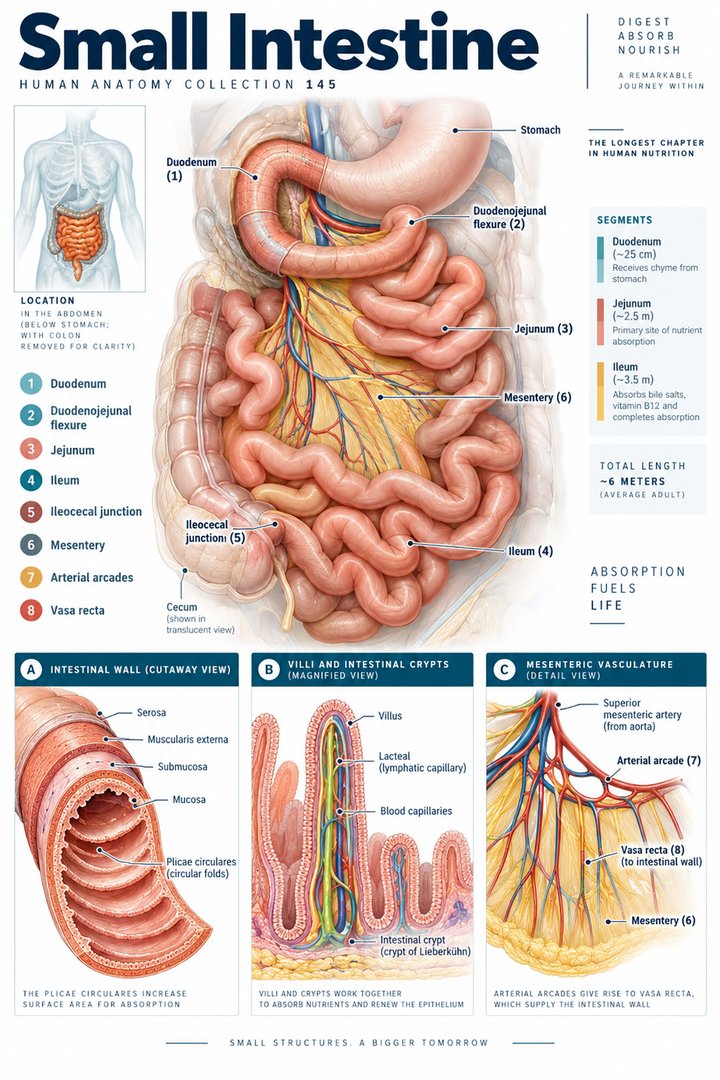
Small Intestine
Individual poster · 300 DPI print files
Regular $9.90
Explore poster ↗$4.90USD
Offer price · Save $5.00Individual poster · 300 DPI print files
Reduced web preview. Separate high-resolution print files are supplied with the digital download.
ANATOMY 145
A modern anatomy illustration exploring small intestine, designed for educational and decorative use.
Purchases are not available yet. Checkout and download delivery are being prepared.
Sold by Kunstolymp.de · Germany
Compare prices & the complete collection ↗This is a DIGITAL DOWNLOAD. No physical product will be shipped. After purchase, download your files and print them at home, at a local print shop, or through an online professional printing service.
The separate 300 DPI print files are ideal for 24×36-inch posters (approximately 60×90 cm). ISO and 5×7 formats are included. The white border lets you adjust the layout or trim to fit other frame sizes; check the preview before printing to keep the illustration and labels visible.
The planned bundle delivery includes a PDF information sheet with a link to the relevant Google Drive folder and download instructions. The store is currently in preview and purchases are not yet available.
A science-inspired choice for a student’s study corner, an educator’s classroom, or an anatomy enthusiast’s wall. Final licensing terms will apply.
CLINICAL CONTEXT
The small intestine comprises duodenum, jejunum, and ileum. Circular folds, villi, and microvilli create a large absorptive surface; epithelial transporters, digestive enzymes, bile, pancreatic secretions, immune tissue, and enteric nerves coordinate digestion and barrier function. The duodenum receives gastric chyme and biliopancreatic secretions; the jejunum absorbs many nutrients; and the terminal ileum reclaims bile acids and vitamin B12. Disease may therefore present as diarrhoea, pain, anaemia, nutrient deficiency, weight change, or extra-intestinal symptoms. Localisation is useful, but symptoms often overlap with pancreatic, colonic, endocrine, infectious, and functional disorders.
Celiac disease is an immune-mediated response to gluten that damages small-intestinal mucosa and can cause diarrhoea, bloating, abdominal pain, iron-deficiency anaemia, weight loss, bone disease, or minimal digestive symptoms. Crohn disease can affect any part of the gastrointestinal tract and often involves the ileum; inflammation may be transmural, causing strictures, fistulas, abscesses, or obstruction. Infectious enteritis, medication injury, lactose intolerance, small-intestinal bacterial overgrowth, and postoperative malabsorption are additional considerations. Ask about stool frequency and blood, nocturnal symptoms, fever, travel, dietary restriction, growth or weight change, family history, medicines, prior surgery, hydration, and functional impact. A gluten-free diet before celiac testing can reduce diagnostic sensitivity; advise patients to discuss testing before removing gluten.
Evaluation begins with history, examination, hydration and nutritional status, then targeted testing. Celiac workup commonly uses serology while the patient consumes gluten, followed where appropriate by duodenal biopsy. Crohn evaluation may combine blood and stool inflammatory markers, infection testing, ileocolonoscopy with biopsies, cross-sectional imaging, and small-bowel capsule or enteroscopy in selected cases. Treatment is cause-specific: celiac disease requires a strict lifelong gluten-free diet with dietitian guidance and monitoring for deficiencies; Crohn treatment may use corticosteroids for induction in selected flares, immunomodulators, biologic or targeted therapies, nutrition support, endoscopic procedures, or surgery for complications. Rehydration and electrolyte replacement are important in significant diarrhoea. Persistent bleeding, obstruction, abscess, severe malnutrition, or systemic illness needs prompt specialist care.
Dietitian-led nutrition, adequate energy and protein, correction of documented deficiencies, stress support, and gentle activity can complement disease-directed care. Restrictive elimination diets and supplements should be supervised because they can worsen malnutrition or conceal the cause. Probiotics and herbal products do not replace proven celiac or Crohn treatment, and interactions or contamination are possible. Seek urgent assessment for severe or escalating pain, abdominal distension with vomiting or inability to pass stool or gas, substantial blood in stool, dehydration, fever with immunosuppression, or fainting. This article supports clinical education and does not provide individual medical advice.
Further reading: NIDDK: celiac disease diagnosis · NIDDK: celiac disease treatment · NIDDK: Crohn disease diagnosis
Explain the working diagnosis, important alternatives, planned tests, expected course, and specific safety-netting in language the patient can use. Invite questions about treatment goals, capacity, cost, culture, and complementary therapies. Use a professional interpreter when language access could affect consent or understanding, and confirm clear arrangements for timely clinical review in writing. Document the reasoning, reassess response to treatment, and coordinate care across professions when illness affects more than one system. Teaching anatomy is most useful when it supports this partnership: accurate localisation, respectful listening, timely escalation, and a plan that remains responsive to the individual patient.
HUMAN ANATOMY COLLECTION · 001—300
A closer look at what makes us human. Discover anatomy posters for your study space, classroom, and everyday curiosity.
DIGITAL DOWNLOADS · 300 DPI PRINT FILES
EXPLORE BY SYSTEM
LEARN & EXPLORE
Detailed English guides with Latin terminology, diagrams, real images, and clinical learning connections.
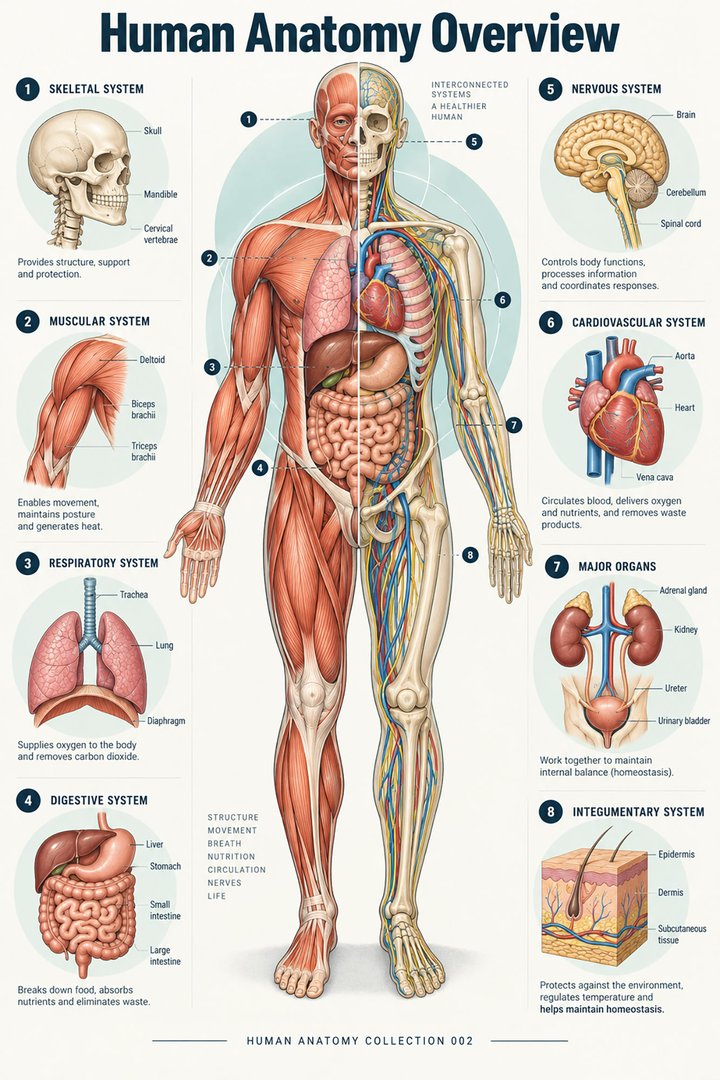 Human Anatomy Diagrams ↗
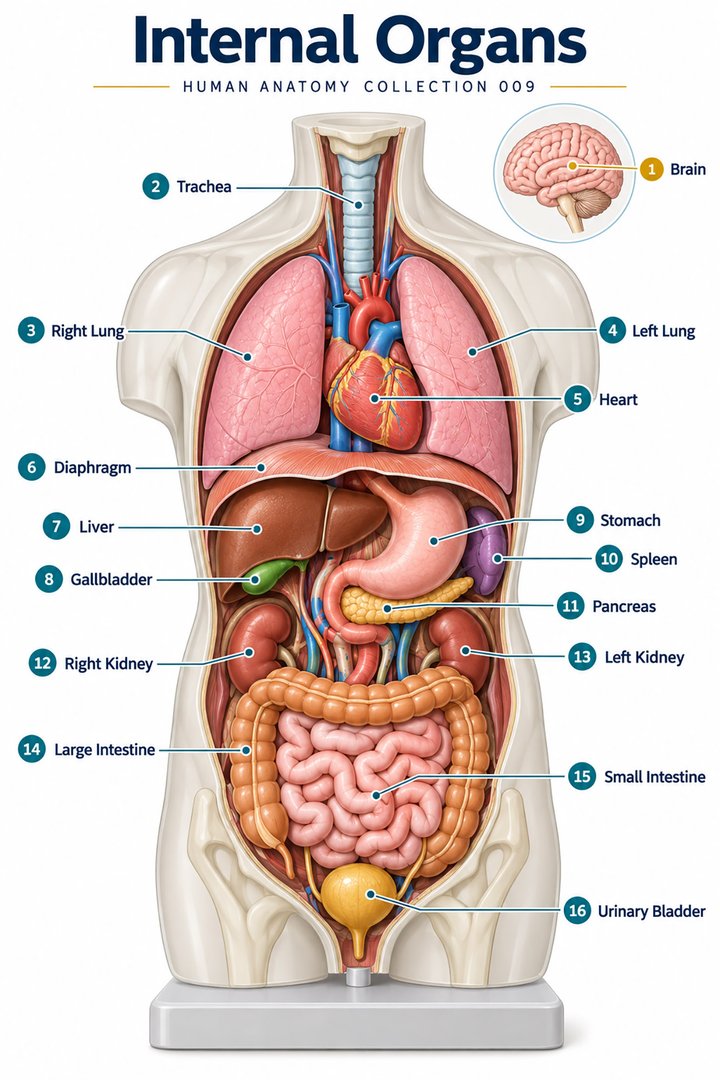 Human Body Organs ↗
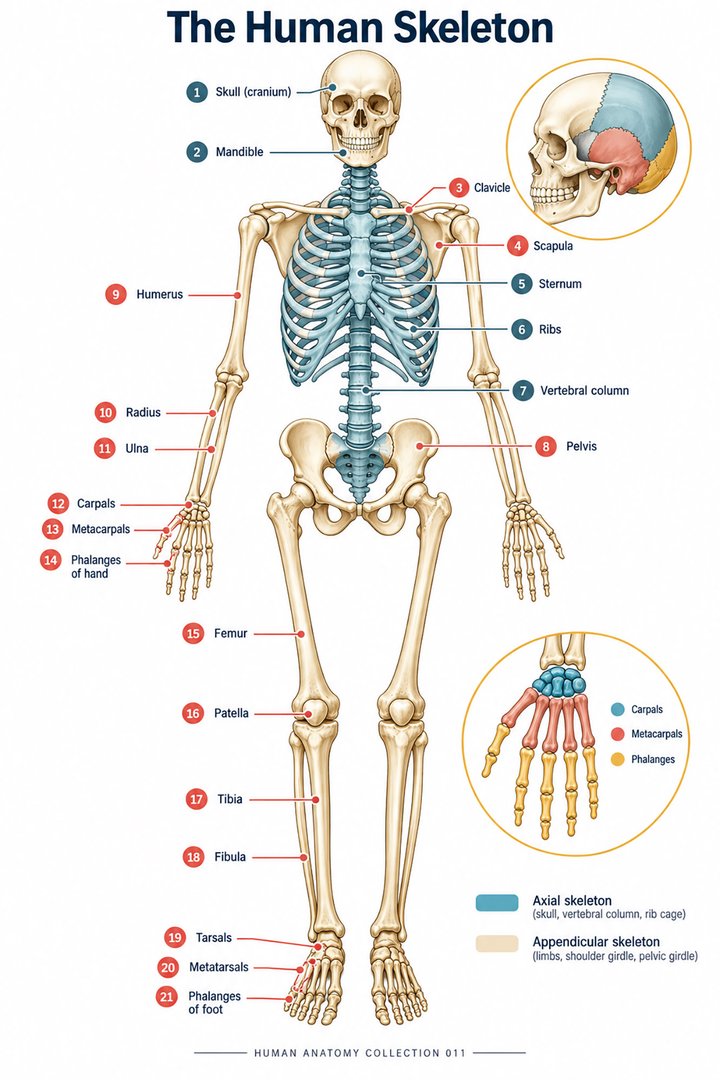 Skeletal System Anatomy ↗
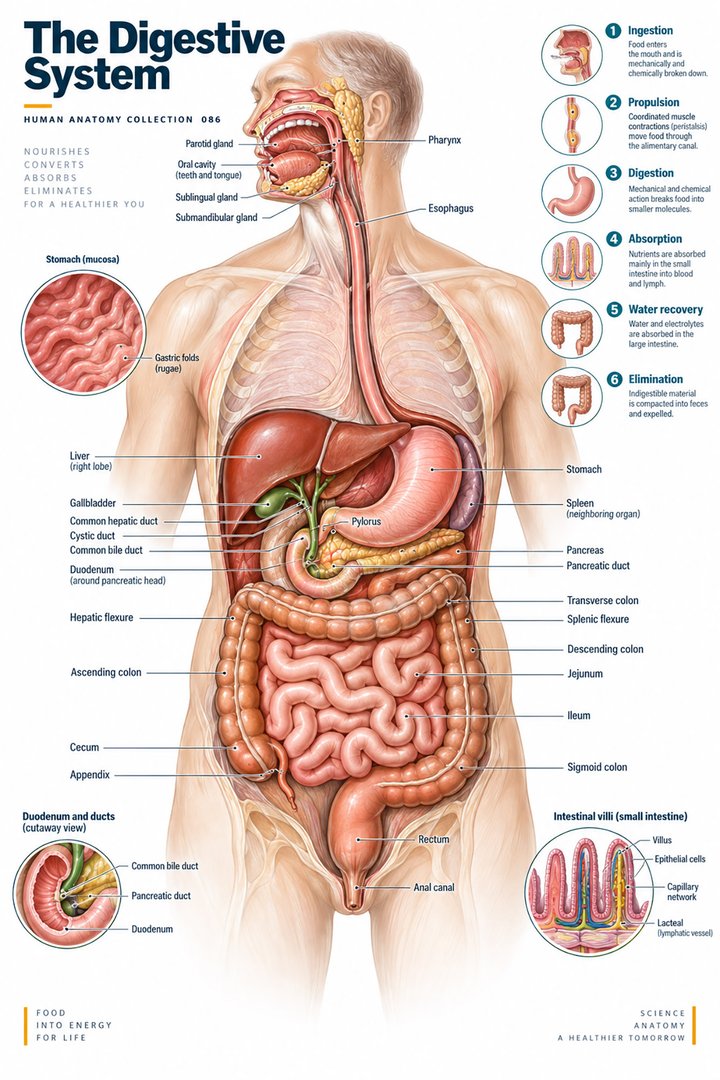 Human Digestive System ↗
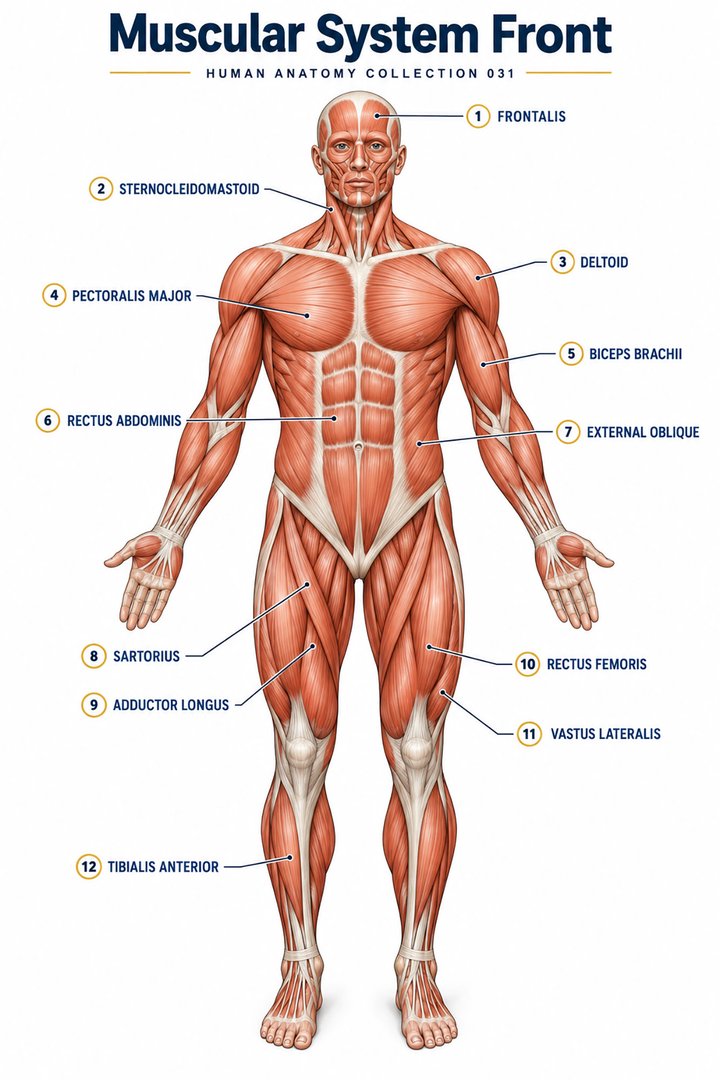 Muscular System Overview ↗
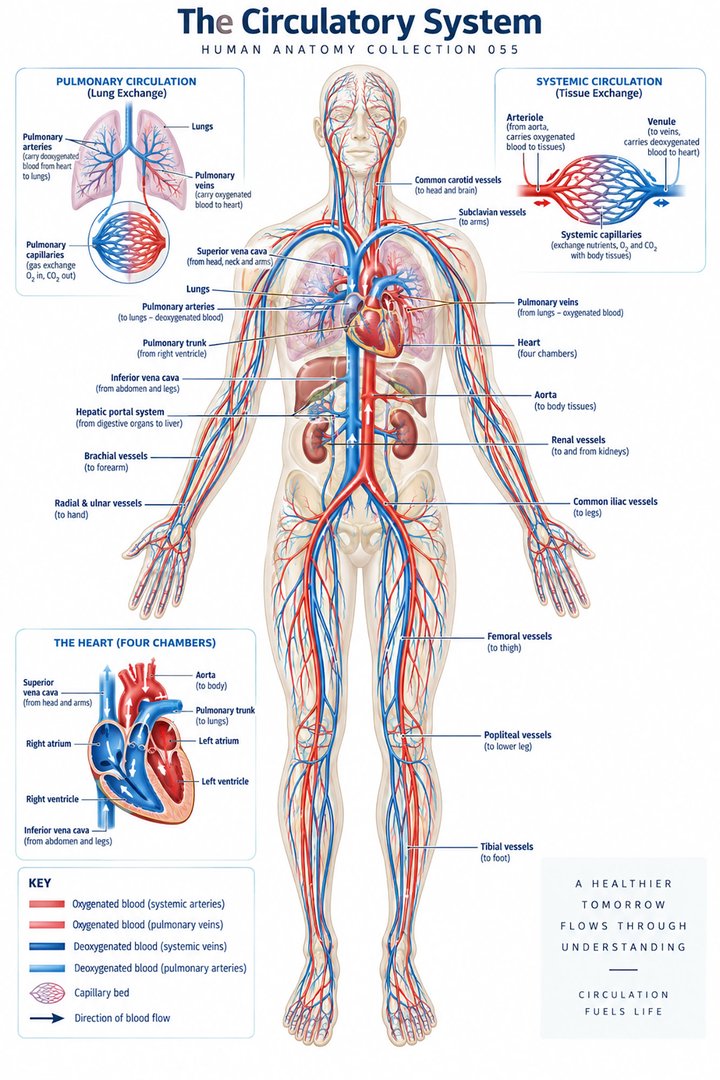 Human Circulatory System ↗
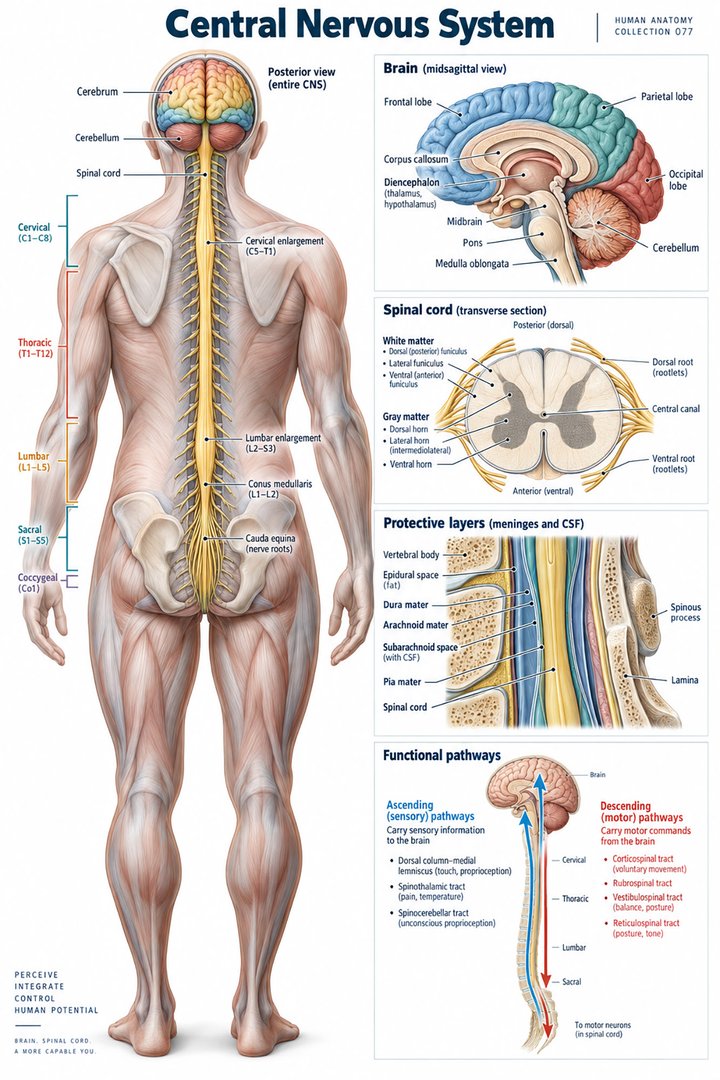 Human Nervous System ↗
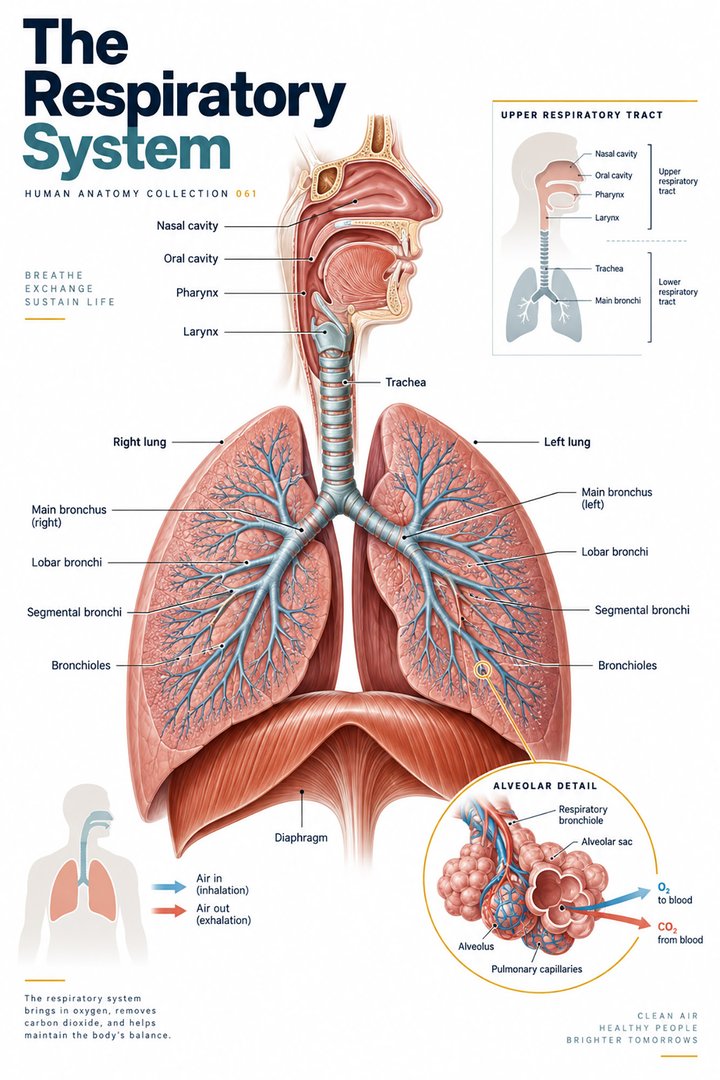 Respiratory System Functions ↗
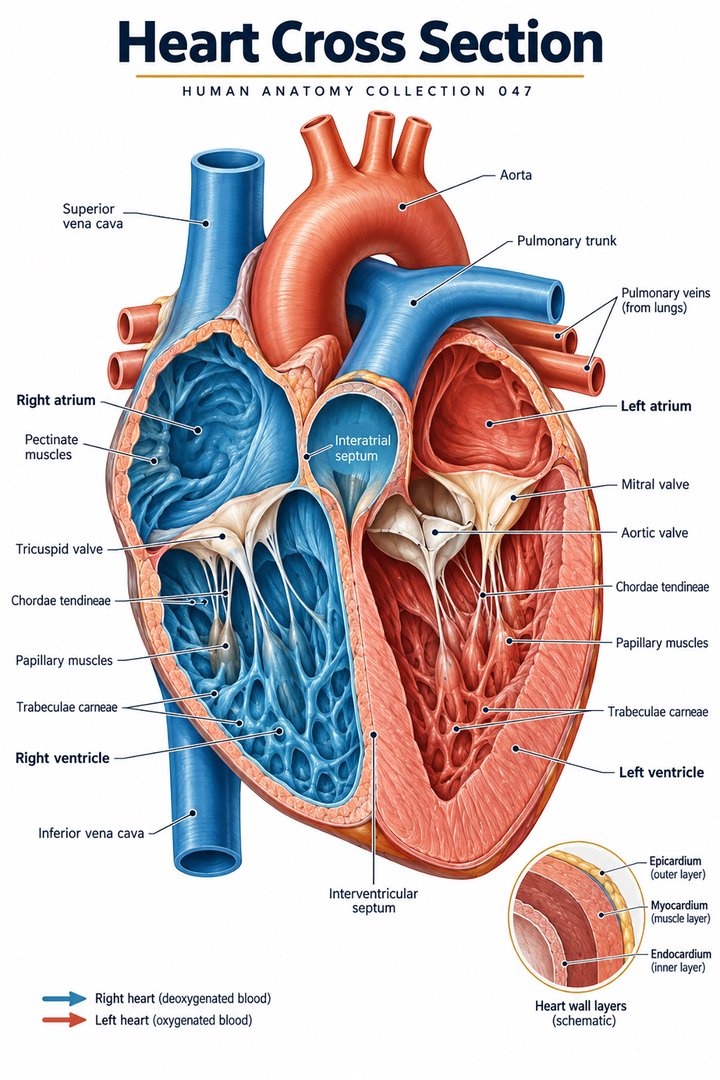 Human Heart Structure ↗
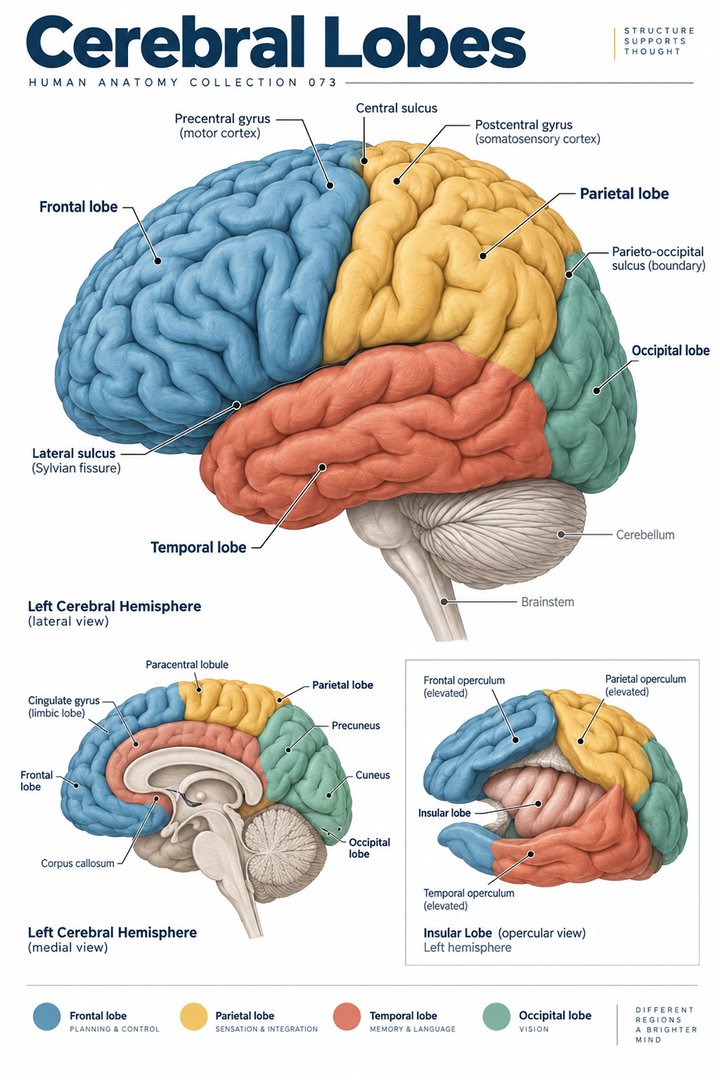 Human Brain Lobes ↗
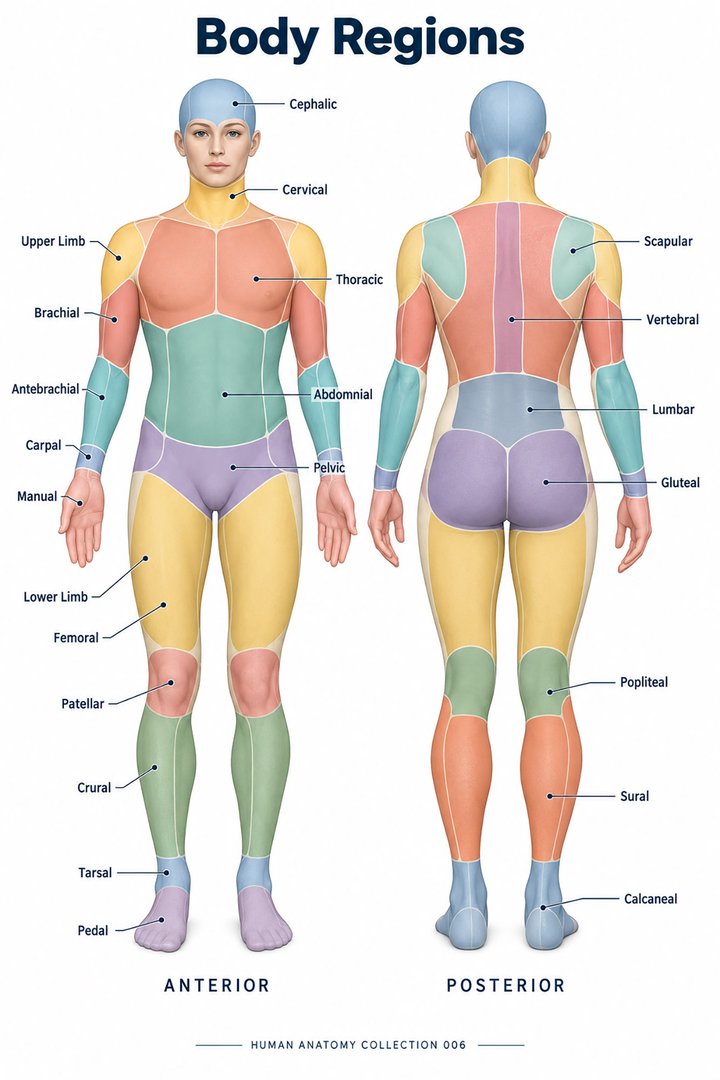 Human Body Parts ↗
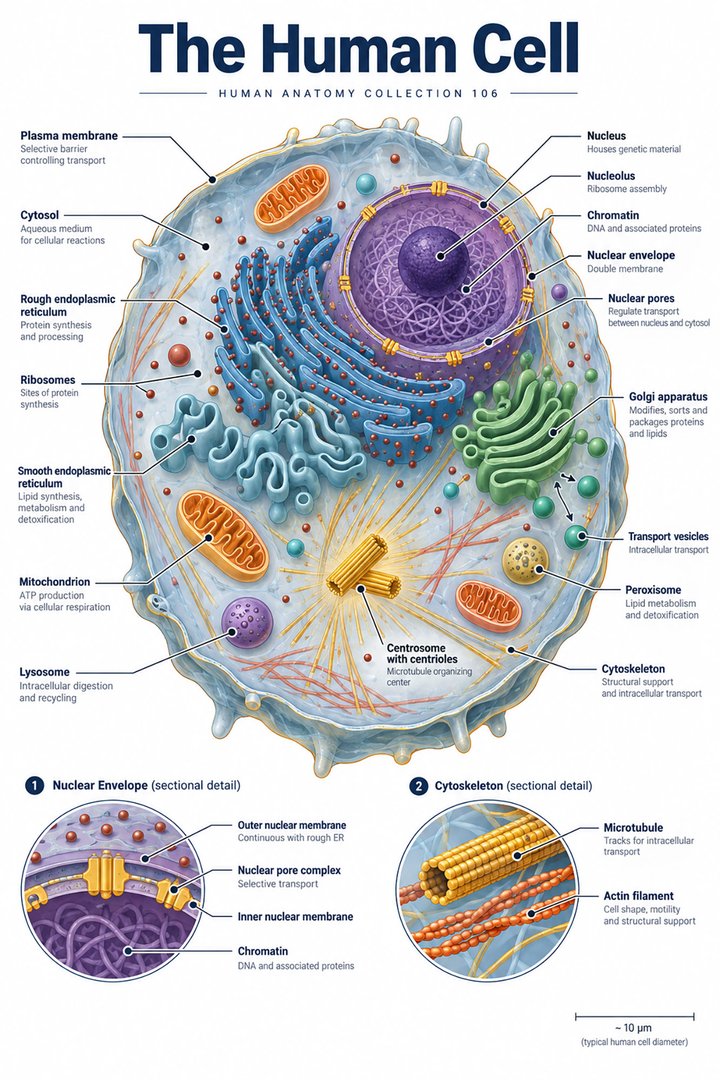 Human Cell Structure ↗
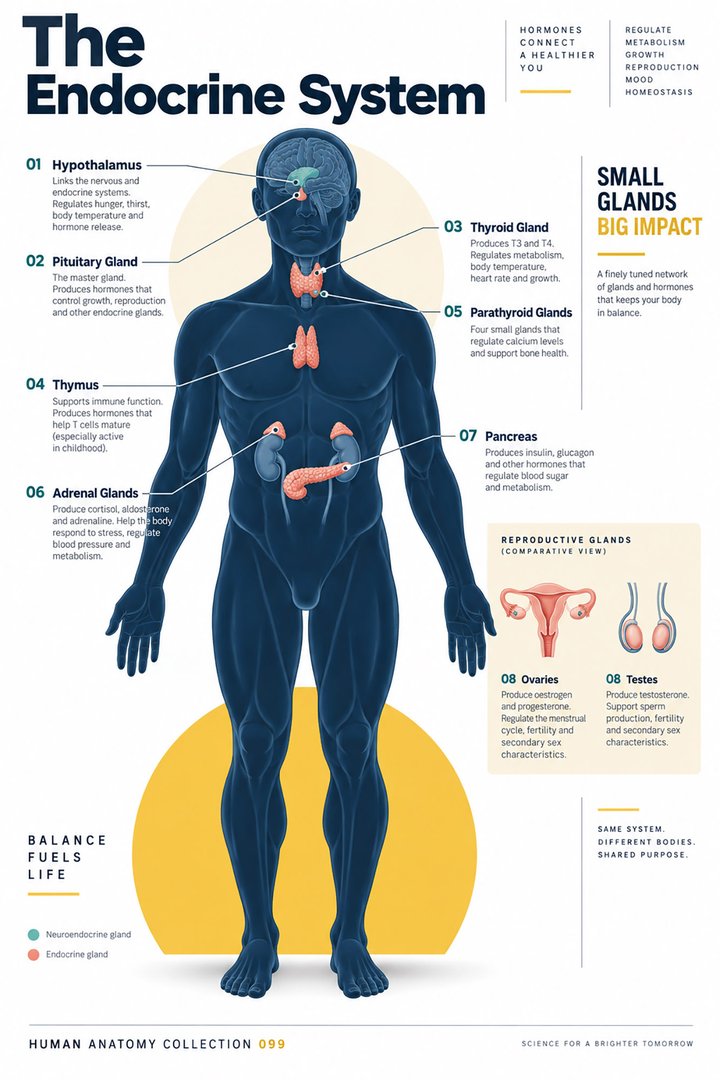 Human Endocrine System ↗
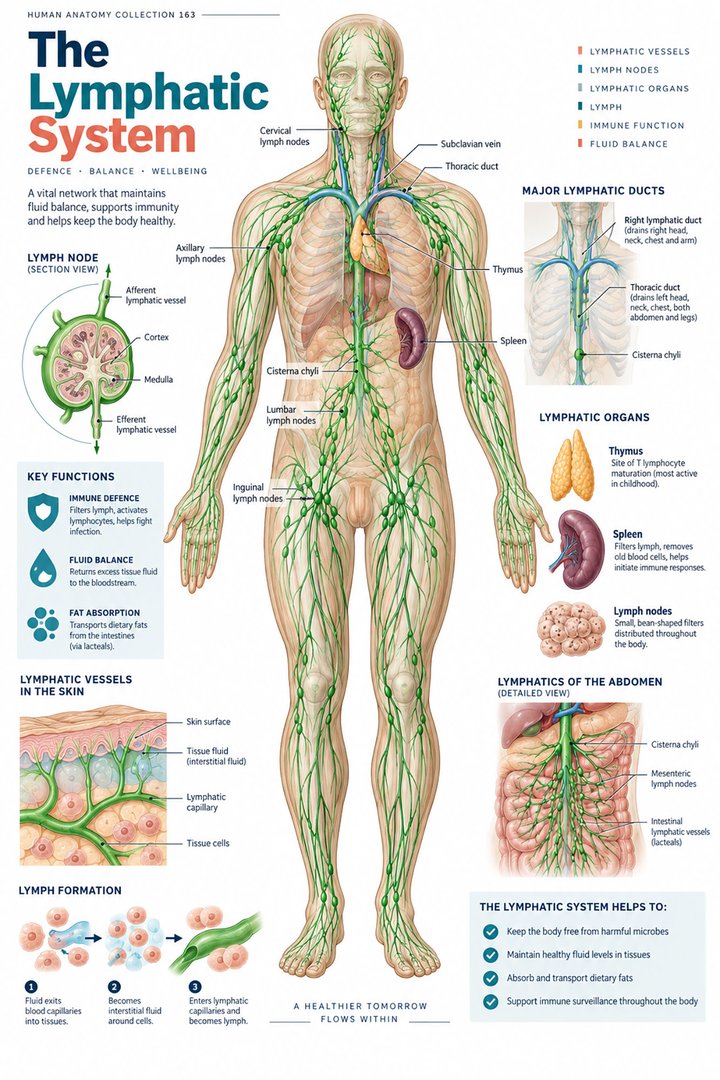 Human Lymphatic System ↗
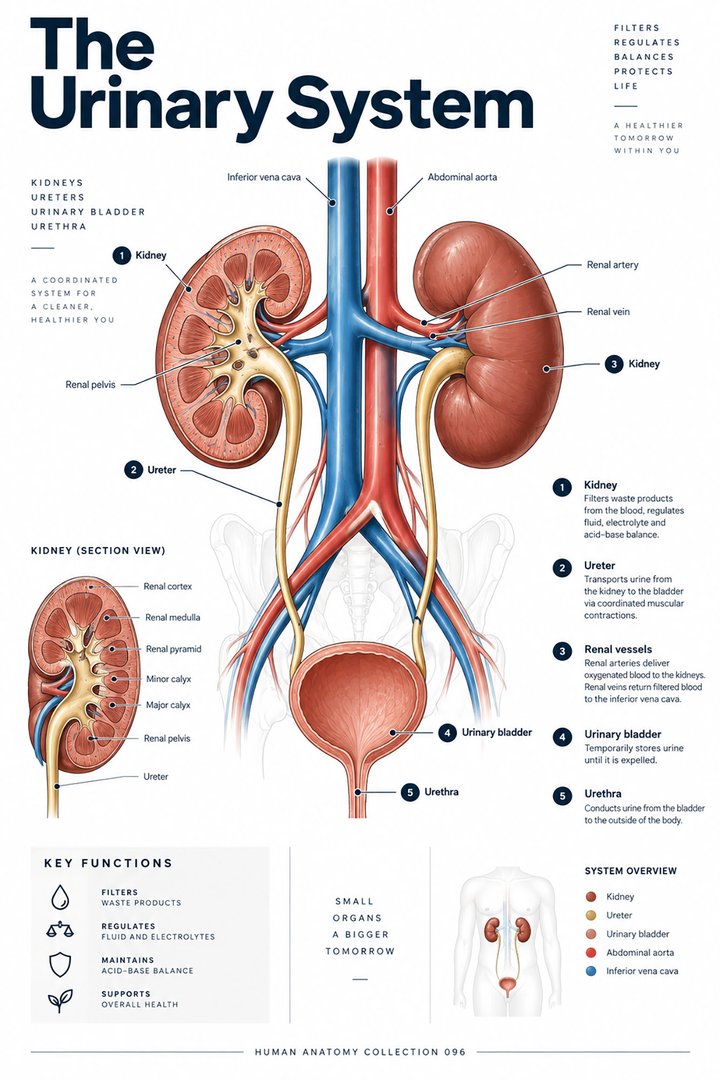 Human Urinary System ↗
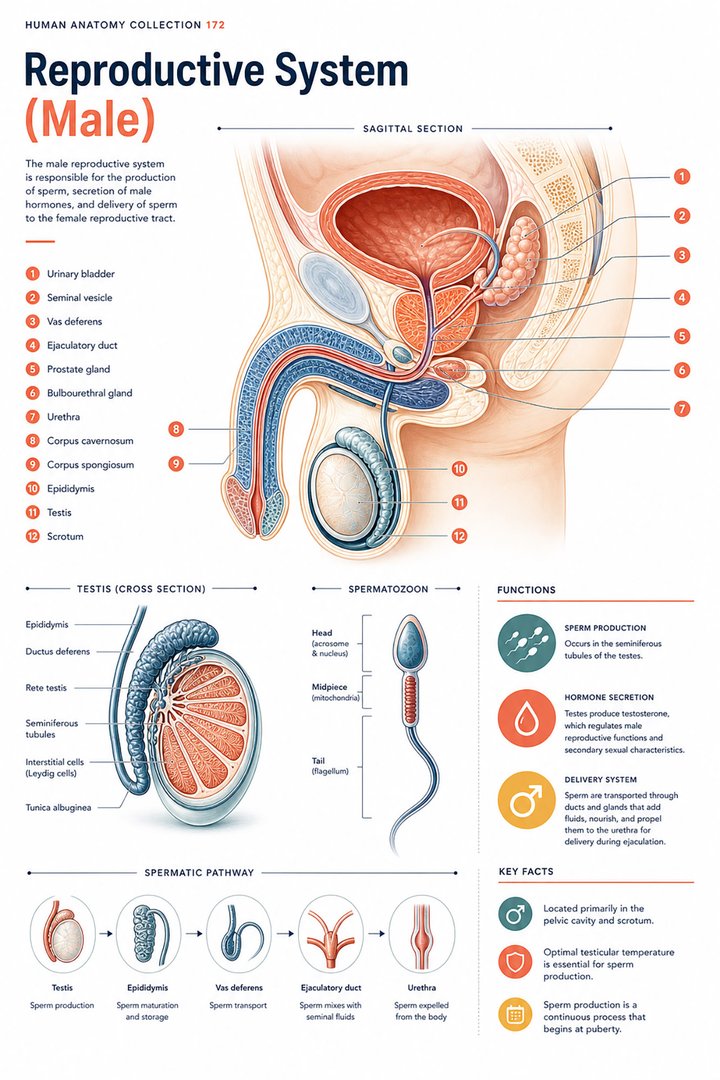 Male Reproductive System ↗
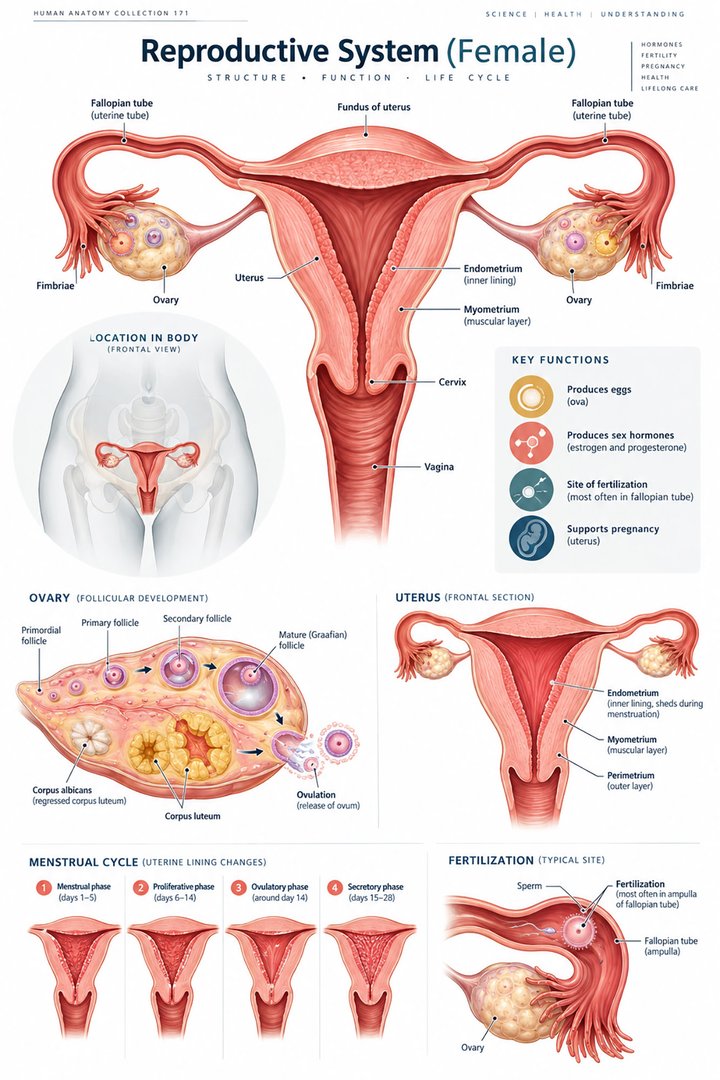 Female Reproductive System ↗
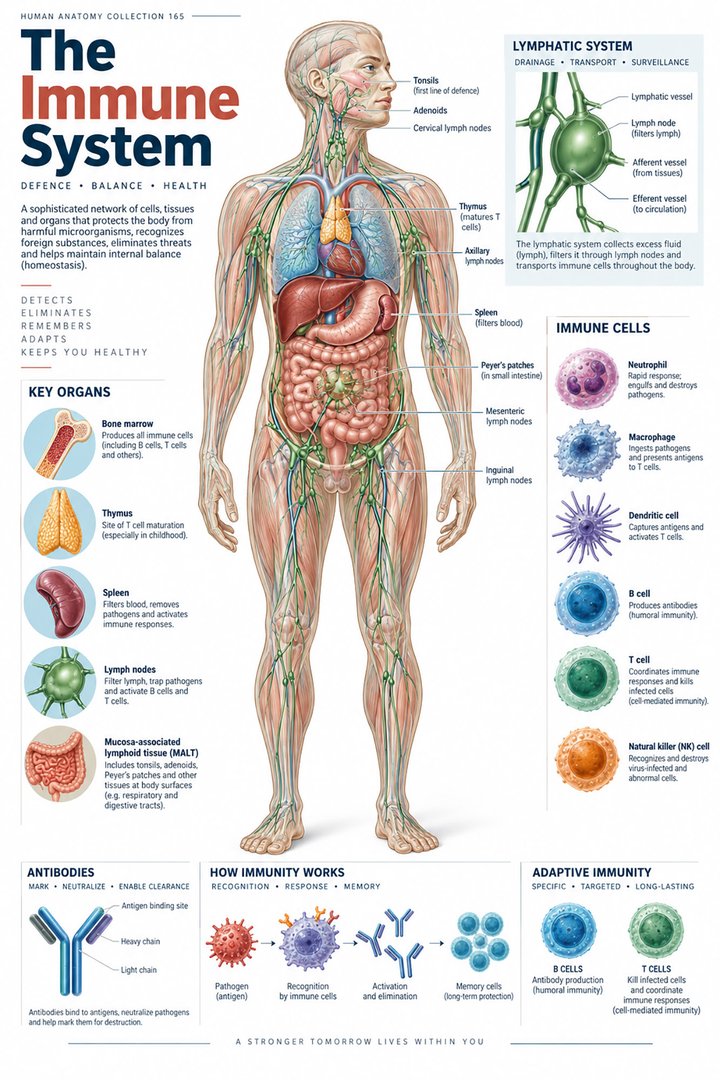 Human Immune System ↗Central Nervous System ↗
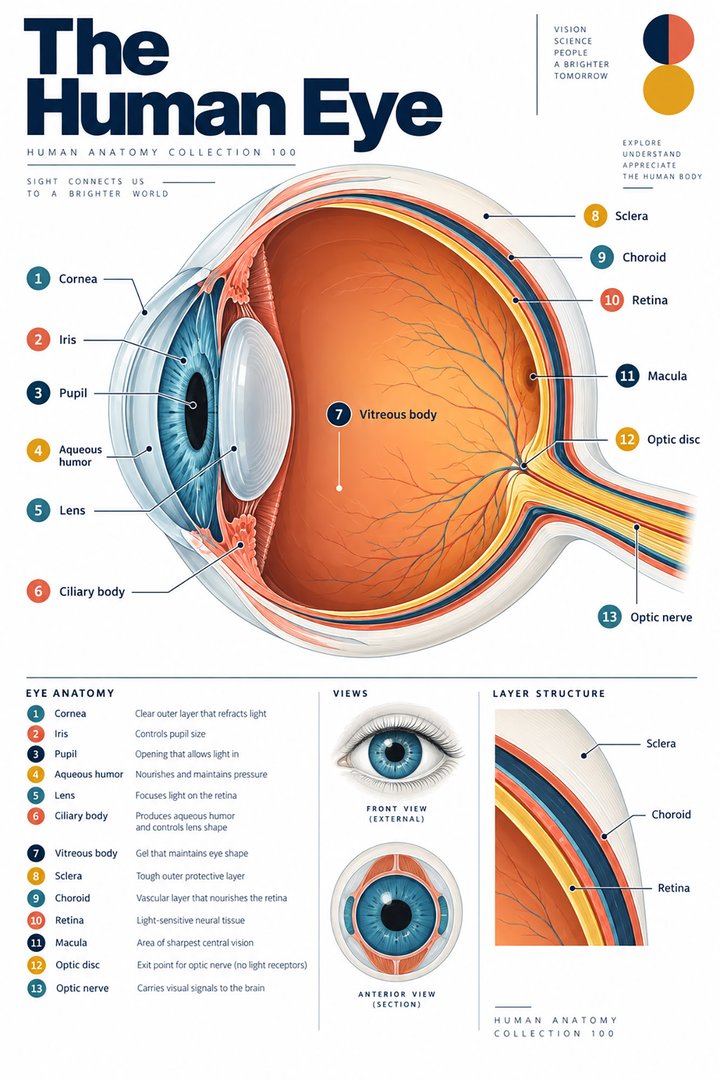 Human Eye Structure ↗
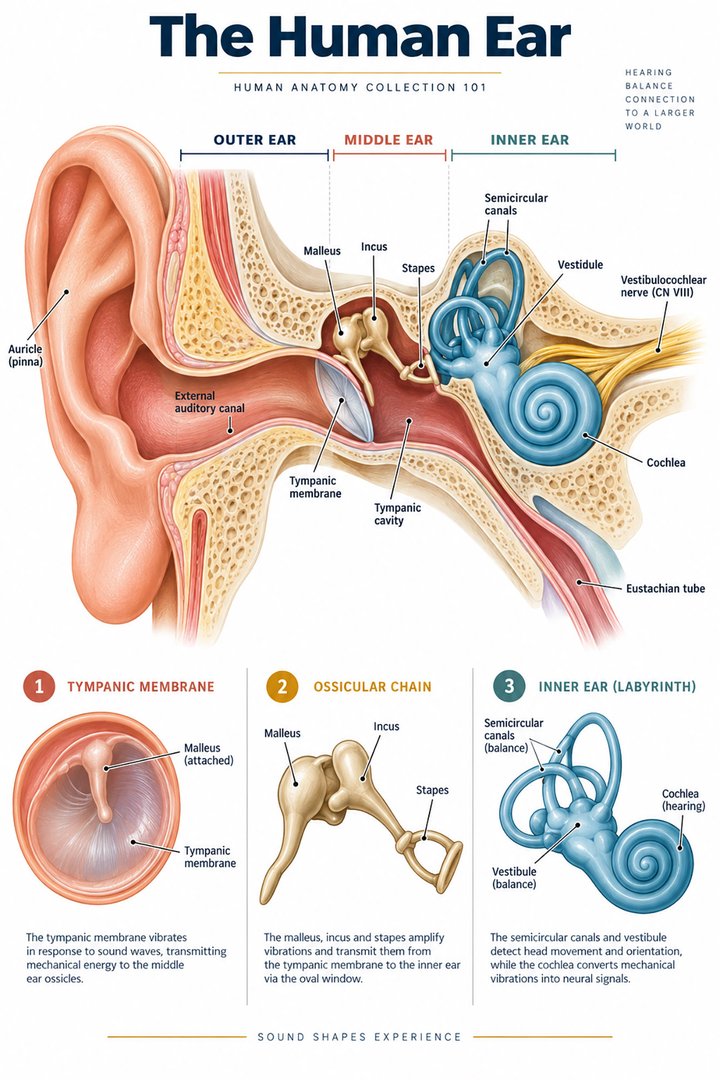 Human Ear Structure ↗
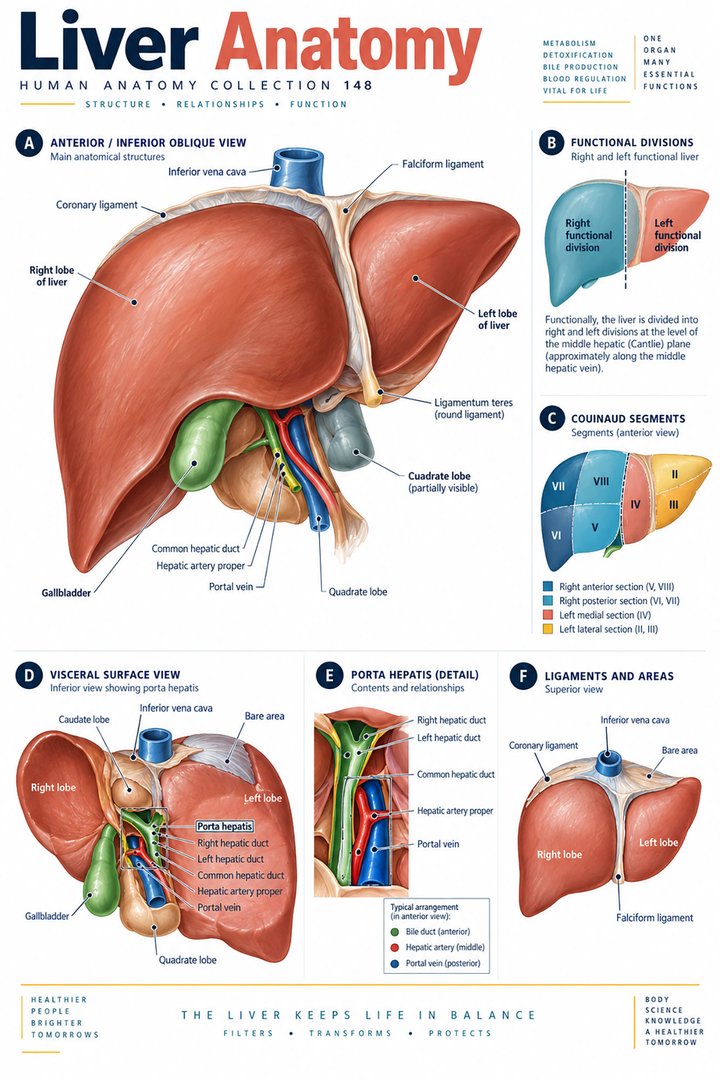 Human Liver Function ↗
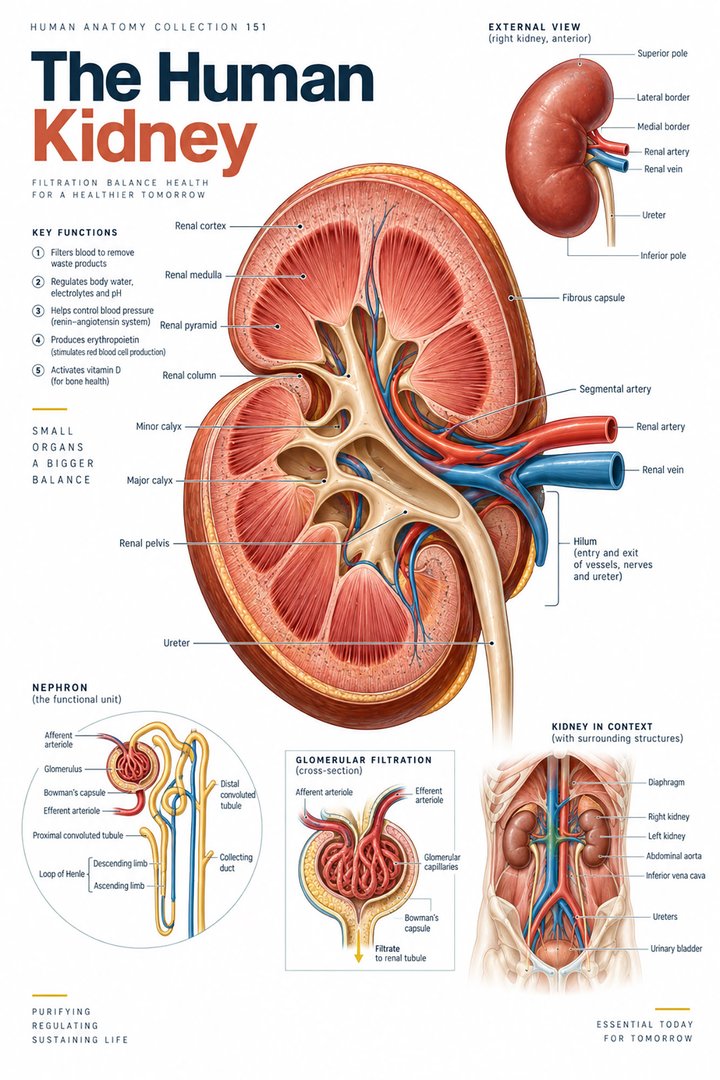 Human Kidney Anatomy ↗
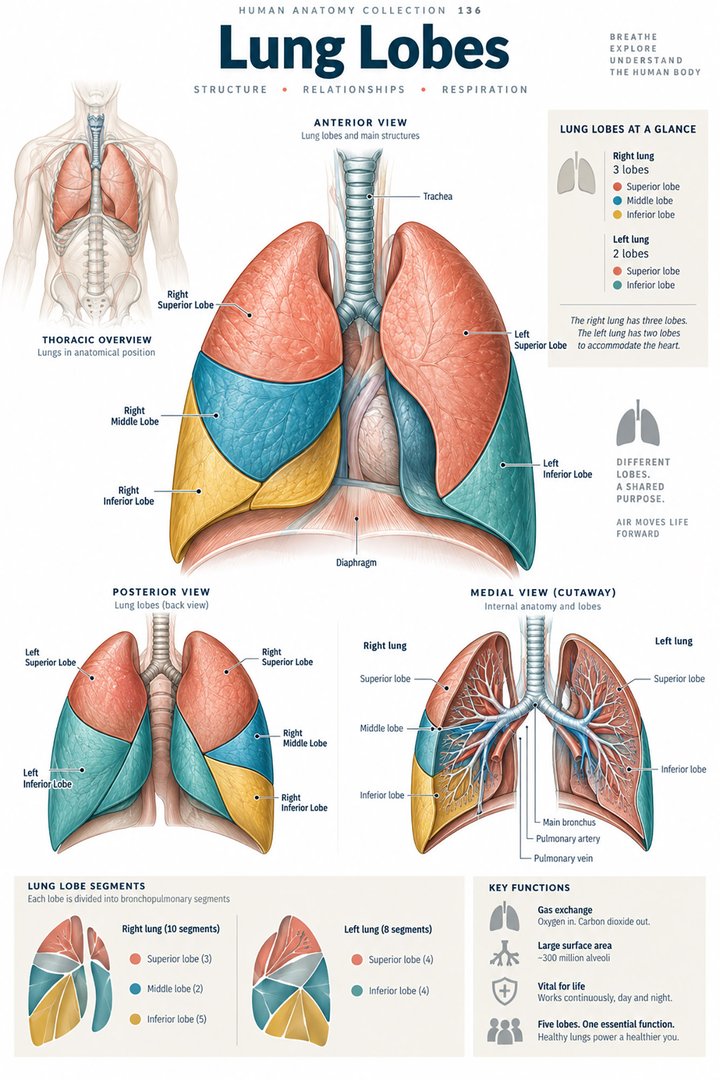 Human Lung Anatomy ↗
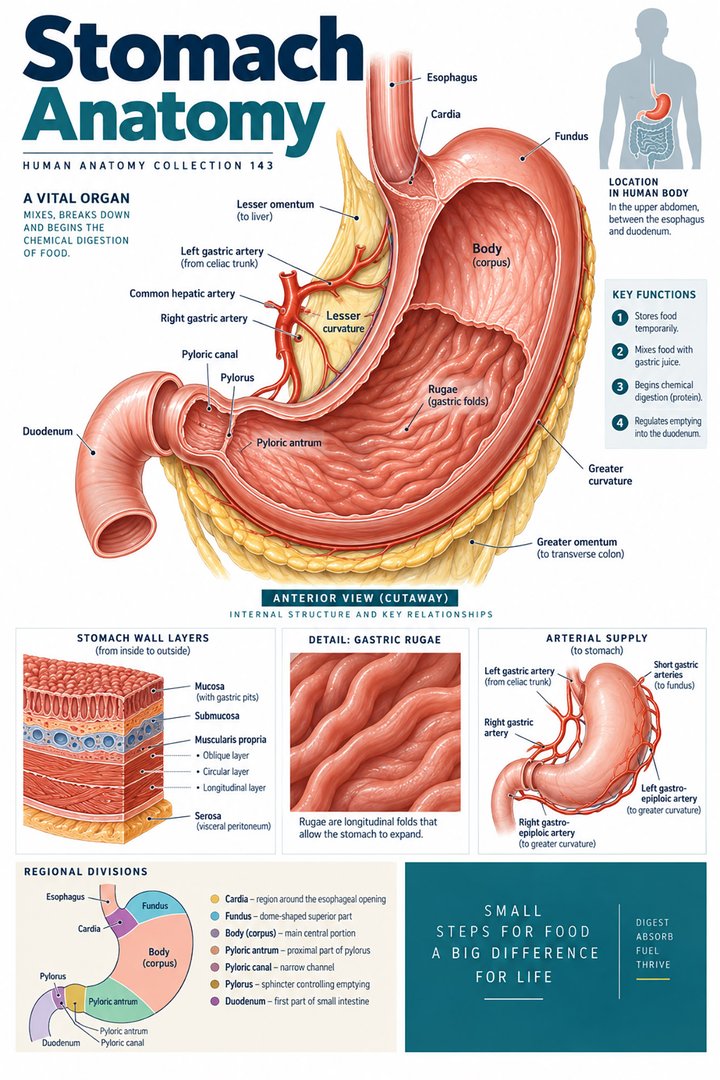 Human Stomach Structure ↗
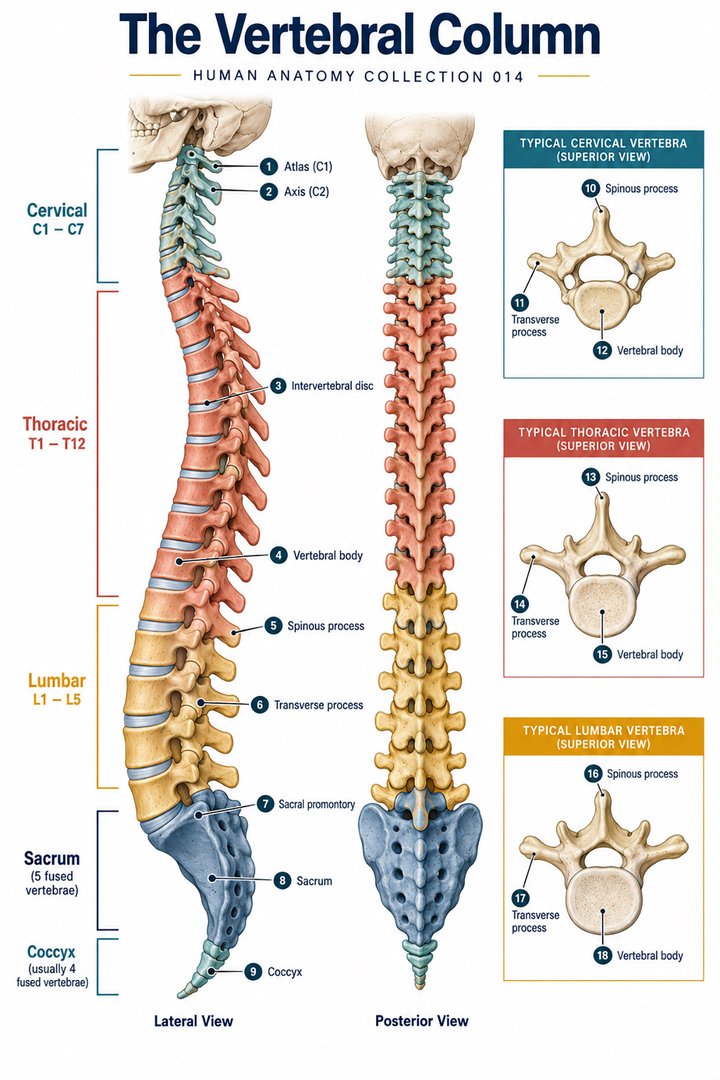 Human Spine Anatomy ↗
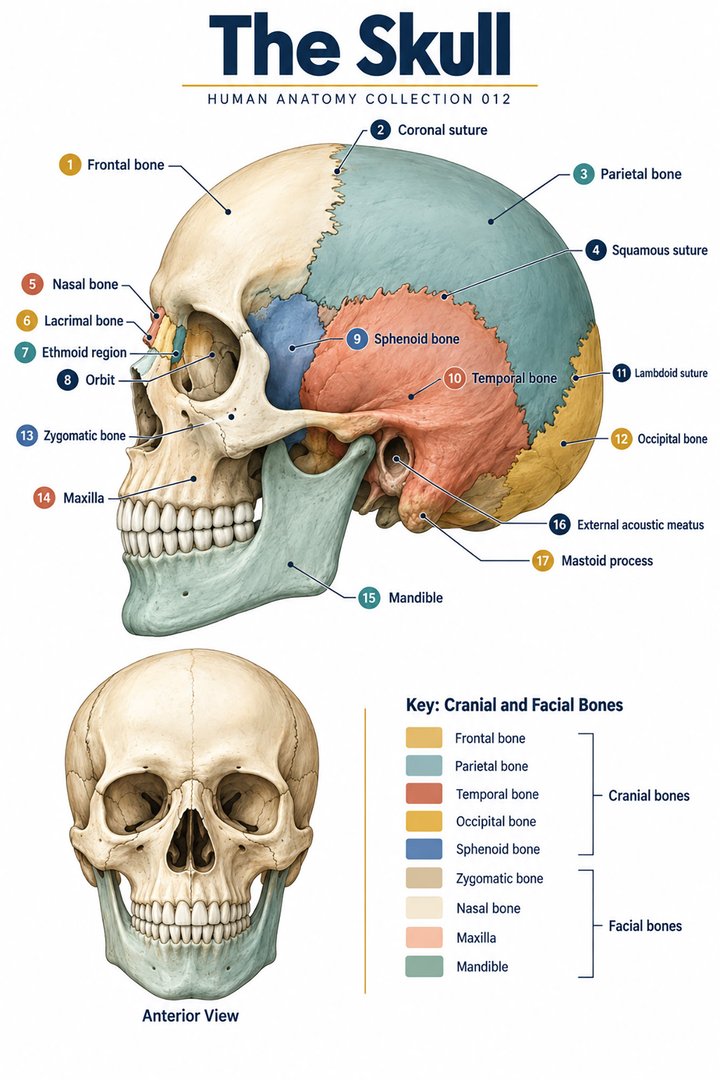 Human Skull Anatomy ↗
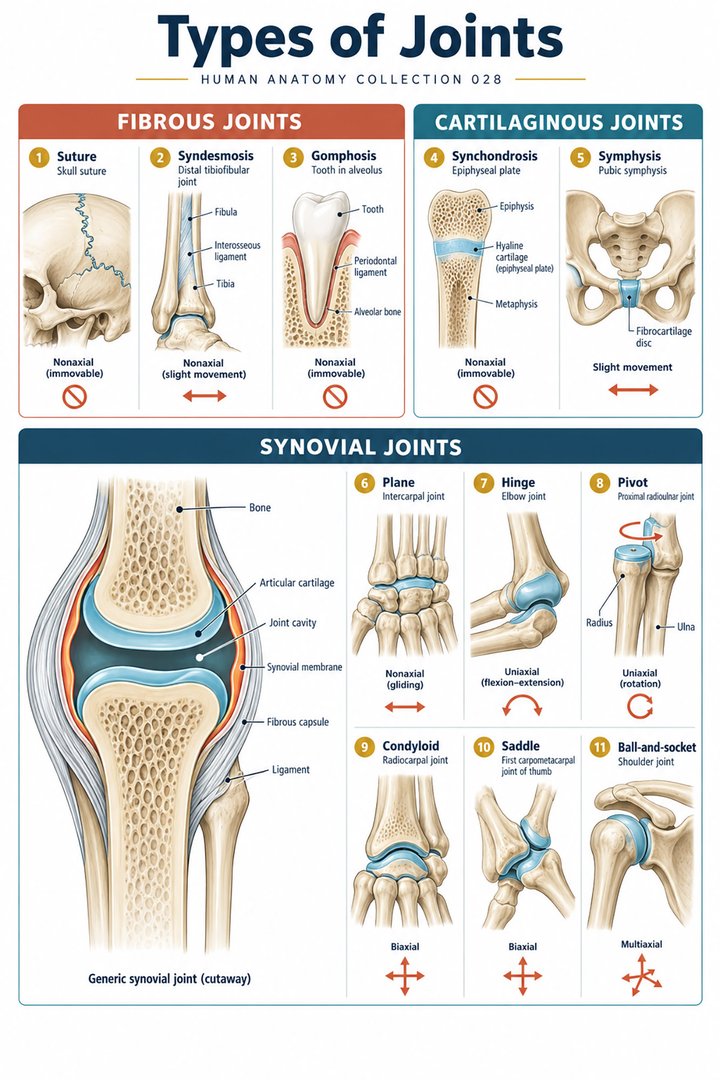 Human Joint Types ↗
 Human Skin Layers ↗
 Autonomic Nervous System ↗
 Human Blood Vessels ↗
 Human Body Tissues ↗
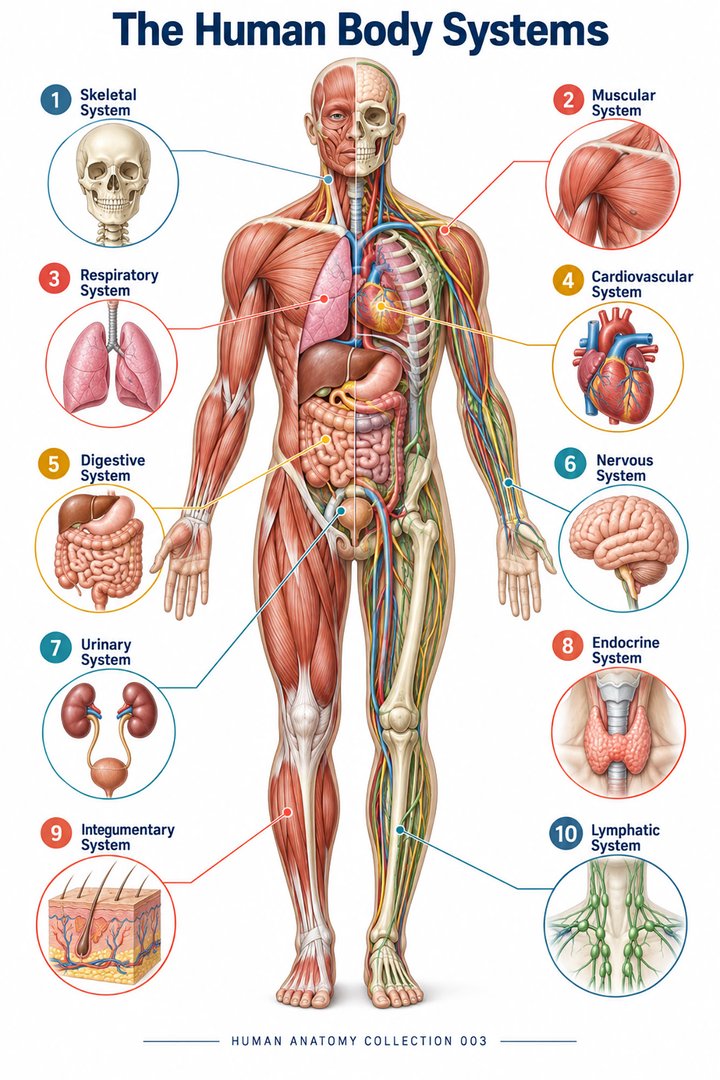 Human Body Systems ↗
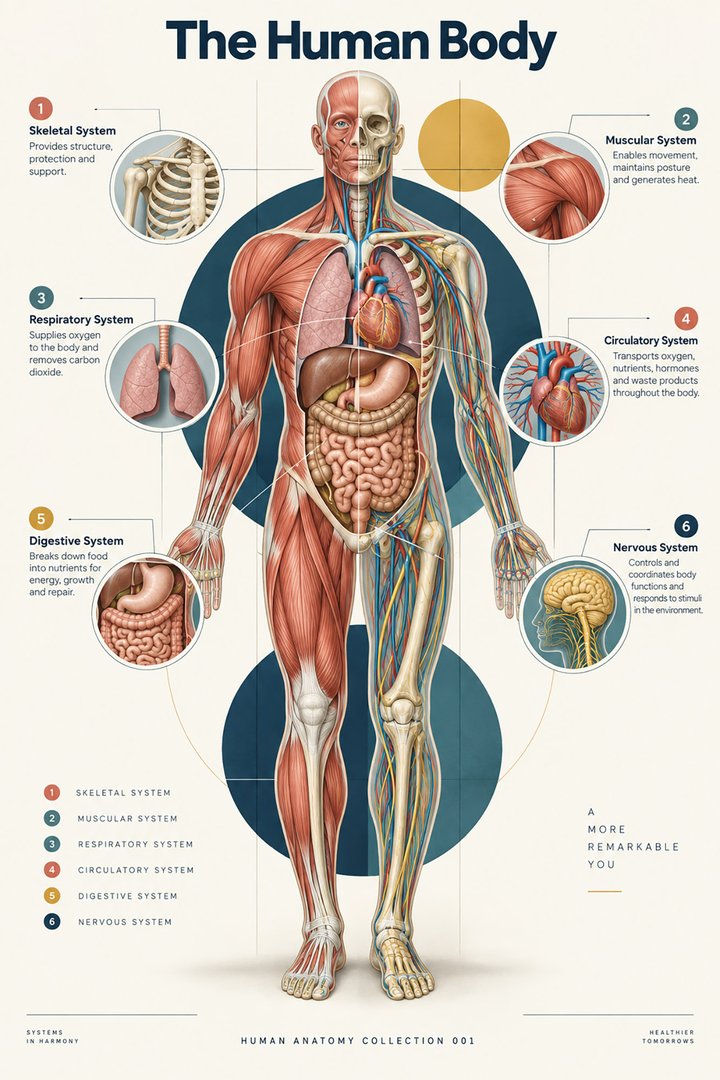 Human Body Facts ↗Human Anatomy and Physiology ↗
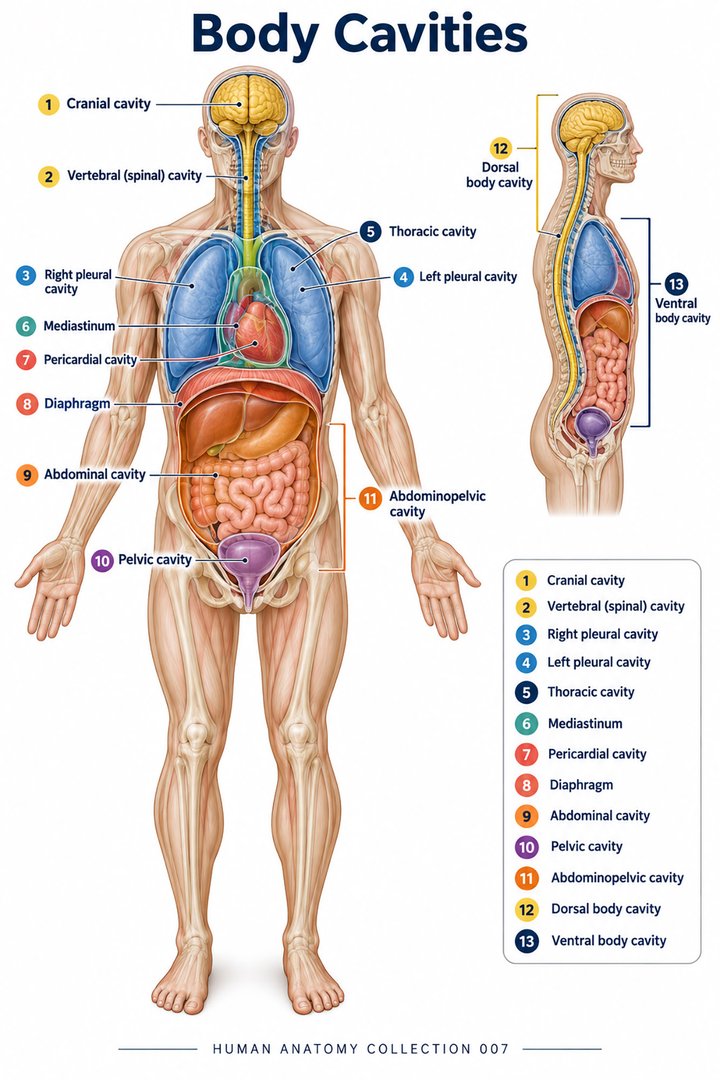 Human Body Cavities ↗Human Torso Anatomy ↗Human Digestive Tract ↗
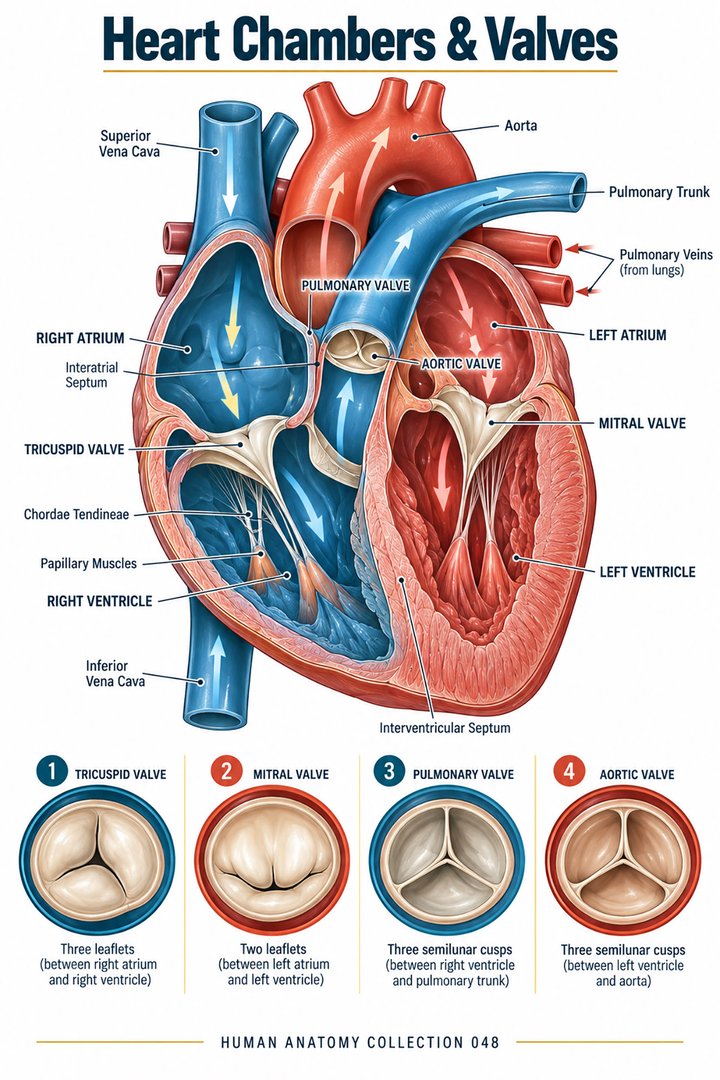 Human Heart Chambers ↗Human Organ Placement ↗
 Human Body Proportions ↗
 Peripheral Nervous System ↗
 Human Endocrine Glands ↗
 Human Bone Density ↗Human Blood Circulation ↗
 Human Muscle Groups ↗
 Human Spinal Cord ↗
 Human Thyroid Gland ↗
 Human Pancreas Function ↗
 Human Gallbladder Anatomy ↗