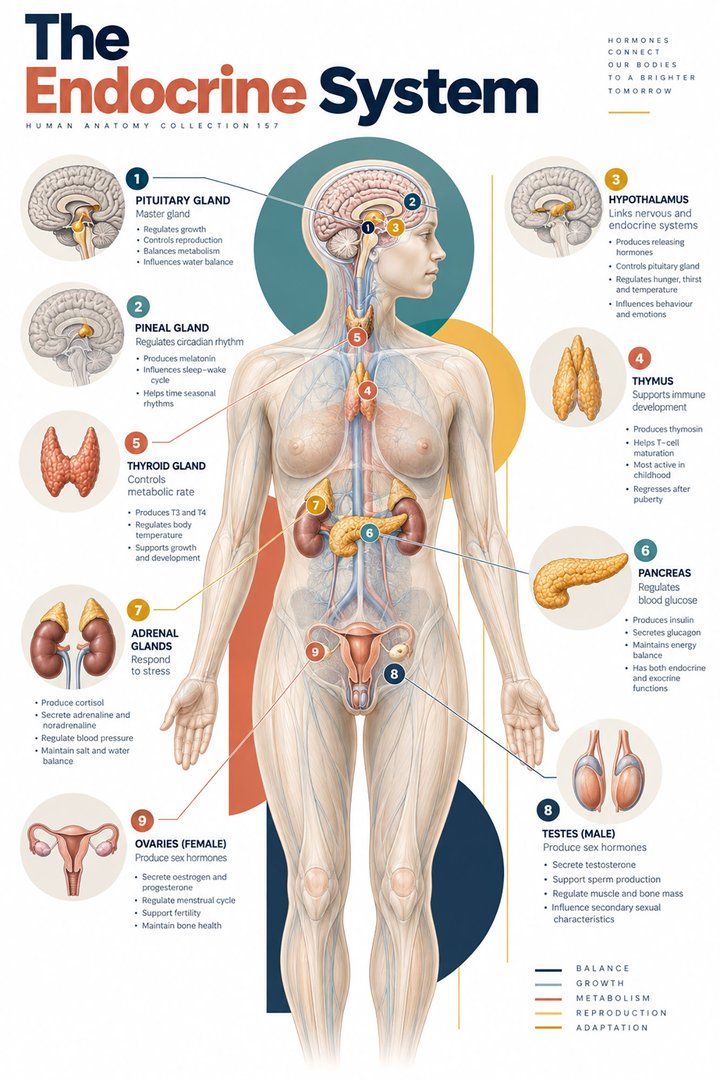
The Endocrine System
Individual poster · 300 DPI print files
Regular $9.90
Explore poster ↗$4.90USD
Offer price · Save $5.00Individual poster · 300 DPI print files
Reduced web preview. Separate high-resolution print files are supplied with the digital download.
ANATOMY 157
A modern anatomy illustration exploring the endocrine system, designed for educational and decorative use.
Purchases are not available yet. Checkout and download delivery are being prepared.
Sold by Kunstolymp.de · Germany
Compare prices & the complete collection ↗This is a DIGITAL DOWNLOAD. No physical product will be shipped. After purchase, download your files and print them at home, at a local print shop, or through an online professional printing service.
The separate 300 DPI print files are ideal for 24×36-inch posters (approximately 60×90 cm). ISO and 5×7 formats are included. The white border lets you adjust the layout or trim to fit other frame sizes; check the preview before printing to keep the illustration and labels visible.
The planned bundle delivery includes a PDF information sheet with a link to the relevant Google Drive folder and download instructions. The store is currently in preview and purchases are not yet available.
A science-inspired choice for a student’s study corner, an educator’s classroom, or an anatomy enthusiast’s wall. Final licensing terms will apply.
CLINICAL CONTEXT
The endocrine system coordinates distant organs through hormones released into circulation. Hypothalamic and pituitary signals regulate peripheral glands; thyroid hormones influence metabolic rate, adrenal hormones affect stress response and salt balance, parathyroid hormone helps control calcium, and pancreatic islets regulate glucose. Gonadal hormones influence reproduction, bone, and secondary sex characteristics. Feedback loops, binding proteins, receptor sensitivity, illness, pregnancy, age, and medicines all shape measured hormone levels. This map is clinically useful because fatigue, weight change, heat or cold intolerance, thirst, polyuria, mood change, menstrual symptoms, weakness, and blood-pressure abnormalities are common but nonspecific and may arise from endocrine or non-endocrine causes.
Diabetes mellitus causes chronic hyperglycaemia from impaired insulin secretion, action, or both, with acute risks such as hypoglycaemia and ketoacidosis and long-term vascular, renal, retinal, and neurological complications. Hypothyroidism may cause cold intolerance, constipation, dry skin, and slowed function; hyperthyroidism can produce tremor, heat intolerance, palpitations, weight loss, and anxiety. Adrenal insufficiency may cause fatigue, weight loss, gastrointestinal symptoms, postural dizziness, and, during crisis, shock. Cortisol excess can cause proximal weakness, skin changes, hypertension, glucose intolerance, and bone fragility. Calcium disorders, pituitary disease, and reproductive endocrine conditions add further presentations. Medication review is essential: glucocorticoids, lithium, amiodarone, biotin supplements, and many other agents can alter symptoms or laboratory interpretation.
History should establish timeline, medications and supplements, family and autoimmune history, pregnancy possibility, sleep, nutrition, and functional impact. Examination may assess vital signs, volume status, thyroid, skin, visual fields, body habitus, neuromuscular signs, and reproductive features with consent. Laboratory testing is selected to test a hypothesis and interpreted with timing, illness, binding proteins, assay limits, and feedback physiology in mind; repeat or dynamic testing may be needed. Treatment targets the cause and may include insulin or other glucose-lowering therapy, thyroid hormone replacement or antithyroid treatment, replacement of cortisol and sometimes mineralocorticoid in adrenal failure, treatment of hormone-secreting tumours, and surgery or radiotherapy for selected pituitary or gland disease. Shared management includes monitoring, complication screening, and clear sick-day or emergency plans where indicated.
Sleep, physical activity, balanced nutrition, stress support, and diabetes self-management education complement medical treatment but do not replace hormone replacement or treatment of hormone excess. “Adrenal fatigue” is not a recognised diagnosis, and unregulated glandular products or high-dose iodine can cause harm. Supplements such as biotin can interfere with laboratory assays; patients should disclose them and follow laboratory advice before testing. Sudden confusion, severe vomiting, collapse, profound weakness in a person with adrenal insufficiency, severe symptomatic hypo- or hyperglycaemia, chest pain with marked palpitations, or visual field loss requires urgent assessment. This educational guide does not replace individual evaluation.
Further reading: NIDDK: endocrine diseases · NIDDK: diabetes overview · NIDDK: hypothyroidism
Explain the working diagnosis, important alternatives, planned tests, expected course, and specific safety-netting in language the patient can use. Invite questions about treatment goals, capacity, cost, culture, and complementary therapies. Use a professional interpreter when language access could affect consent or understanding, and confirm clear arrangements for timely clinical review in writing. Document the reasoning, reassess response to treatment, and coordinate care across professions when illness affects more than one system. Teaching anatomy is most useful when it supports this partnership: accurate localisation, respectful listening, timely escalation, and a plan that remains responsive to the individual patient.
HUMAN ANATOMY COLLECTION · 001—300
A closer look at what makes us human. Discover anatomy posters for your study space, classroom, and everyday curiosity.
DIGITAL DOWNLOADS · 300 DPI PRINT FILES
EXPLORE BY SYSTEM
LEARN & EXPLORE
Detailed English guides with Latin terminology, diagrams, real images, and clinical learning connections.
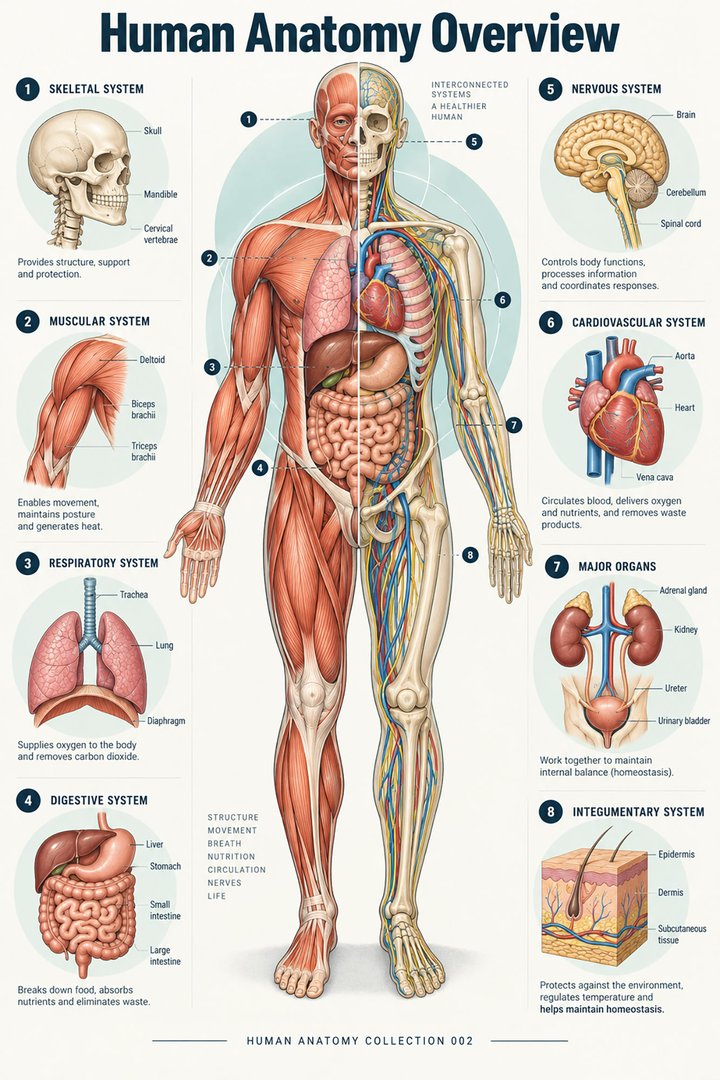 Human Anatomy Diagrams ↗
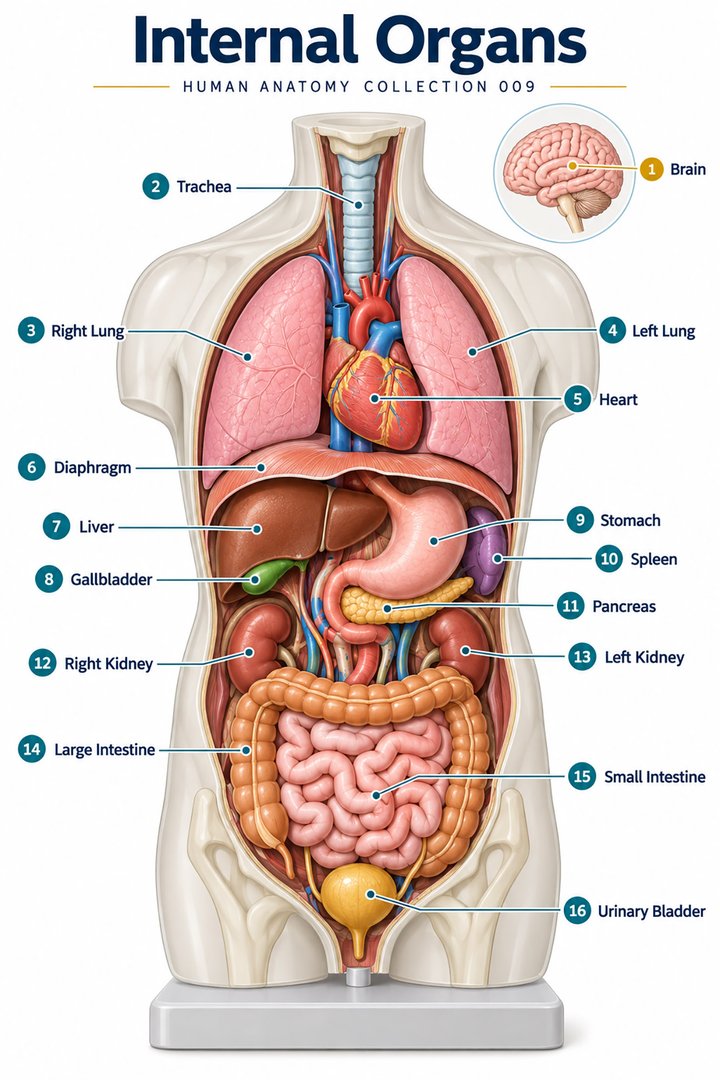 Human Body Organs ↗
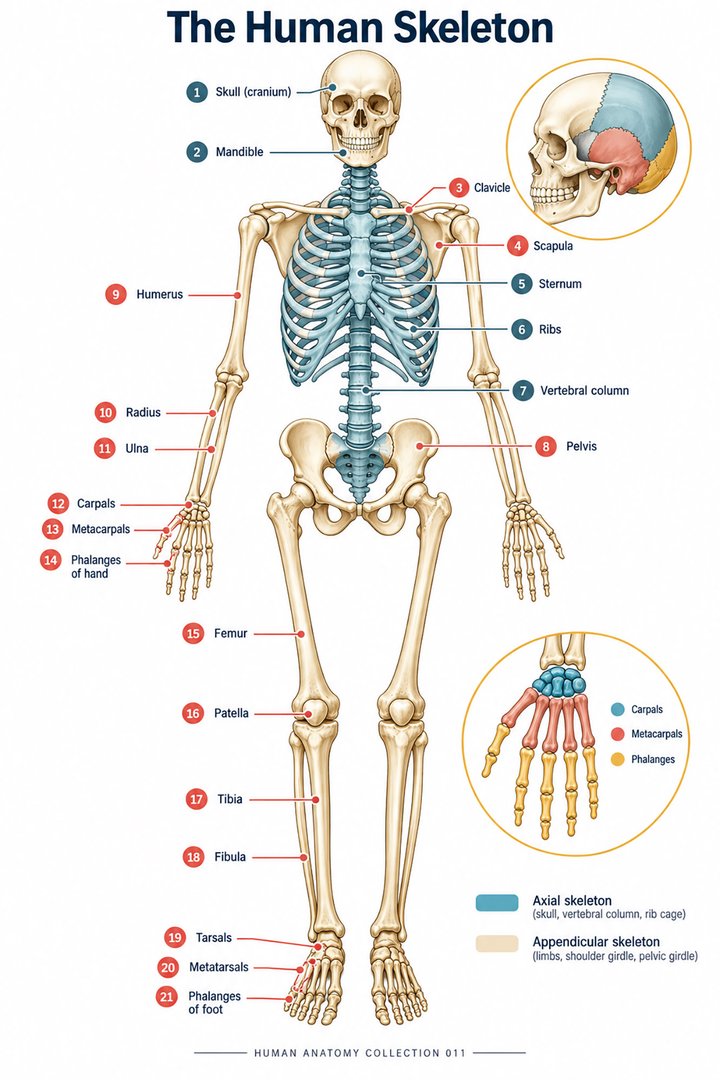 Skeletal System Anatomy ↗
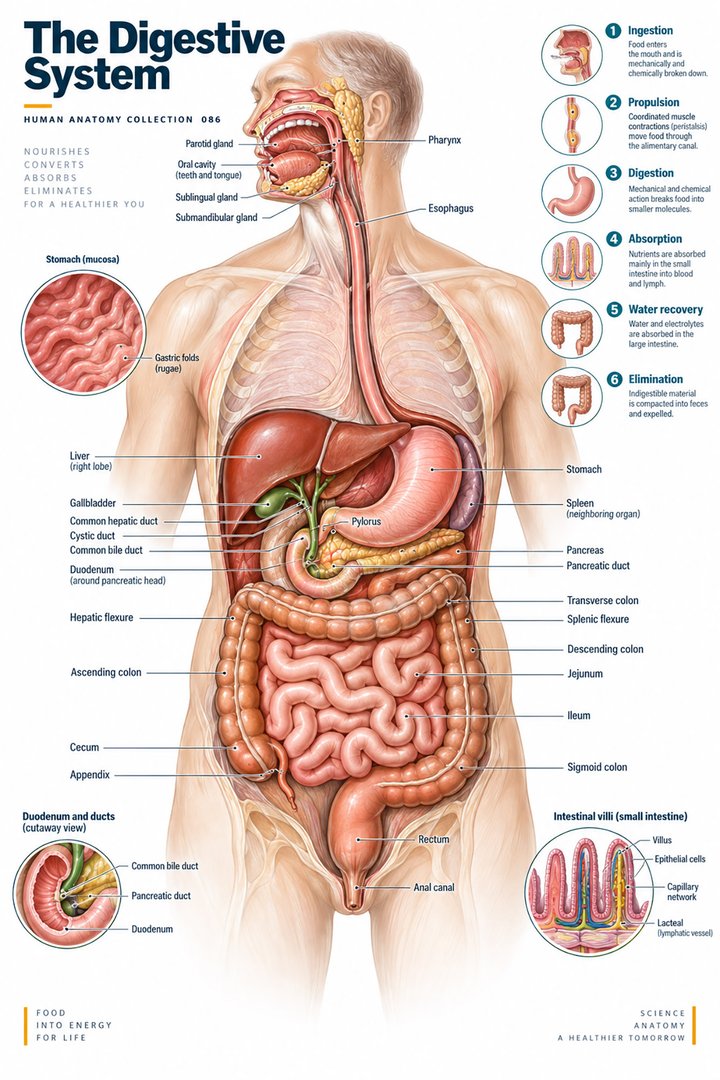 Human Digestive System ↗
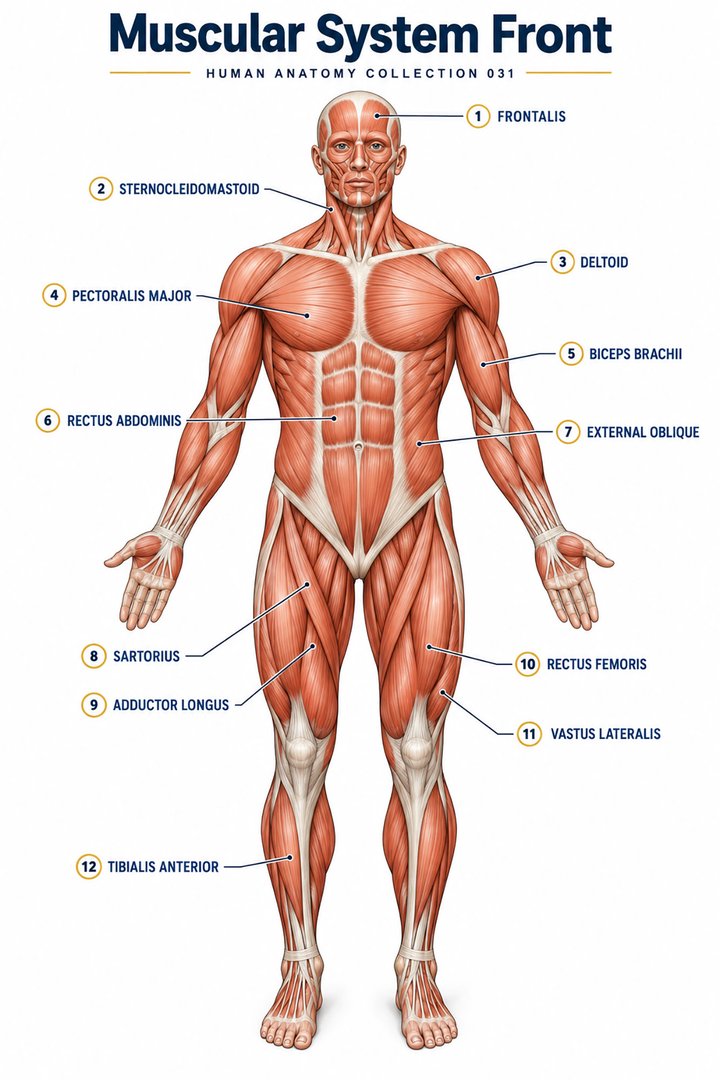 Muscular System Overview ↗
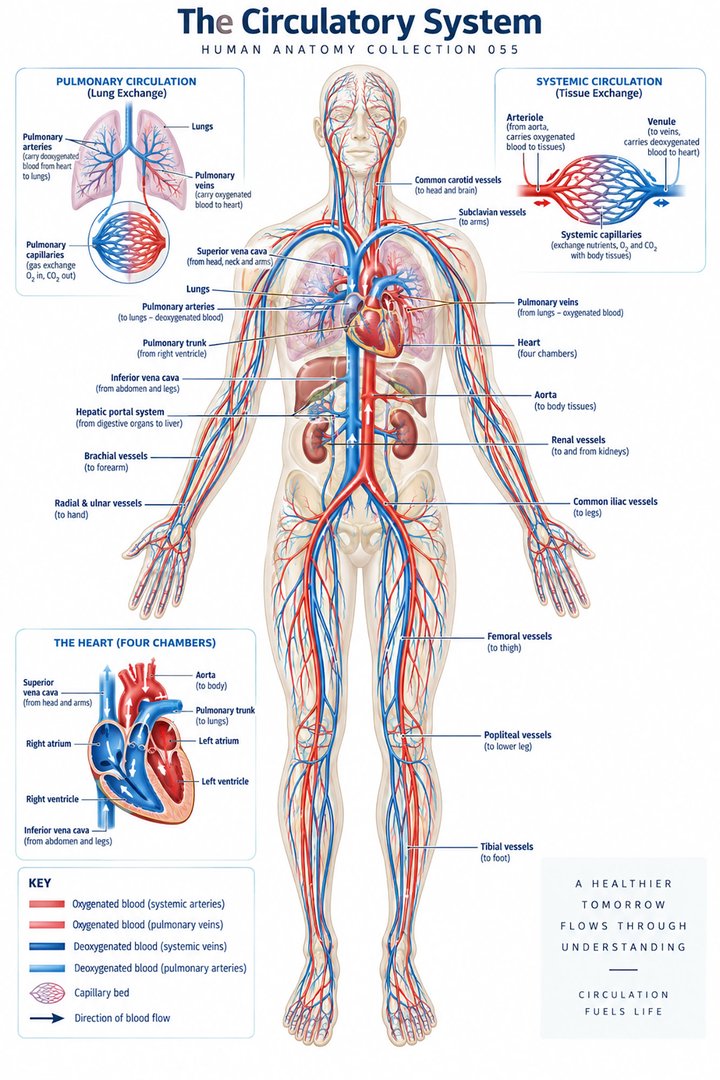 Human Circulatory System ↗
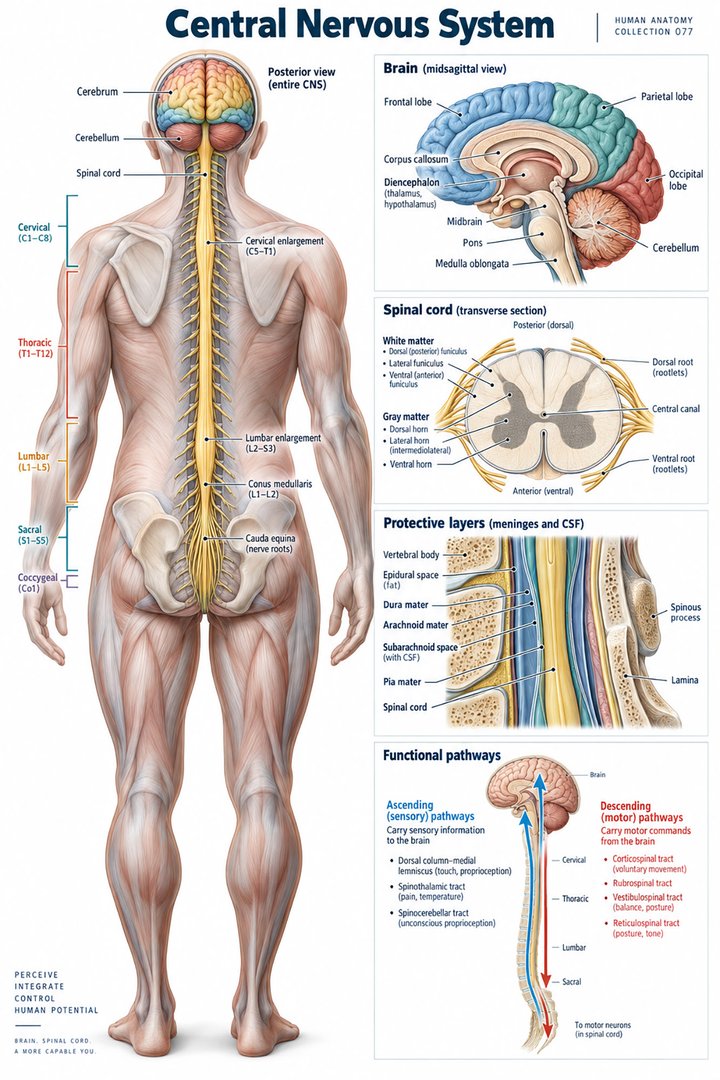 Human Nervous System ↗
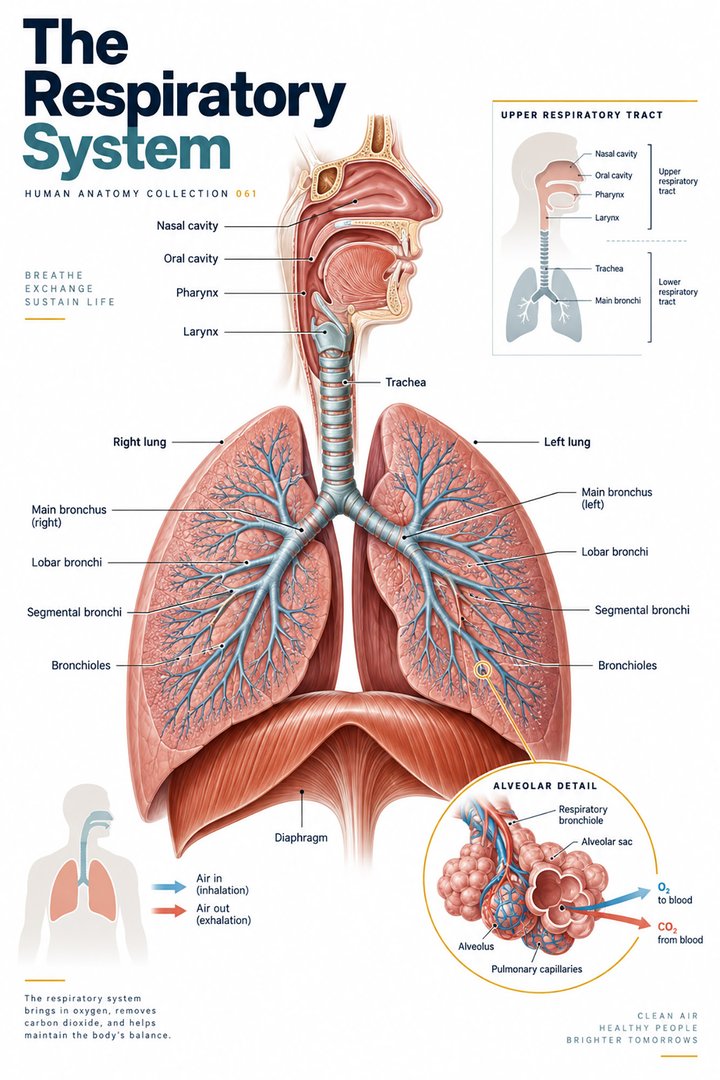 Respiratory System Functions ↗
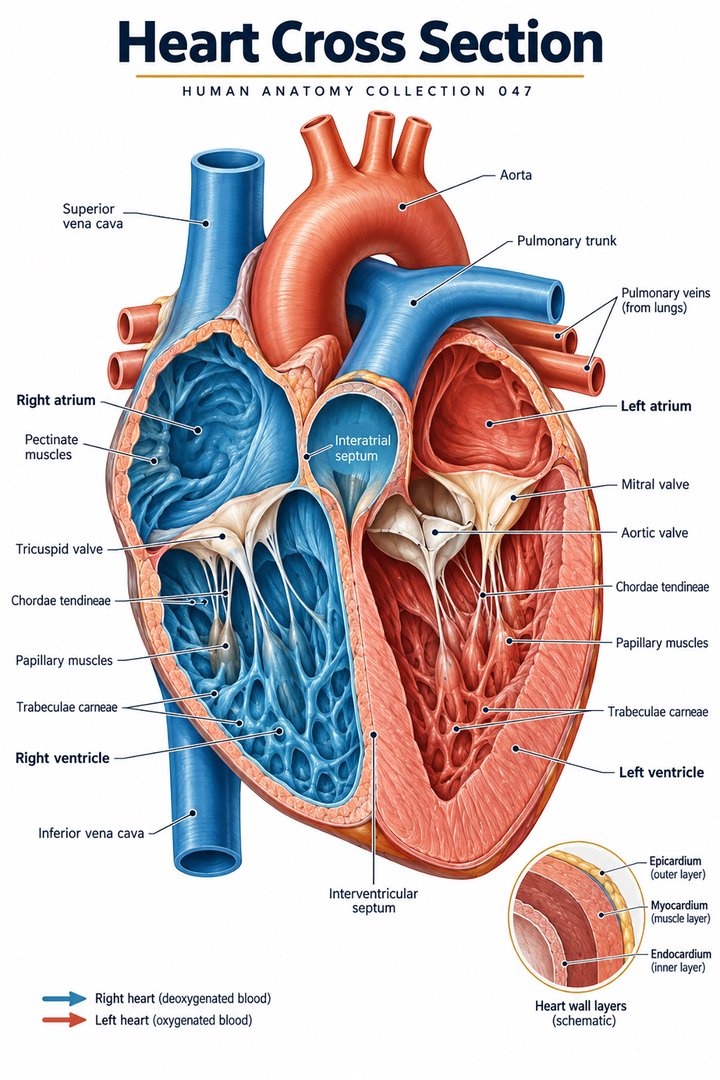 Human Heart Structure ↗
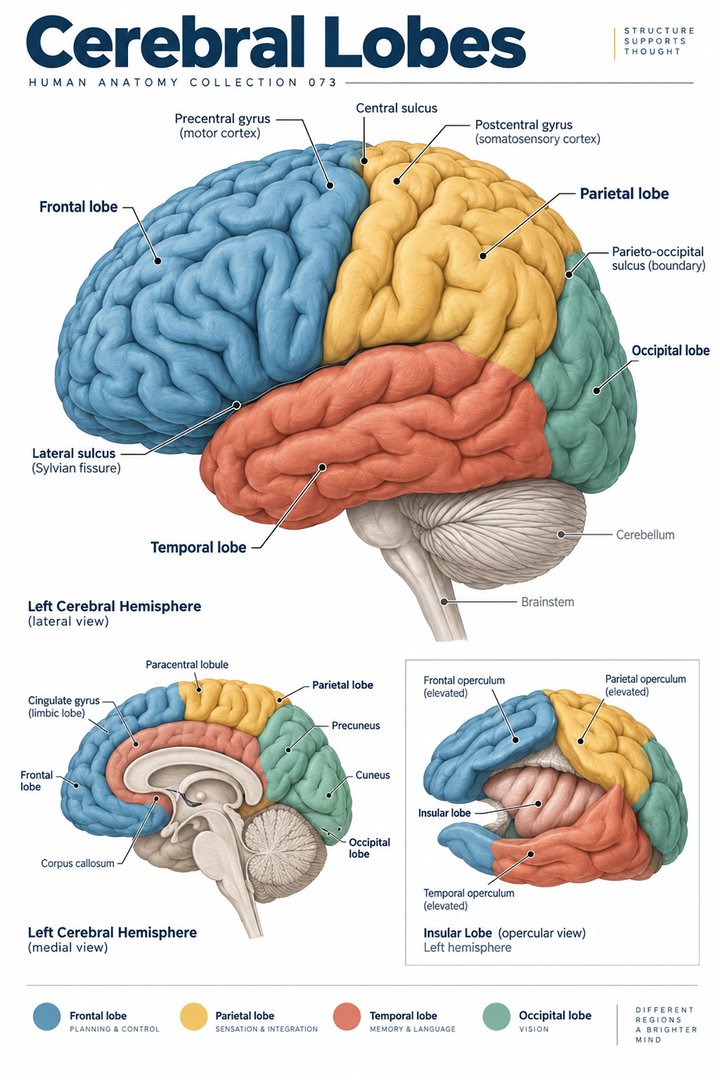 Human Brain Lobes ↗
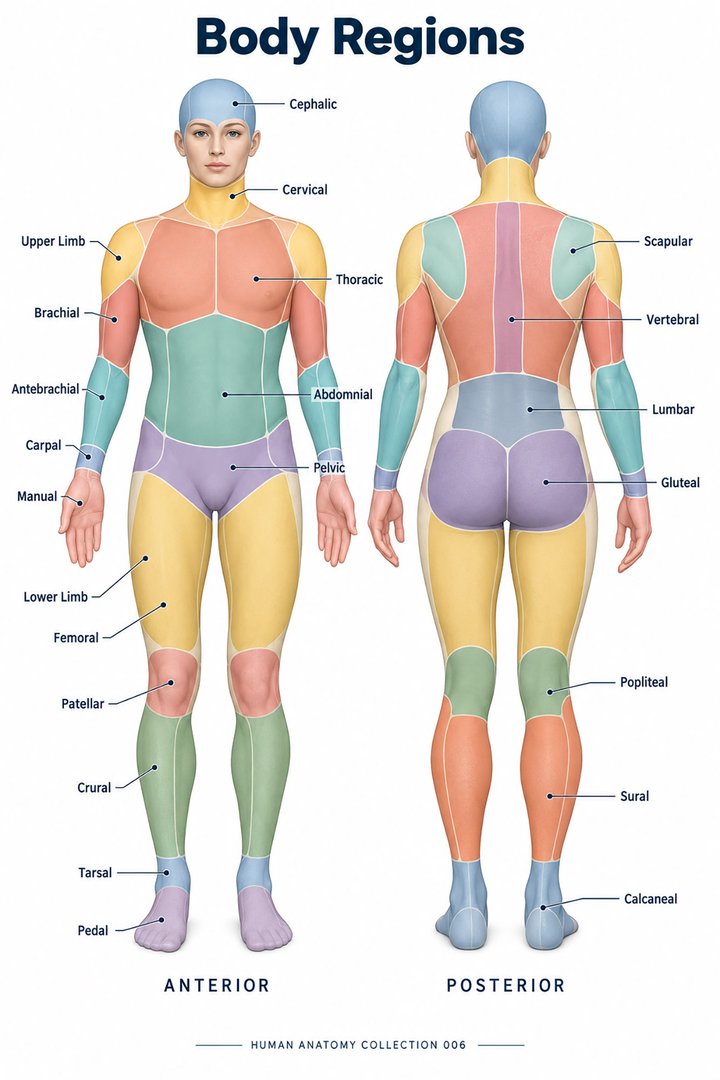 Human Body Parts ↗
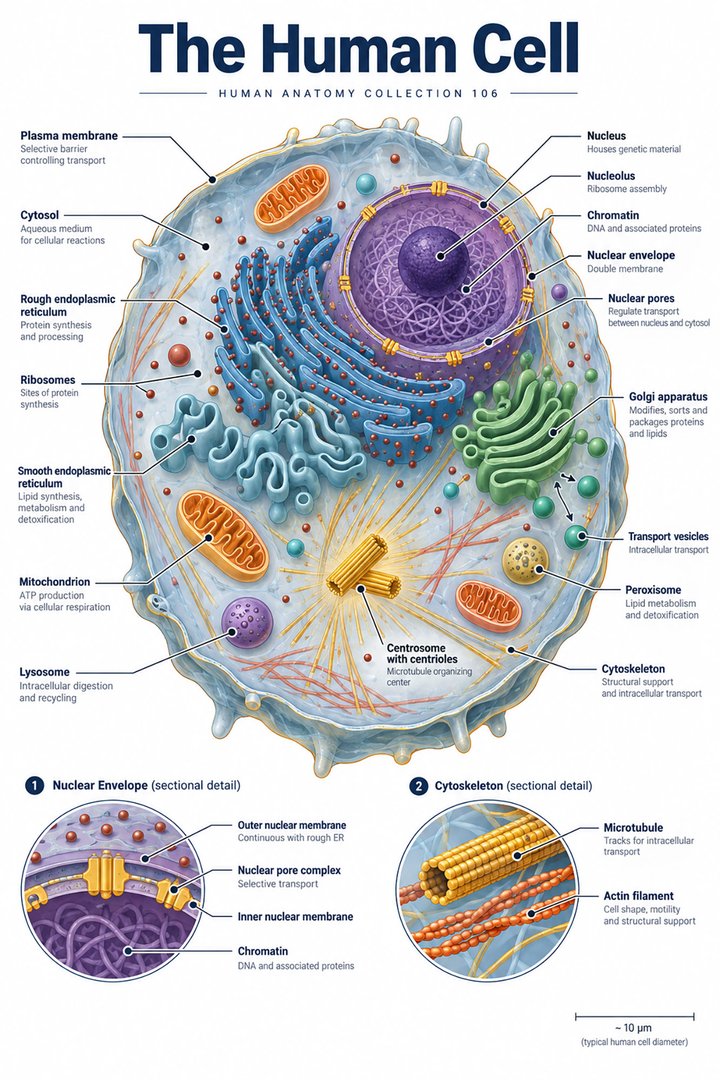 Human Cell Structure ↗
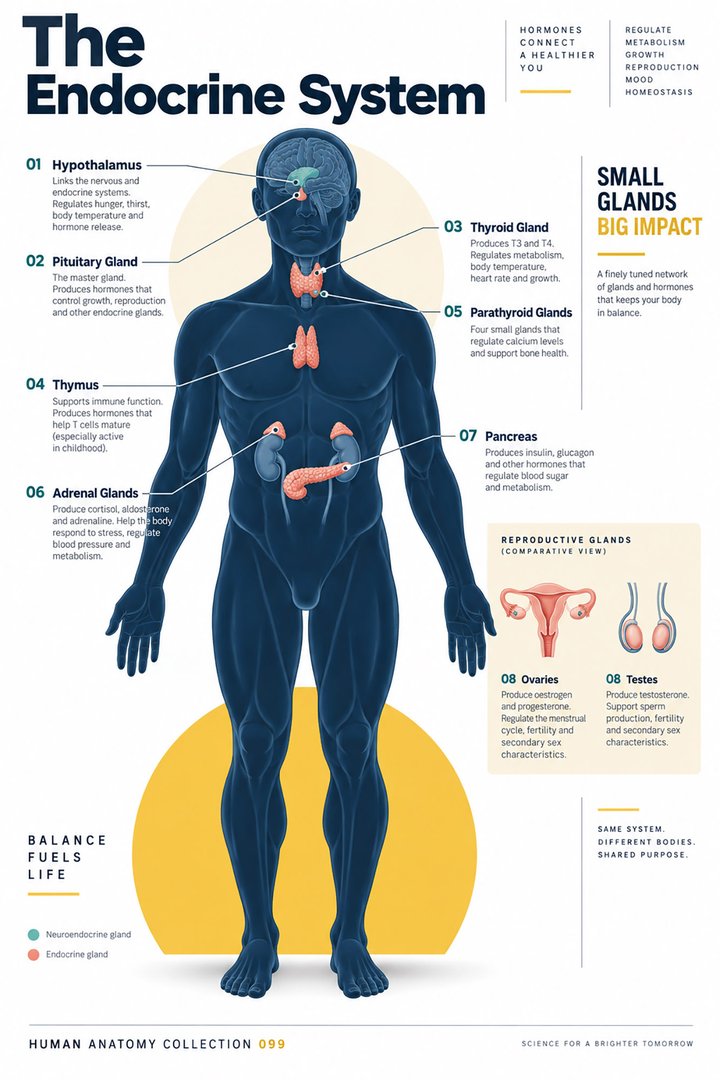 Human Endocrine System ↗
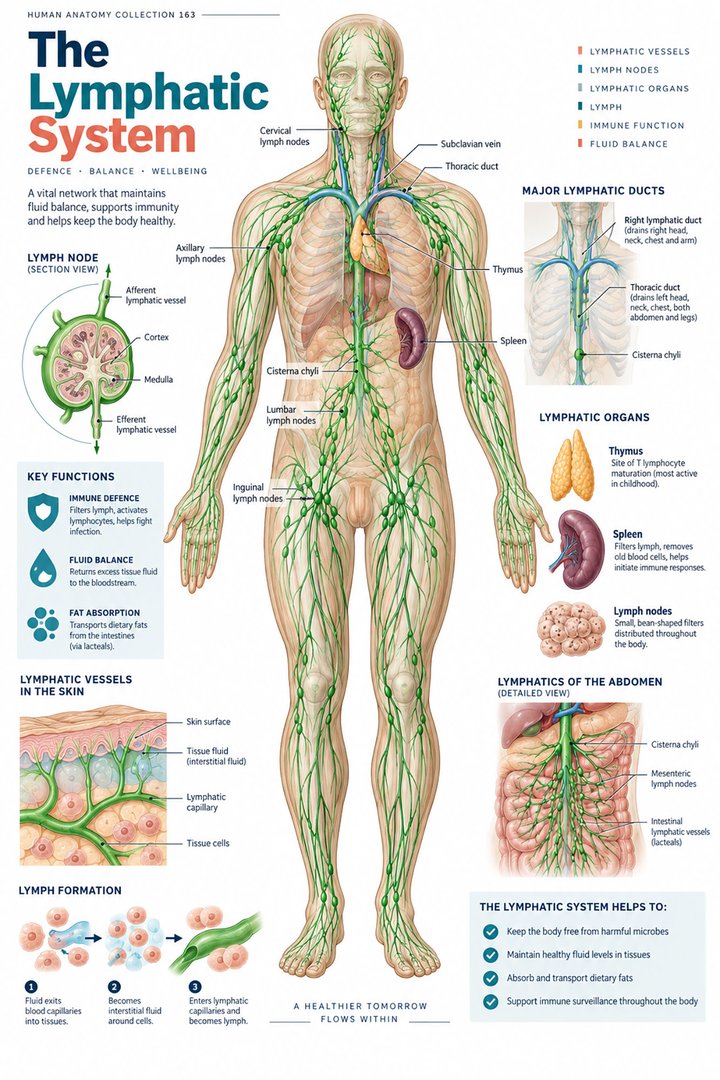 Human Lymphatic System ↗
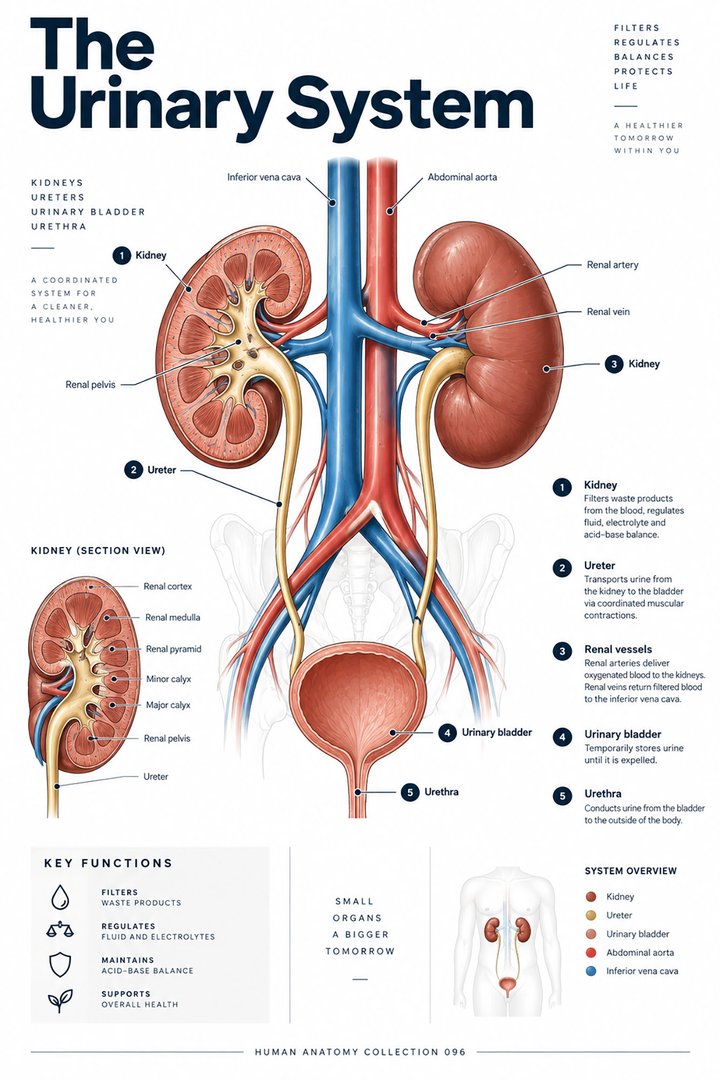 Human Urinary System ↗
 Male Reproductive System ↗
 Female Reproductive System ↗
 Human Immune System ↗Central Nervous System ↗
 Human Eye Structure ↗
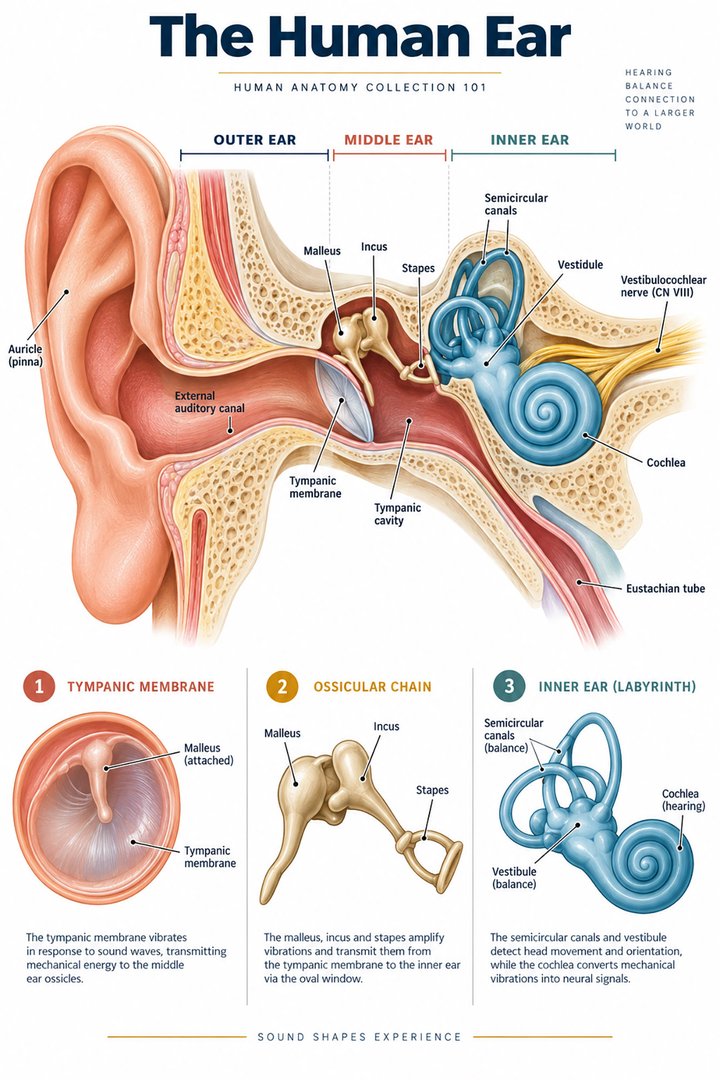 Human Ear Structure ↗
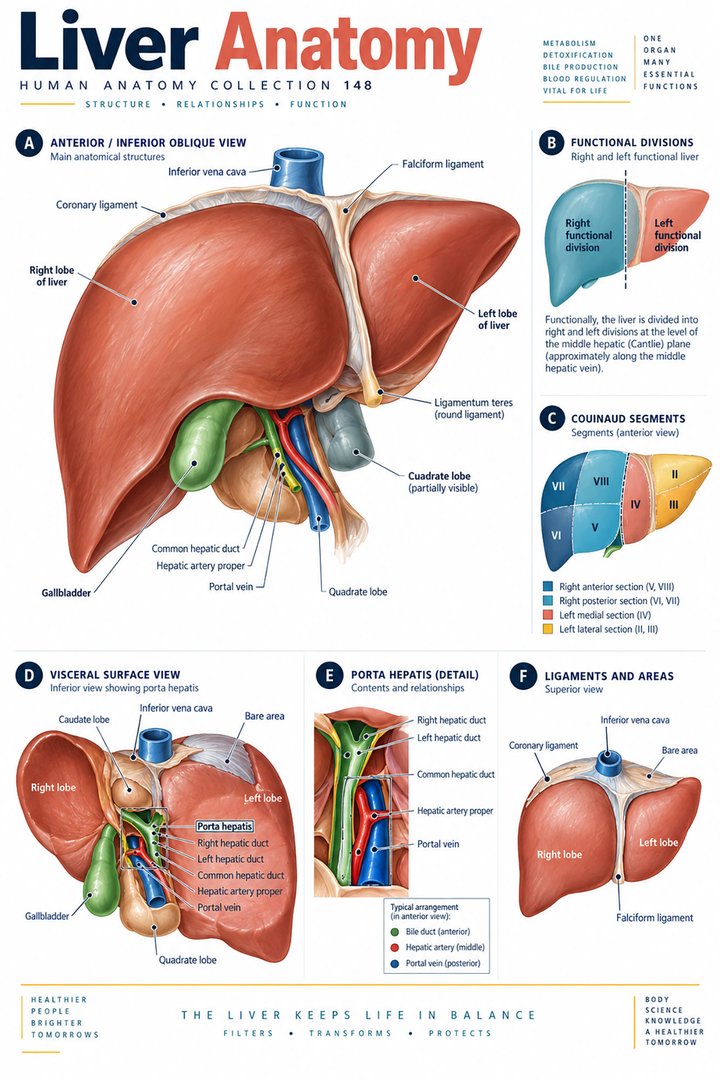 Human Liver Function ↗
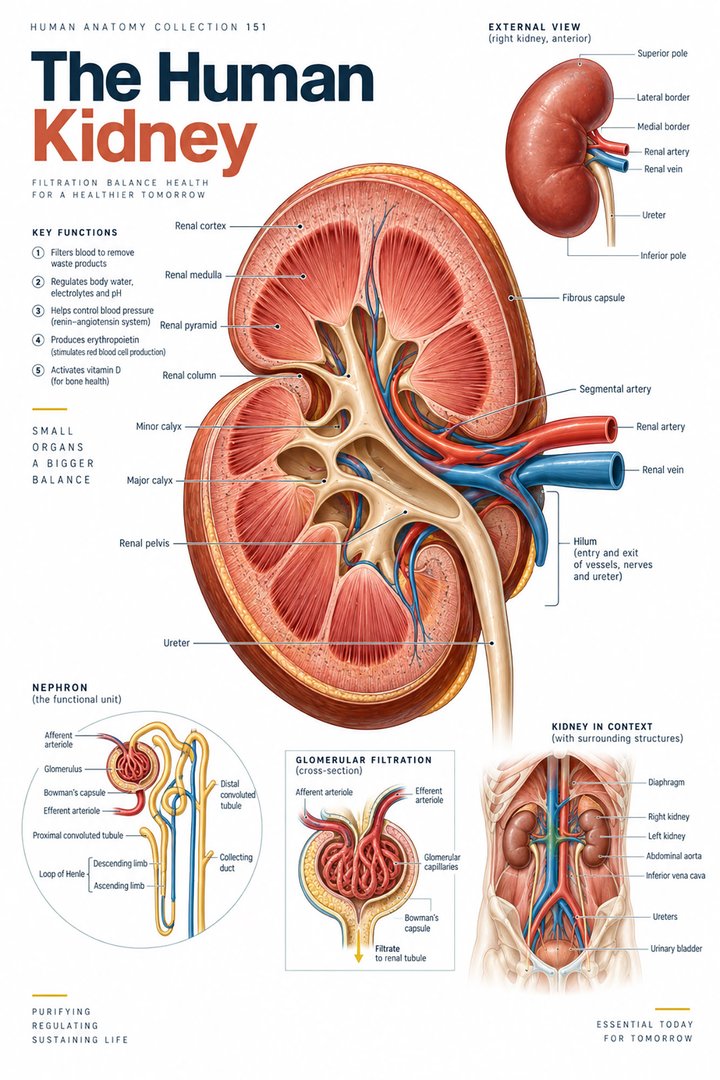 Human Kidney Anatomy ↗
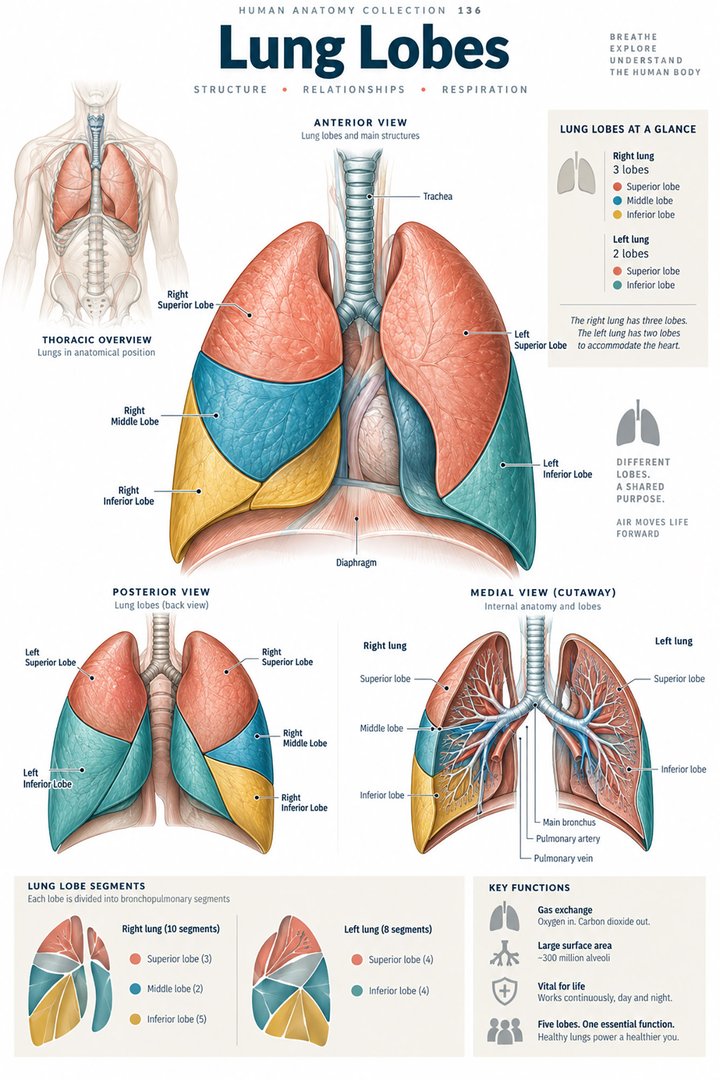 Human Lung Anatomy ↗
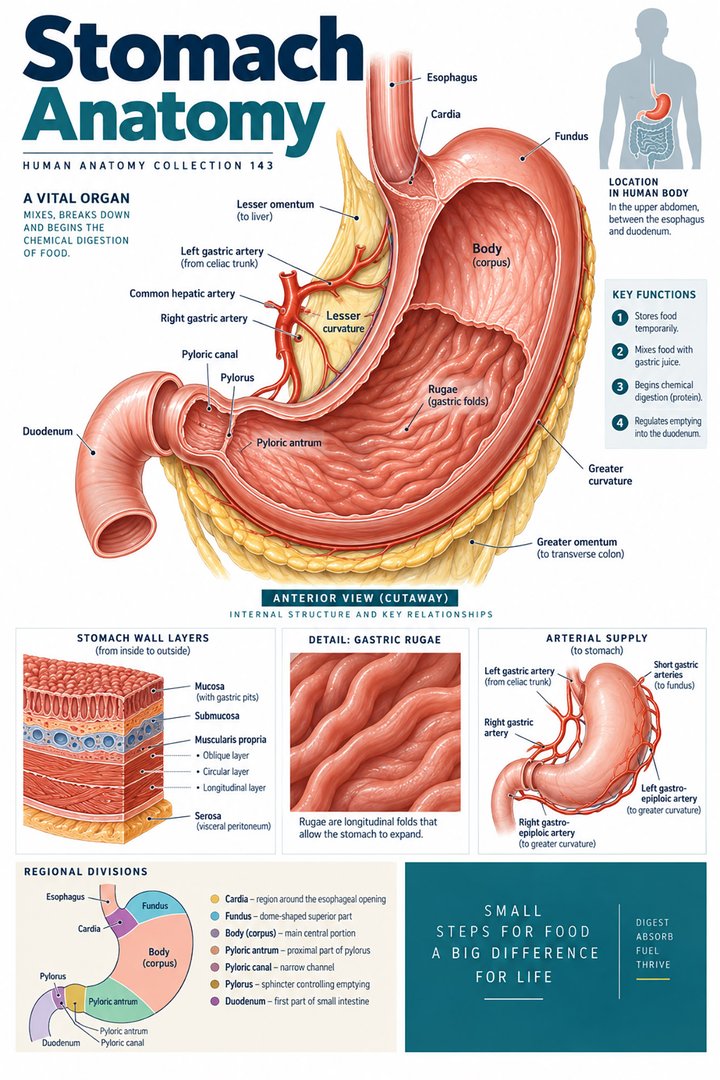 Human Stomach Structure ↗
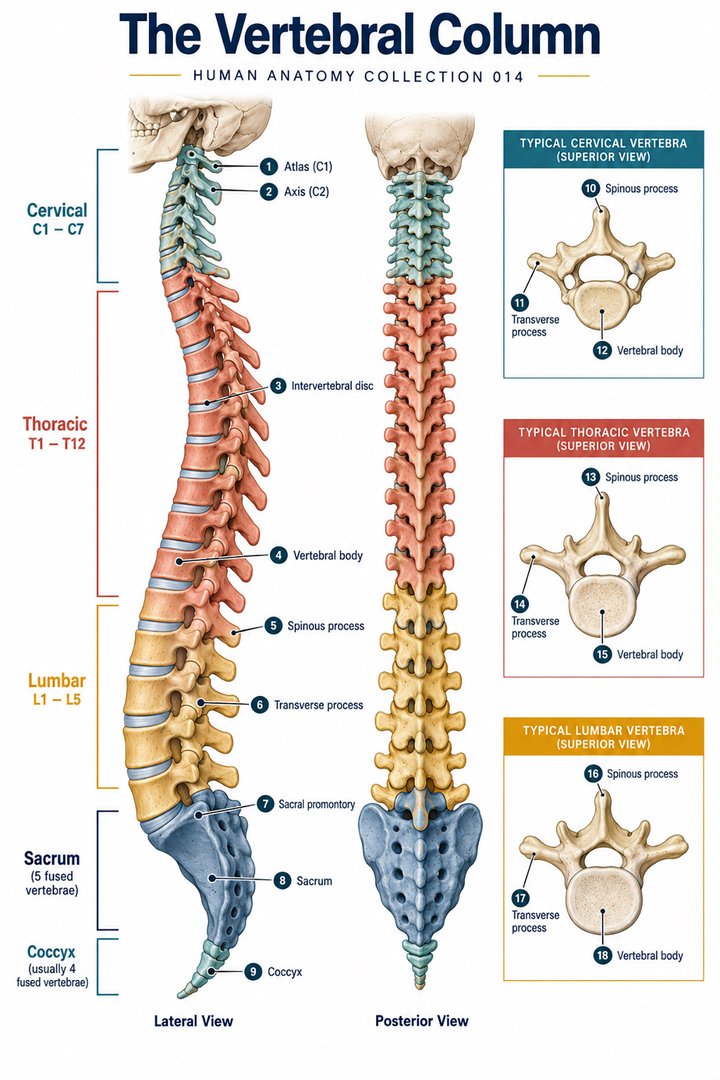 Human Spine Anatomy ↗
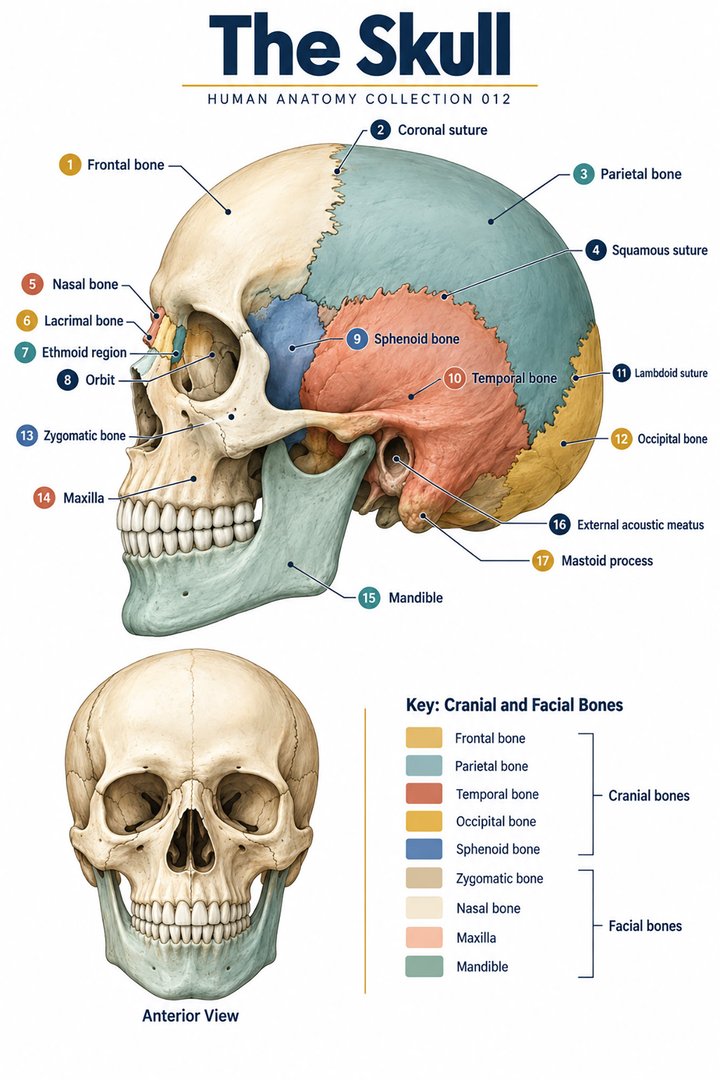 Human Skull Anatomy ↗
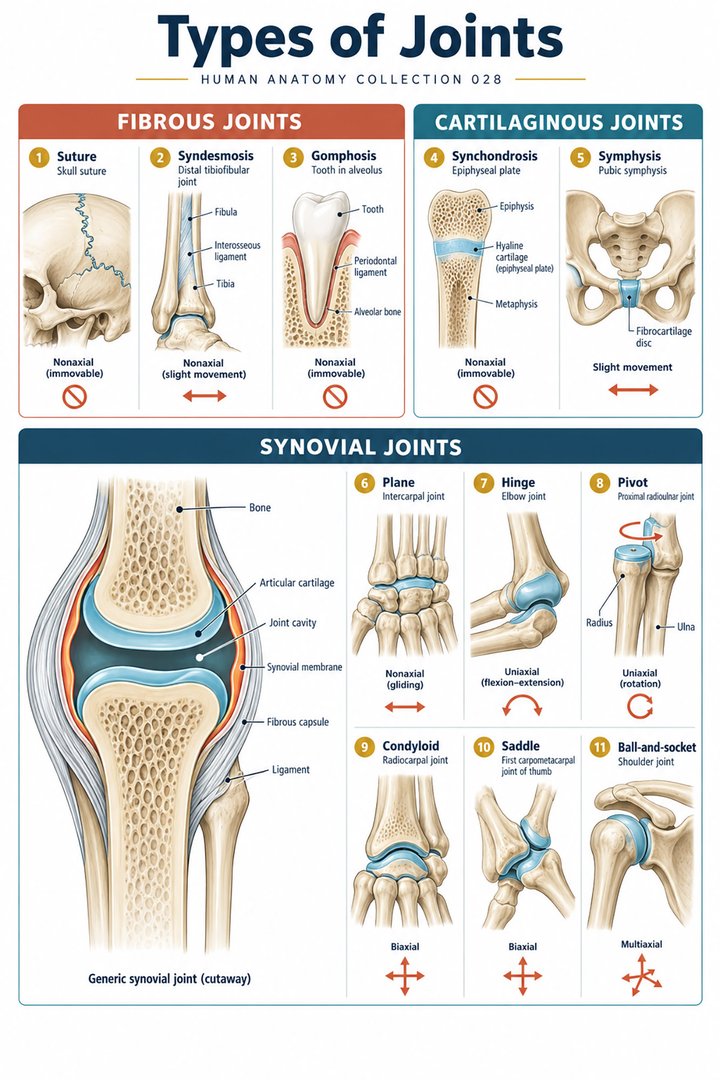 Human Joint Types ↗
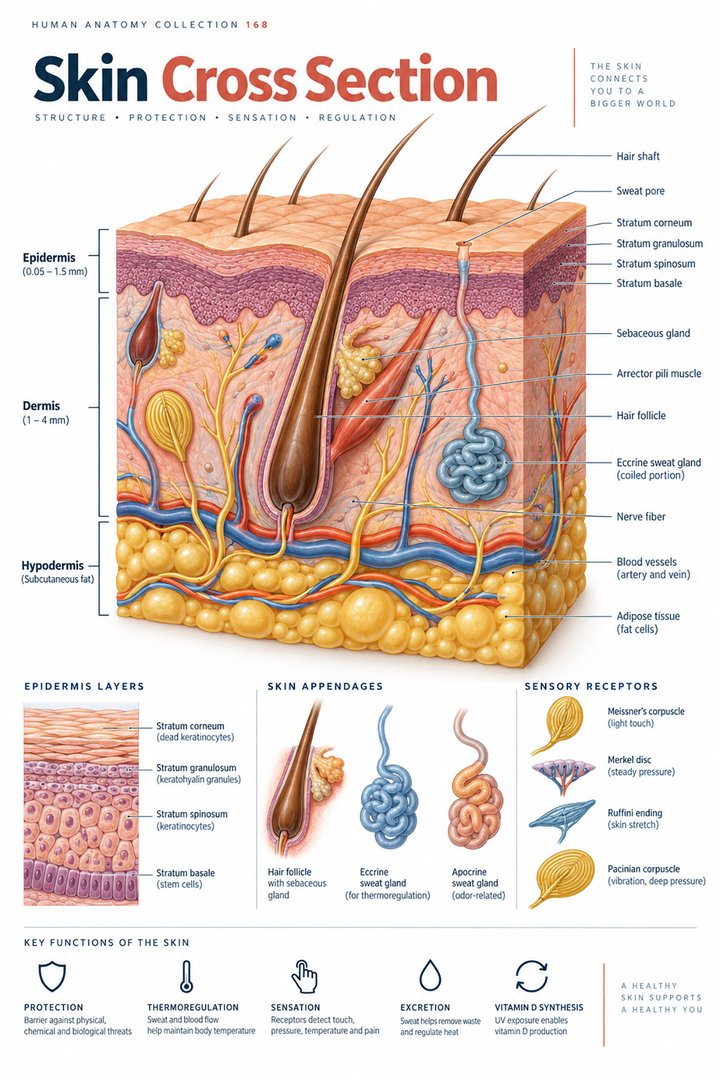 Human Skin Layers ↗
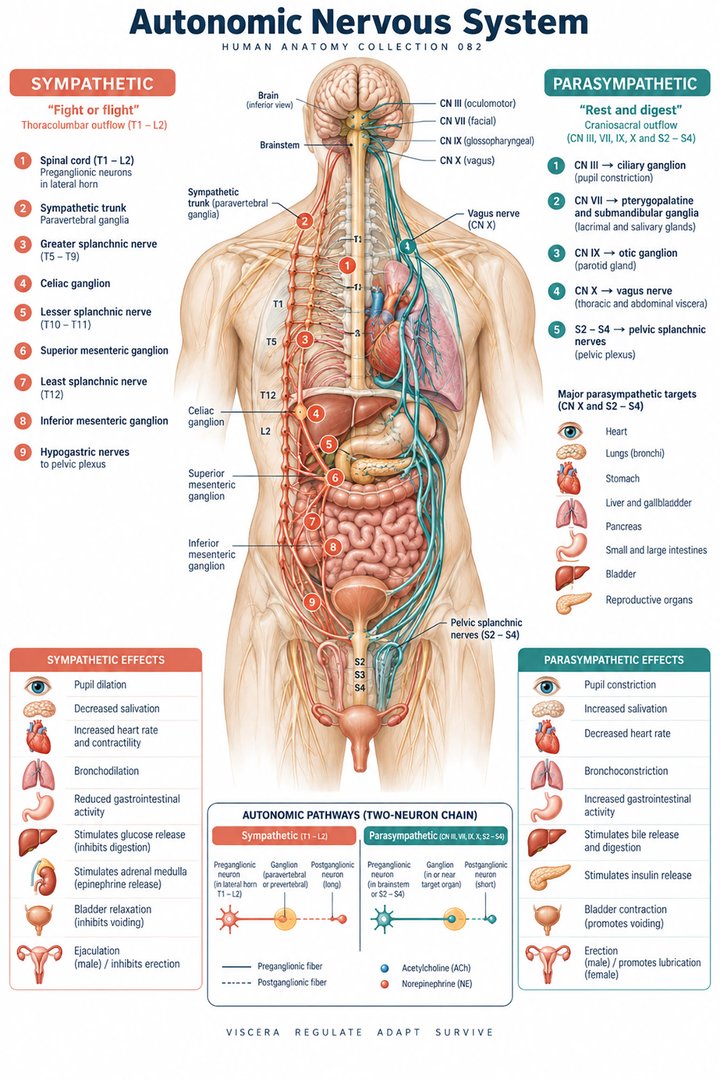 Autonomic Nervous System ↗
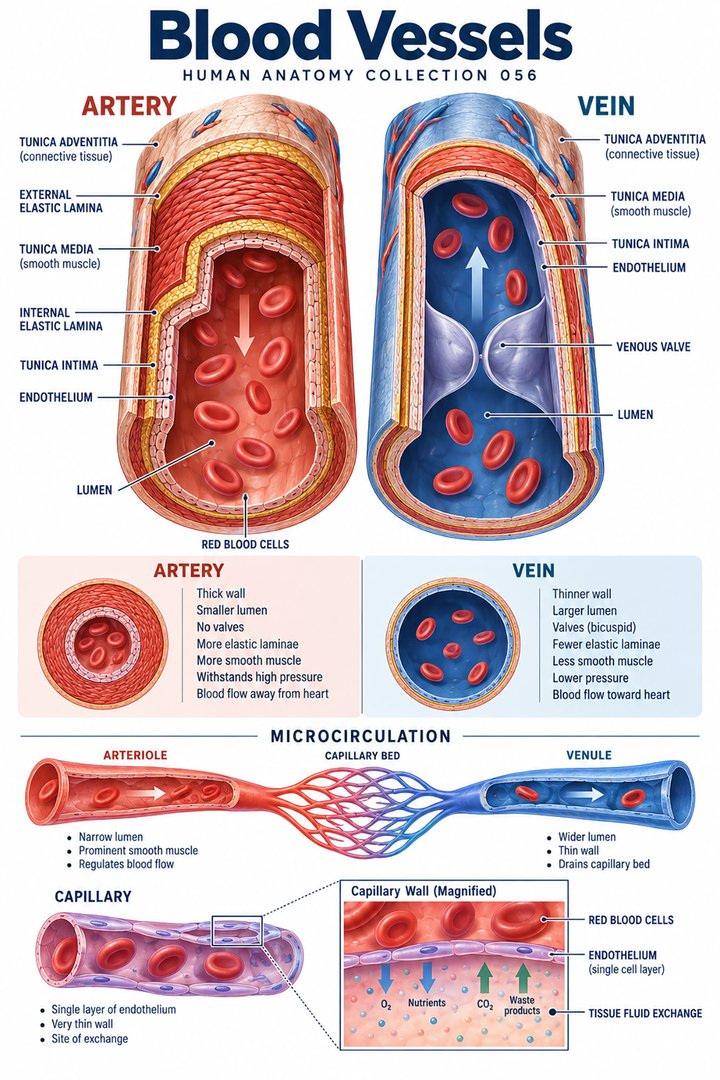 Human Blood Vessels ↗
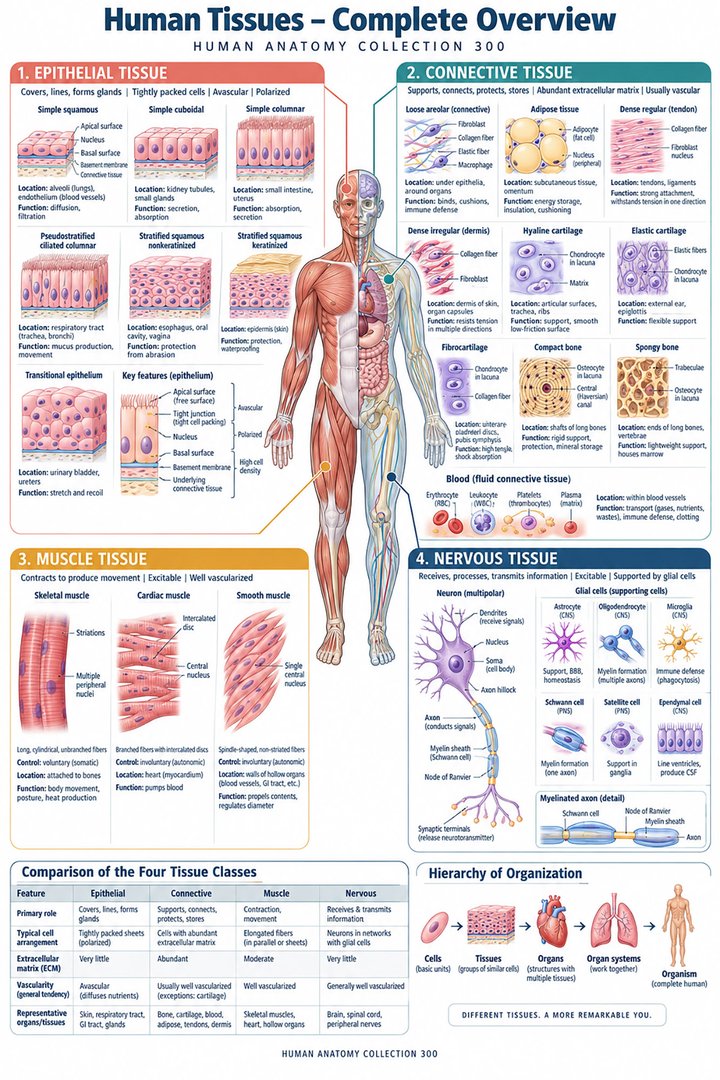 Human Body Tissues ↗
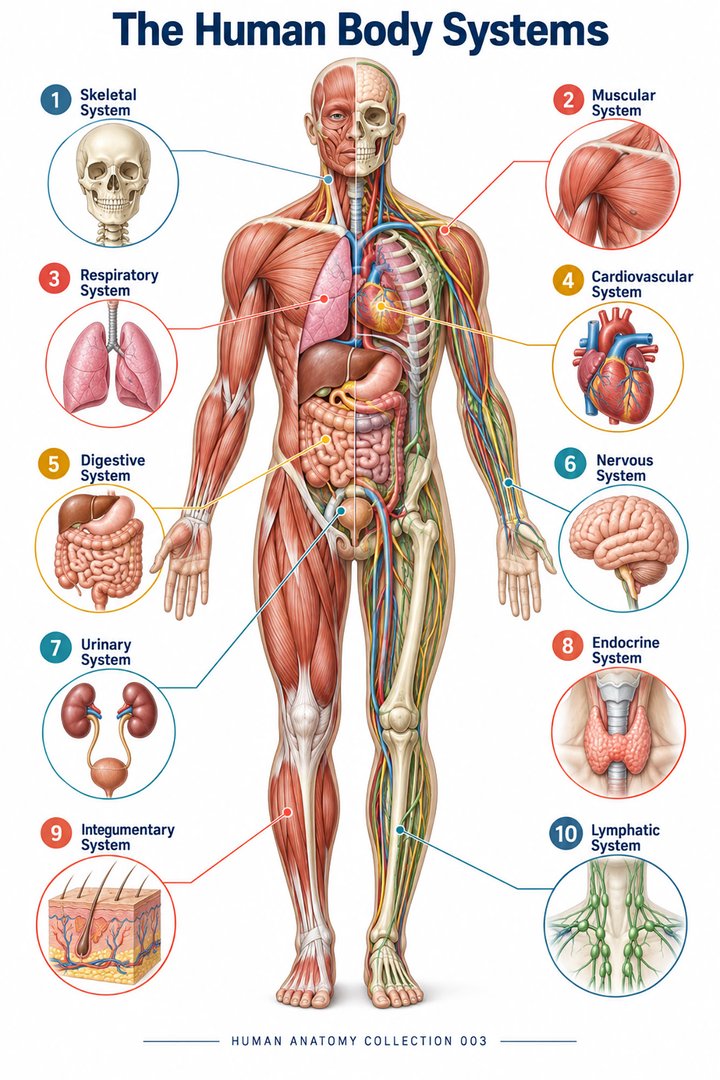 Human Body Systems ↗
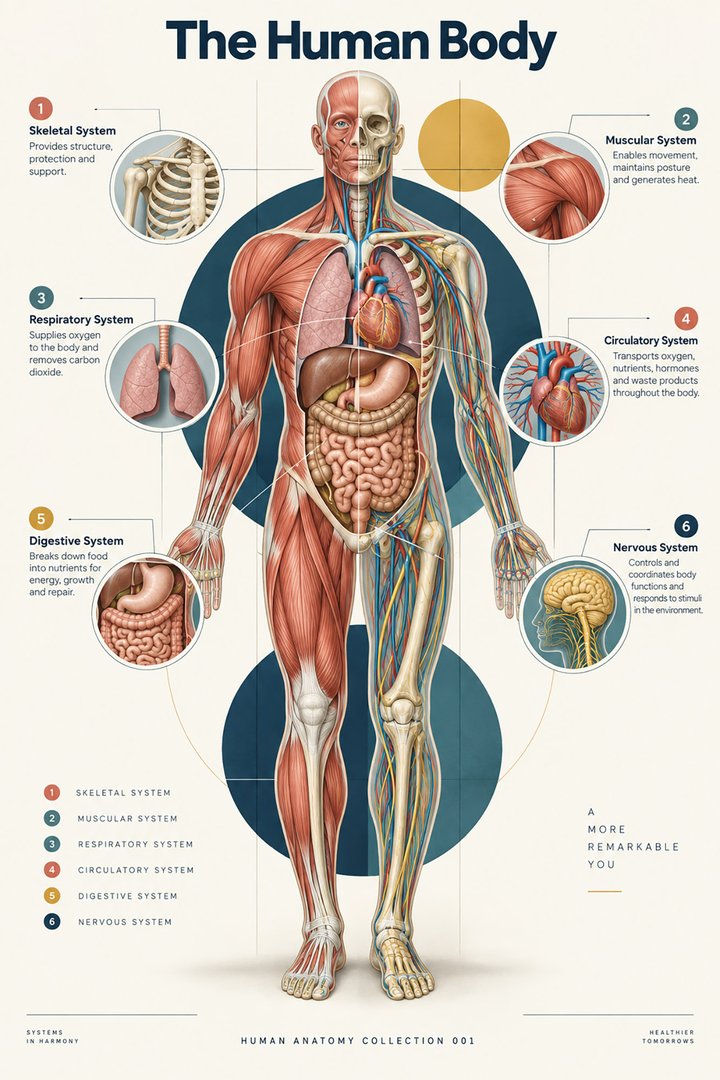 Human Body Facts ↗Human Anatomy and Physiology ↗
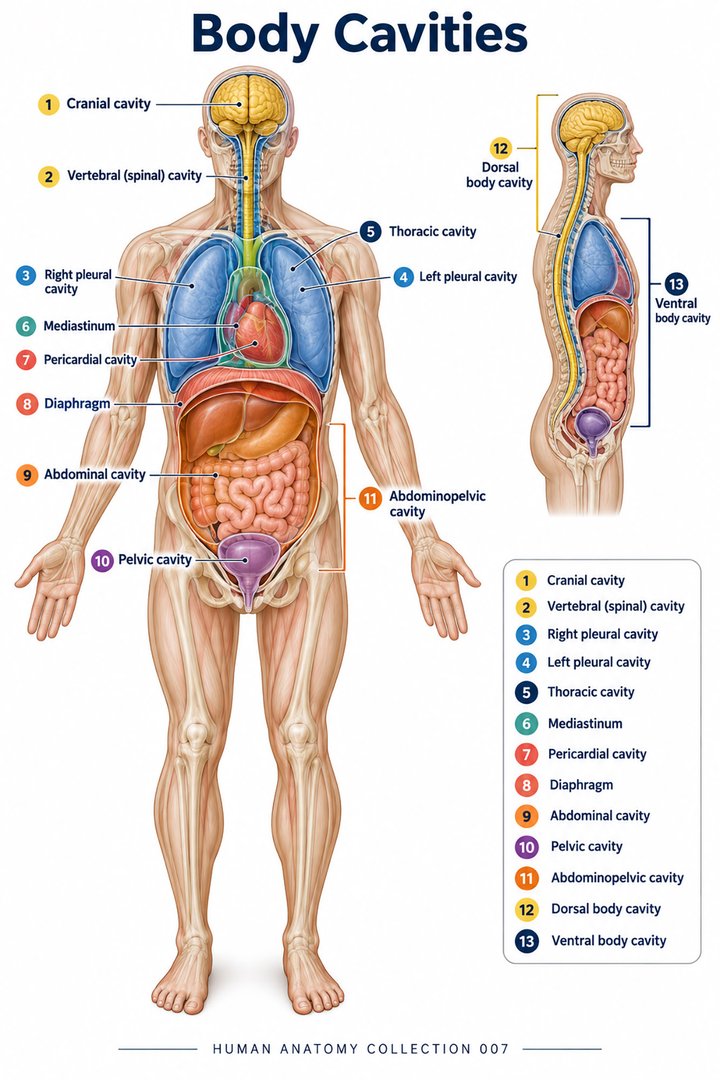 Human Body Cavities ↗Human Torso Anatomy ↗Human Digestive Tract ↗
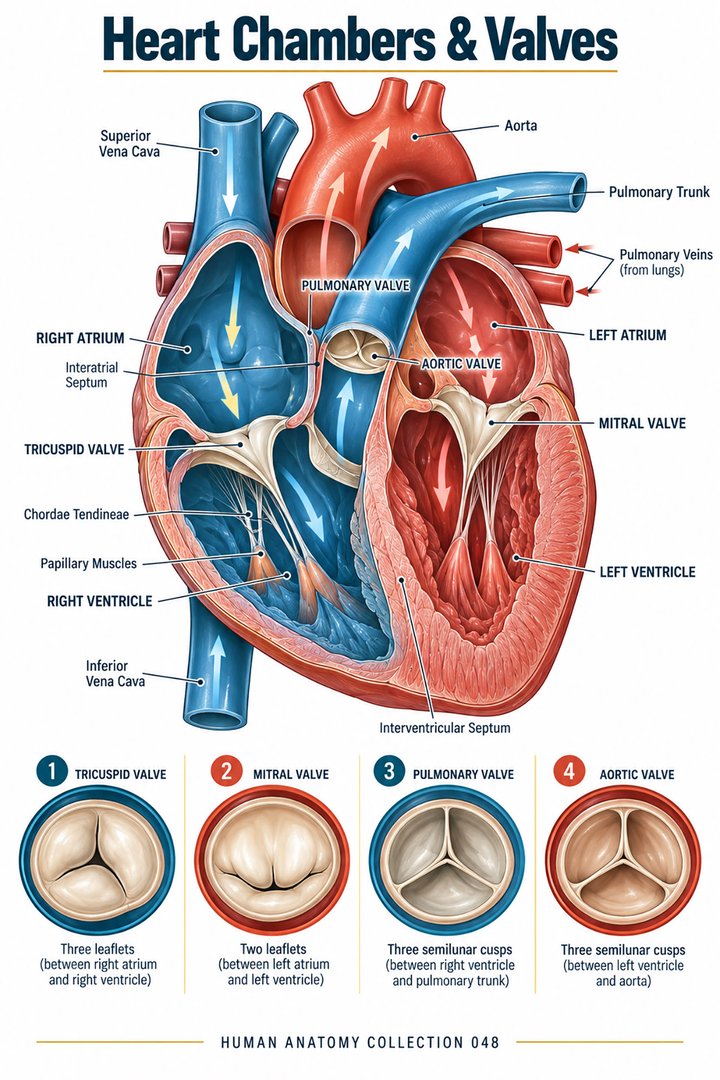 Human Heart Chambers ↗Human Organ Placement ↗
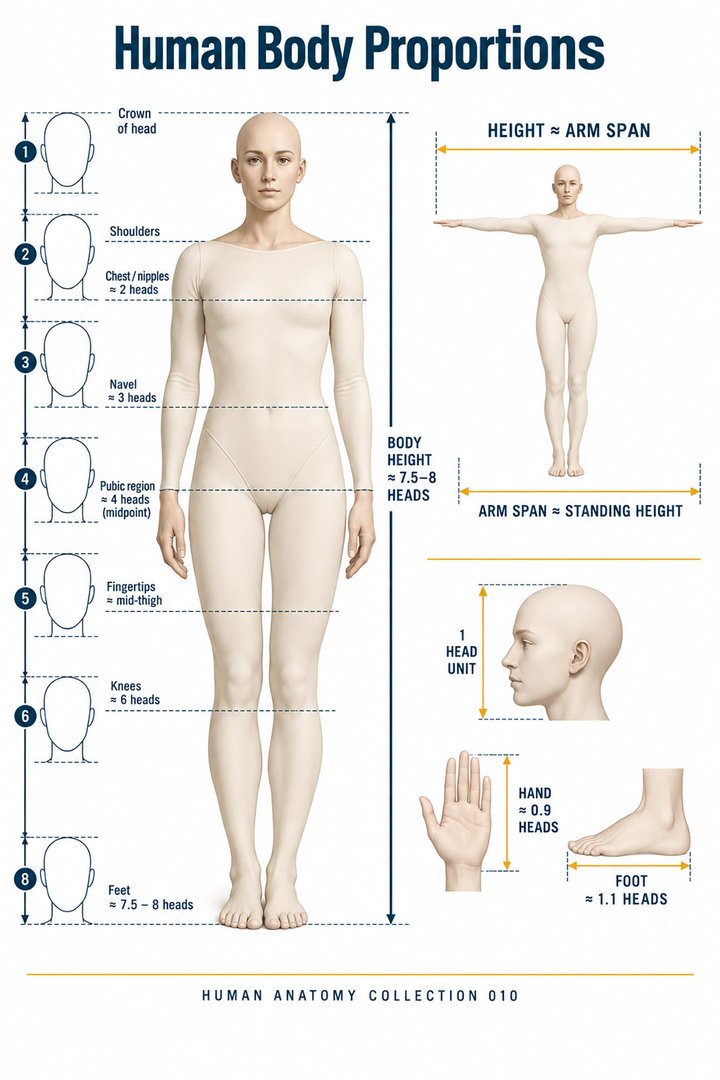 Human Body Proportions ↗
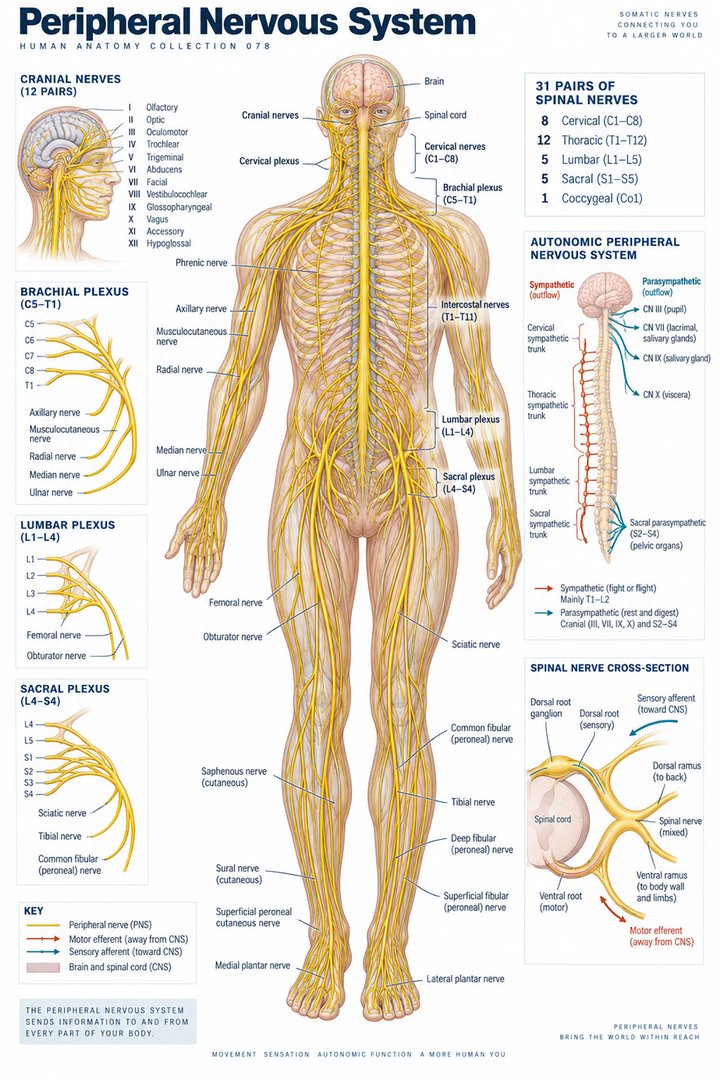 Peripheral Nervous System ↗Human Endocrine Glands ↗
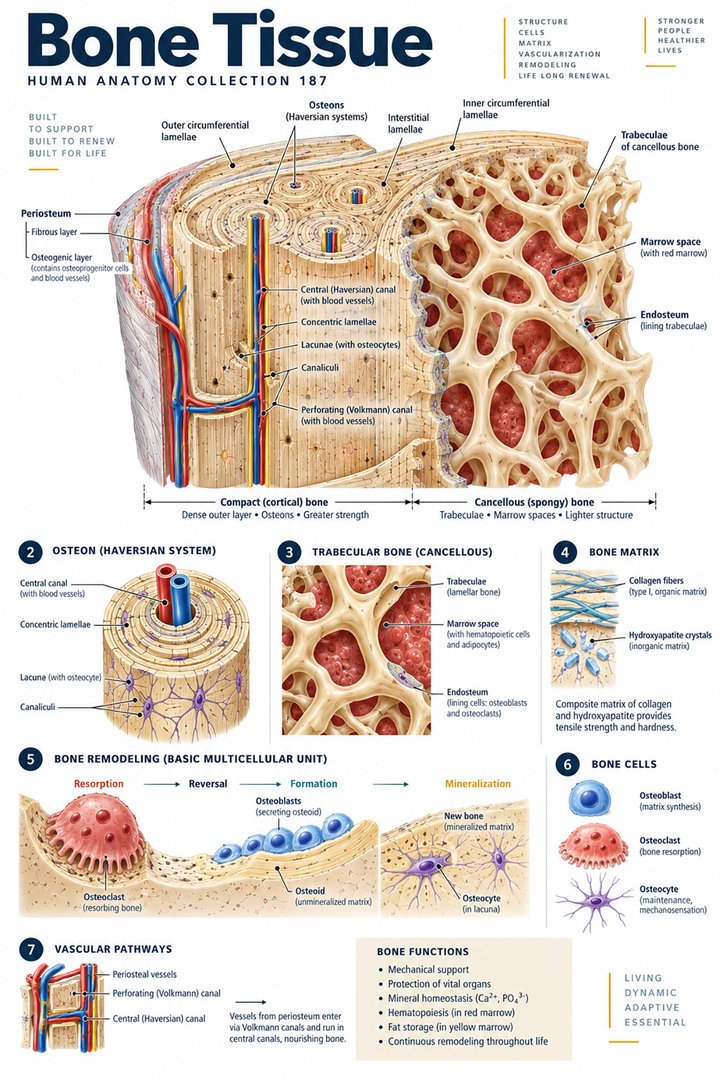 Human Bone Density ↗Human Blood Circulation ↗
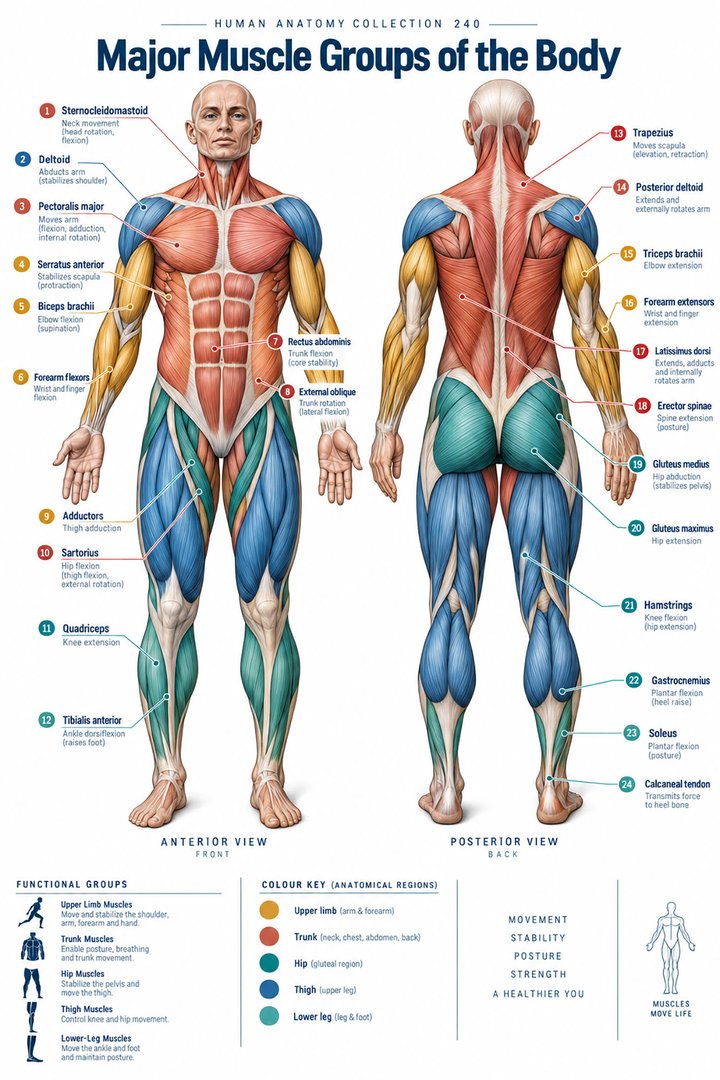 Human Muscle Groups ↗
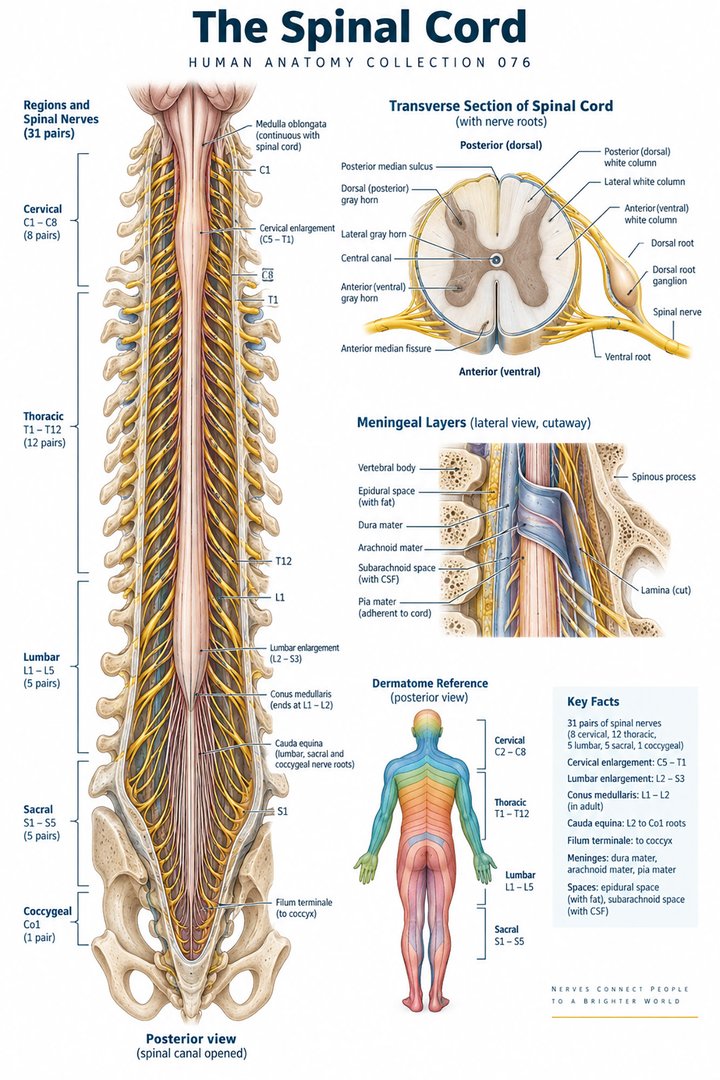 Human Spinal Cord ↗
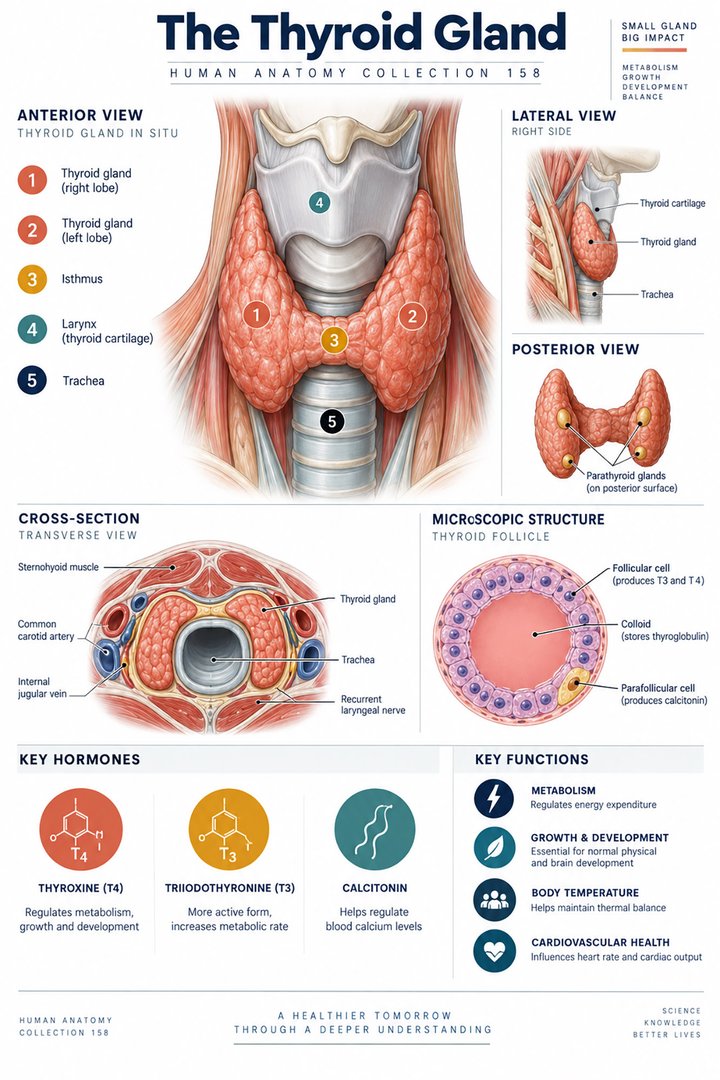 Human Thyroid Gland ↗
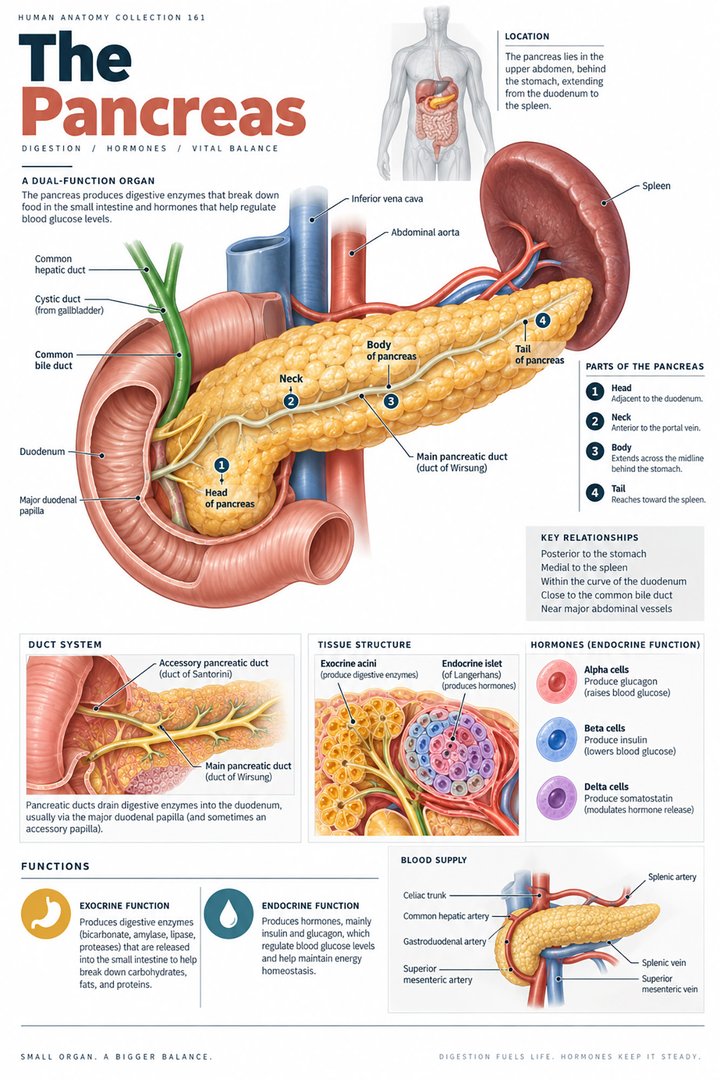 Human Pancreas Function ↗
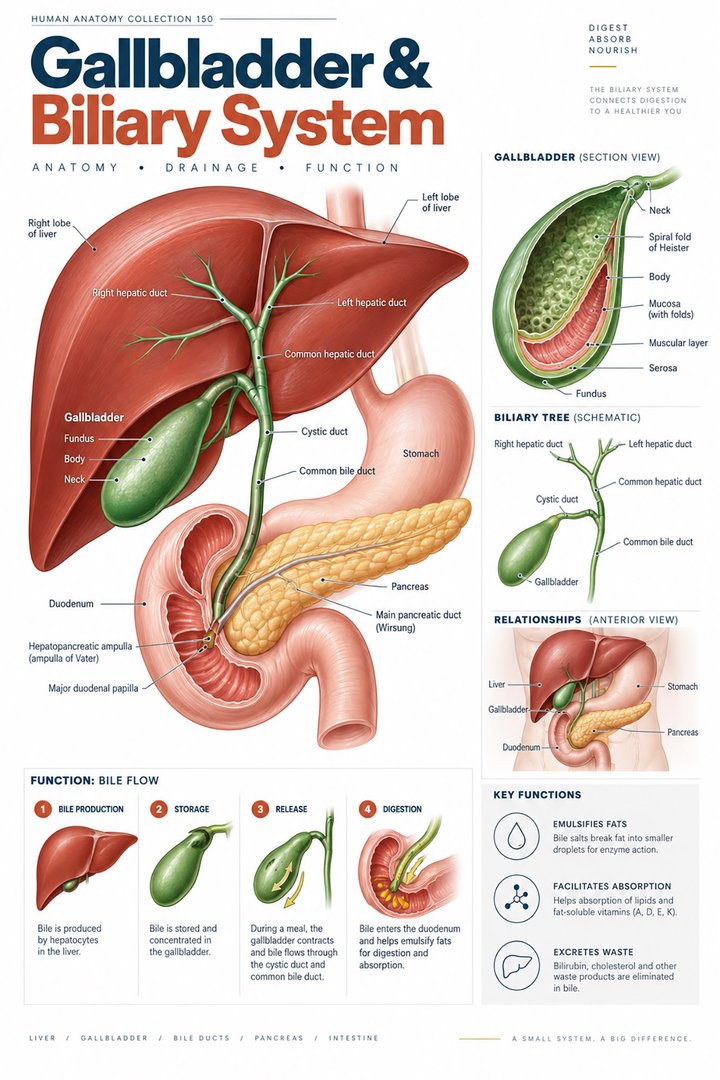 Human Gallbladder Anatomy ↗