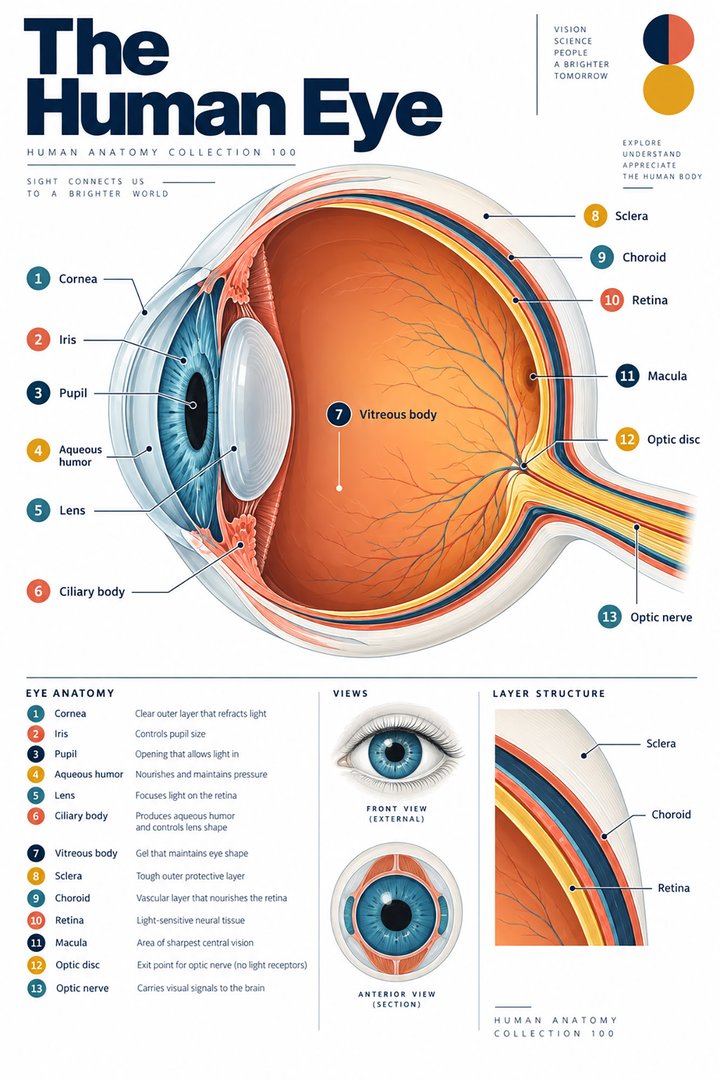
The Human Eye
Individual poster · 300 DPI print files
Regular $9.90
Explore poster ↗$4.90USD
Offer price · Save $5.00Individual poster · 300 DPI print files
Reduced web preview. Separate high-resolution print files are supplied with the digital download.
ANATOMY 100
A modern anatomy illustration exploring the human eye, designed for educational and decorative use.
Purchases are not available yet. Checkout and download delivery are being prepared.
Sold by Kunstolymp.de · Germany
Compare prices & the complete collection ↗This is a DIGITAL DOWNLOAD. No physical product will be shipped. After purchase, download your files and print them at home, at a local print shop, or through an online professional printing service.
The separate 300 DPI print files are ideal for 24×36-inch posters (approximately 60×90 cm). ISO and 5×7 formats are included. The white border lets you adjust the layout or trim to fit other frame sizes; check the preview before printing to keep the illustration and labels visible.
The planned bundle delivery includes a PDF information sheet with a link to the relevant Google Drive folder and download instructions. The store is currently in preview and purchases are not yet available.
A science-inspired choice for a student’s study corner, an educator’s classroom, or an anatomy enthusiast’s wall. Final licensing terms will apply.
CLINICAL CONTEXT
Clear vision depends on an uninterrupted path from the eye surface to the brain. The tear film and transparent cornea provide the first optical surface; the iris controls pupil size, and the lens adjusts focus onto the retina. Photoreceptors convert light into electrical signals that travel through retinal circuits and the optic nerve. The macula supports central detail, while the peripheral retina contributes to the wider visual field. Aqueous humour circulates in the anterior segment, and its drainage helps regulate eye pressure. The vitreous occupies the space behind the lens. Eyelids, ocular muscles, and supporting tissues protect the globe and coordinate gaze. Understanding these relationships helps connect a patient's symptom with possible sites of disease, without treating a diagram as a diagnostic test.
Myopia, hyperopia, astigmatism, and presbyopia alter how light is focused and can cause blurred distance or near vision, eye strain, and difficulty reading. Dry eye may produce burning, grittiness, redness, or intermittent blur, especially during prolonged screen use. Cataract is clouding of the lens and commonly causes gradual visual haze, glare, reduced colour clarity, and difficulty seeing at night. Glaucoma damages the optic nerve and often develops without noticeable early symptoms; normal central vision does not exclude it. Acute angle closure can instead cause intense pain, redness, blurred vision, and nausea. Retinal detachment may cause new flashes, numerous floaters, or a shadow across vision. These patterns help prioritise assessment, but symptoms can overlap and require examination.
Ask when symptoms began, whether one or both eyes are affected, and whether change is sudden, progressive, constant, or intermittent. Clarify pain, light sensitivity, discharge, new floaters, field loss, contact-lens use, trauma, medicines, diabetes, and previous eye procedures. Record the effect on reading, work, mobility, and driving. Assess visual acuity separately in each eye, with usual correction, and examine pupils, eye movements, and external structures. An eye-care professional may use refraction, slit-lamp examination, tonometry, visual-field testing, and a dilated retinal examination; additional imaging depends on the suspected condition. Eye pressure alone neither establishes nor excludes glaucoma. Urgent symptoms require prompt referral rather than waiting for a routine prescription check.
Refractive errors are managed with appropriate spectacles, contact lenses, or selected refractive procedures after assessment. Dry-eye care may include artificial tears, changes to the environment, and prescription treatment according to severity and cause. Cataract surgery replaces the cloudy lens when its effect on daily function warrants intervention; improved lighting and an updated prescription may help earlier symptoms. Glaucoma care uses pressure-lowering drops, laser, or surgery to protect remaining vision, with continuing monitoring and support for adherence. Retinal detachment requires urgent specialist care and may need laser or surgery. For persistent visual impairment, magnification, accessible information, improved lighting, and vision rehabilitation can support independence.
Regular screen breaks, avoiding direct airflow towards the eyes, and suitable lighting can support comfort. Smoking cessation, protective eyewear, and regular eye examinations are useful parts of eye-health care. A varied diet supports general health, but supplements are not universal treatment for eye disease. AREDS2 formulations are intended for particular stages of age-related macular degeneration after professional assessment; they do not prevent AMD in healthy eyes or treat cataract or glaucoma. Review high-dose supplements and potential interactions with a clinician. Avoid unregulated or non-sterile eye products and do not replace prescribed treatment with a herbal remedy. These supportive measures cannot reattach a retina or reverse established optic-nerve damage.
Seek immediate eye-care or emergency assessment for sudden loss of vision, a new curtain or shadow, or new flashes with a sudden increase in floaters. Severe eye pain with redness, blurred vision, or nausea also needs immediate assessment. Do not assume a painful red eye or a sudden change is ordinary eye strain. Keep scheduled reviews even when symptoms improve, particularly during glaucoma treatment. Explain the treatment plan, expected benefit, and specific reasons to seek help in clear language. This article is for clinical learning and does not replace an individual examination.
Further reading: NEI: refractive errors · NEI: dry eye · NEI: cataracts · NEI: glaucoma · NEI: retinal detachment · NEI: AREDS/AREDS2 supplements
Explain the working diagnosis, important alternatives, planned tests, expected course, and specific safety-netting in language the patient can use. Invite questions about treatment goals, capacity, cost, culture, and complementary therapies. Use a professional interpreter when language access could affect consent or understanding, and confirm clear arrangements for timely clinical review in writing. Document the reasoning, reassess response to treatment, and coordinate care across professions when illness affects more than one system. Teaching anatomy is most useful when it supports this partnership: accurate localisation, respectful listening, timely escalation, and a plan that remains responsive to the individual patient.
HUMAN ANATOMY COLLECTION · 001—300
A closer look at what makes us human. Discover anatomy posters for your study space, classroom, and everyday curiosity.
DIGITAL DOWNLOADS · 300 DPI PRINT FILES
EXPLORE BY SYSTEM
LEARN & EXPLORE
Detailed English guides with Latin terminology, diagrams, real images, and clinical learning connections.
 Human Anatomy Diagrams ↗
 Human Body Organs ↗
 Skeletal System Anatomy ↗
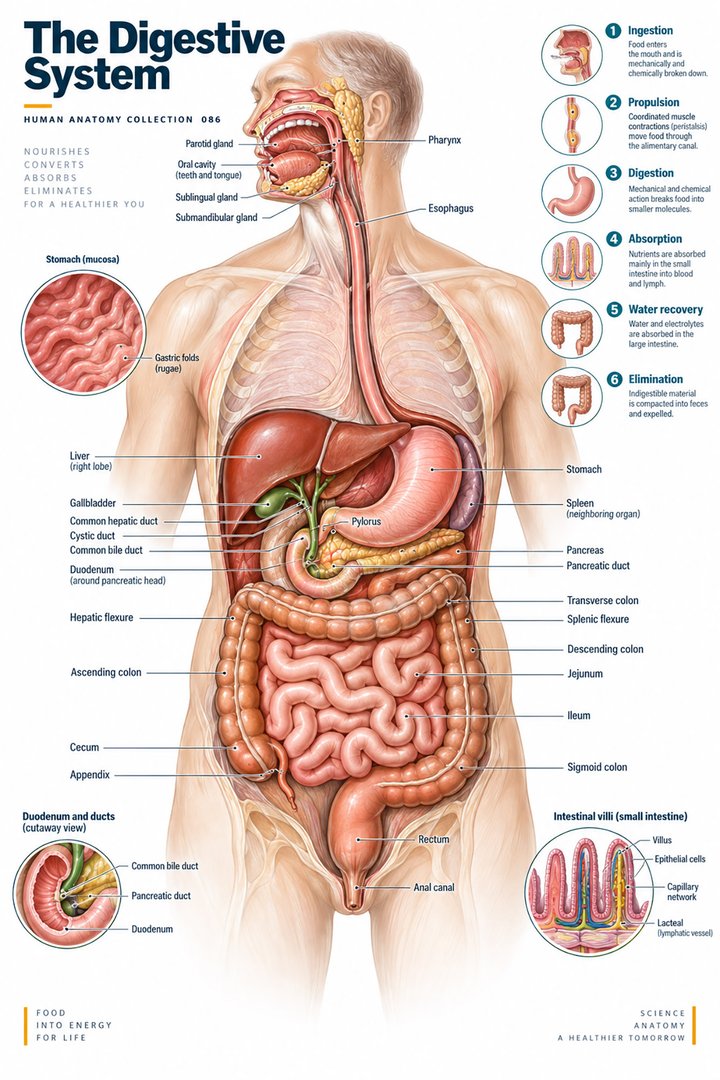 Human Digestive System ↗
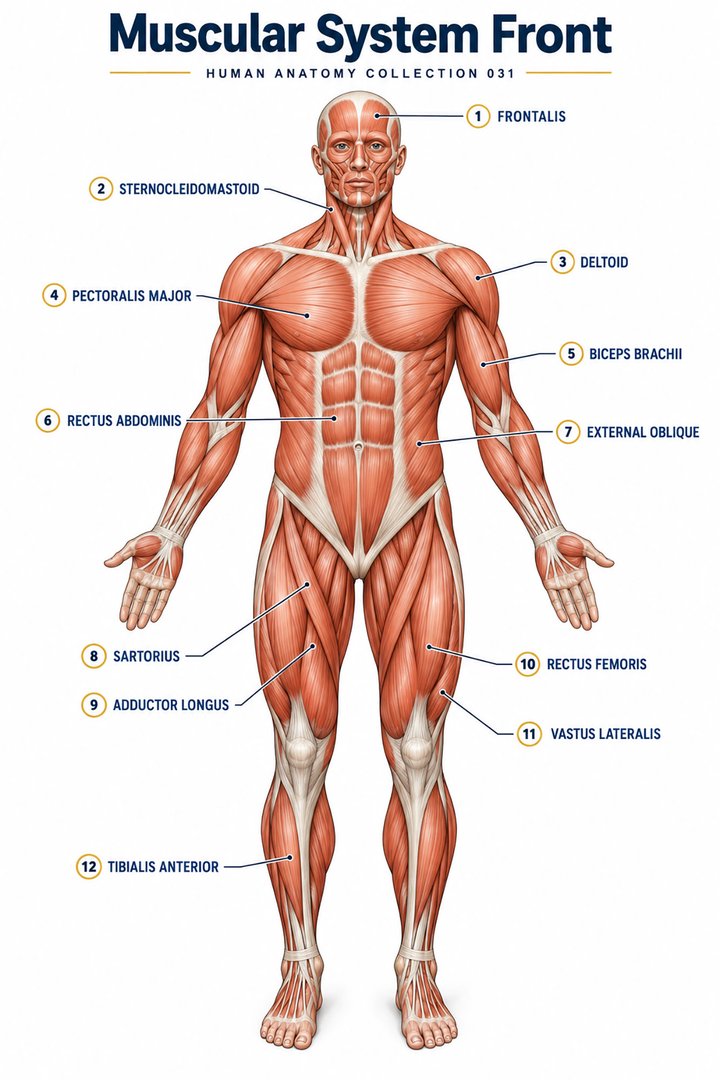 Muscular System Overview ↗
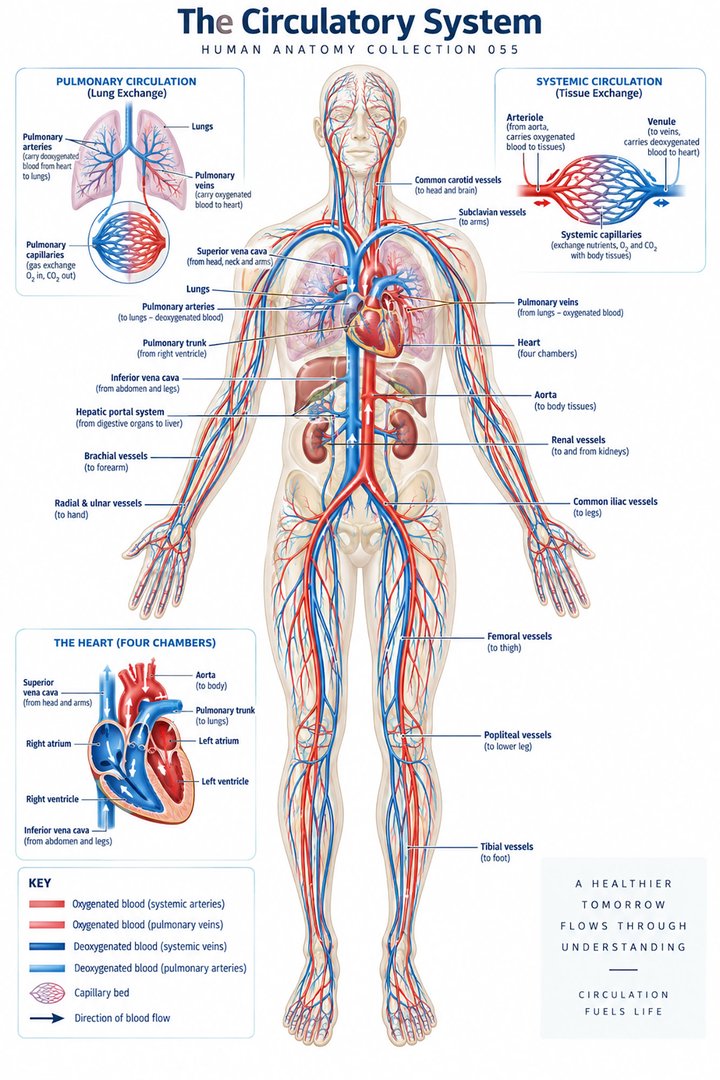 Human Circulatory System ↗
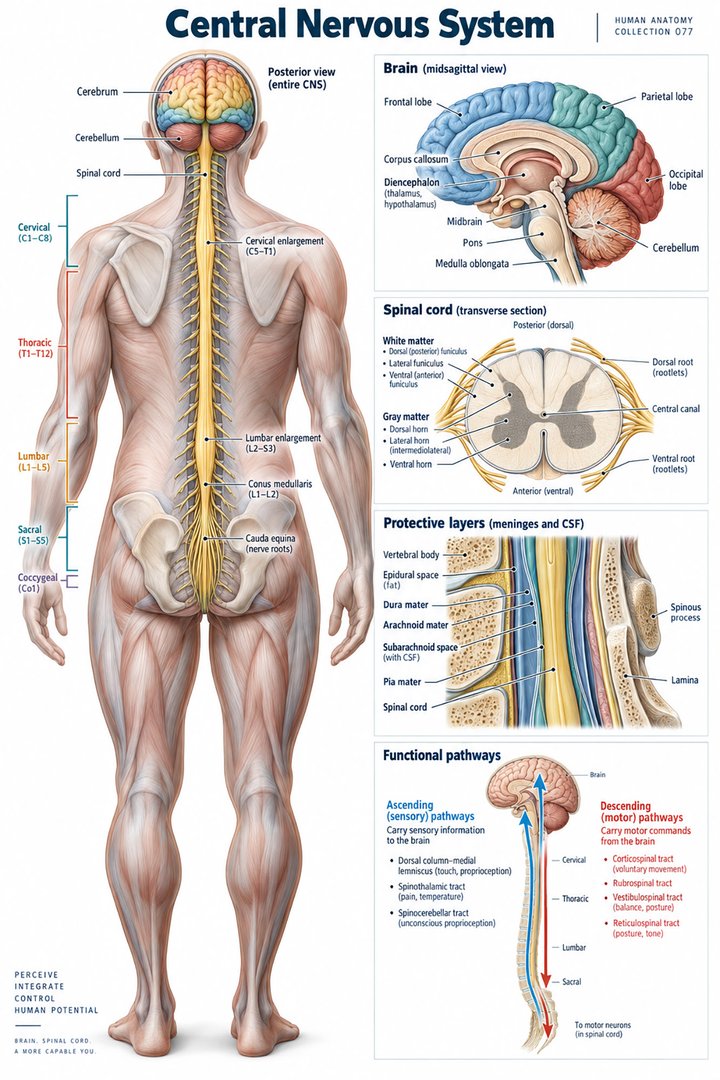 Human Nervous System ↗
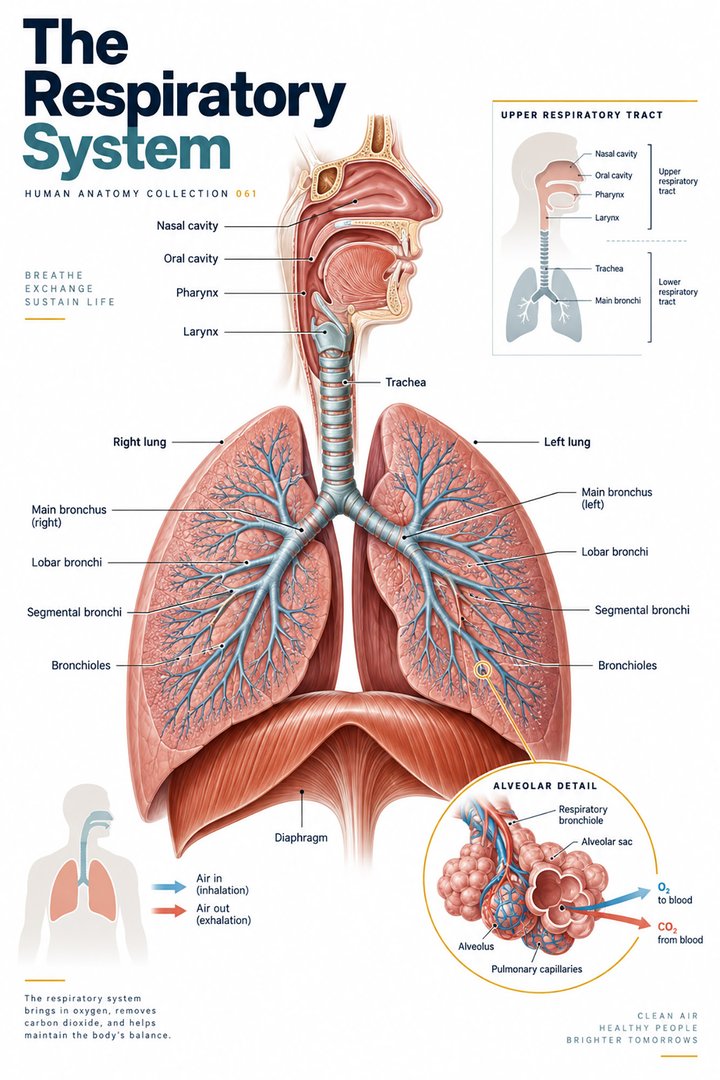 Respiratory System Functions ↗
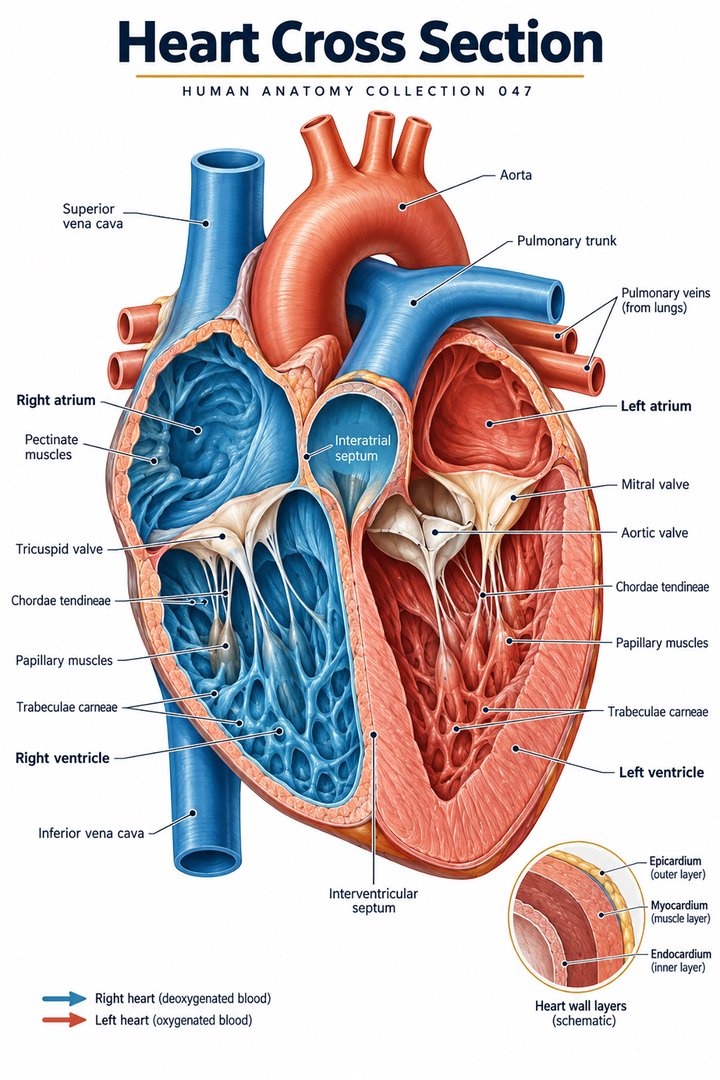 Human Heart Structure ↗
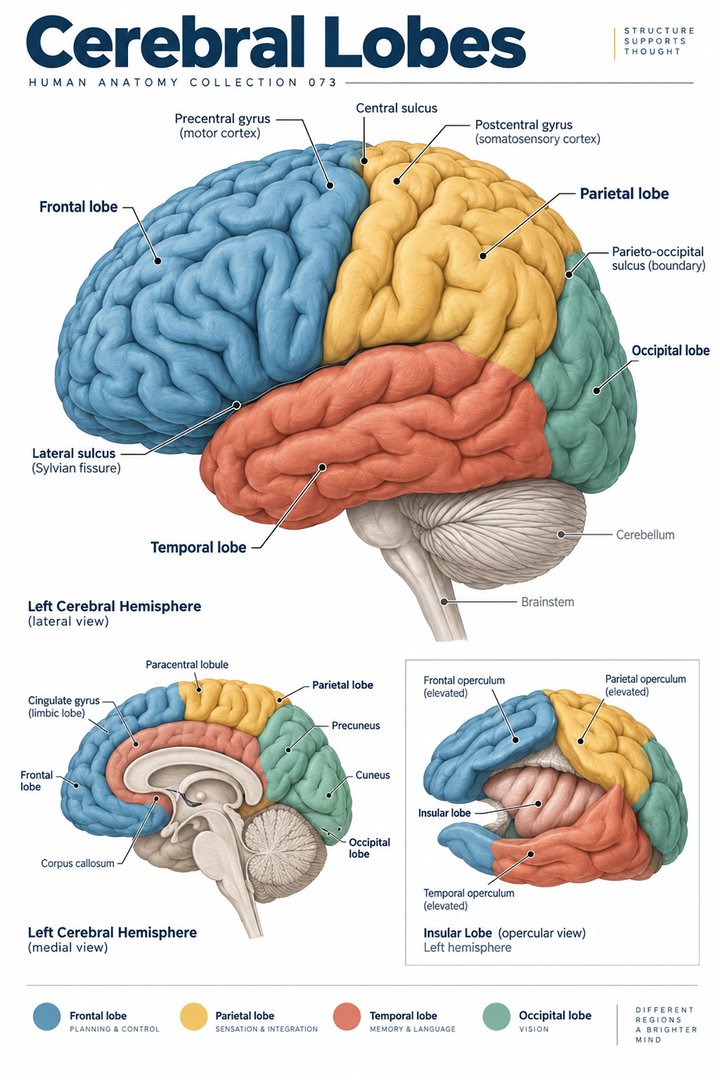 Human Brain Lobes ↗
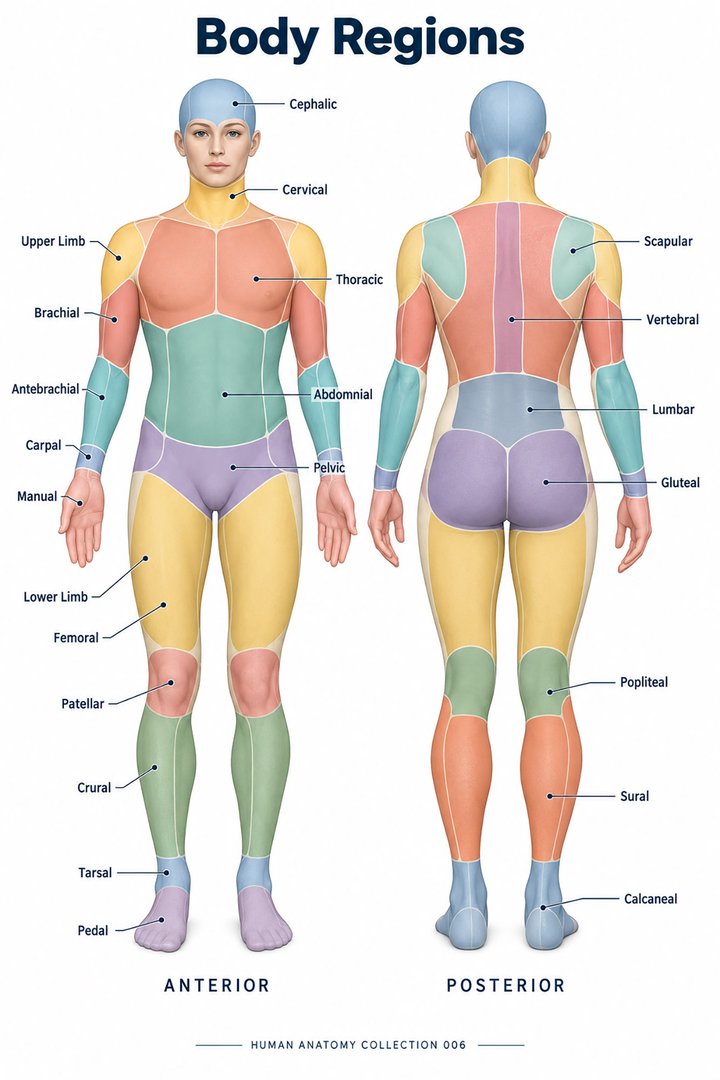 Human Body Parts ↗
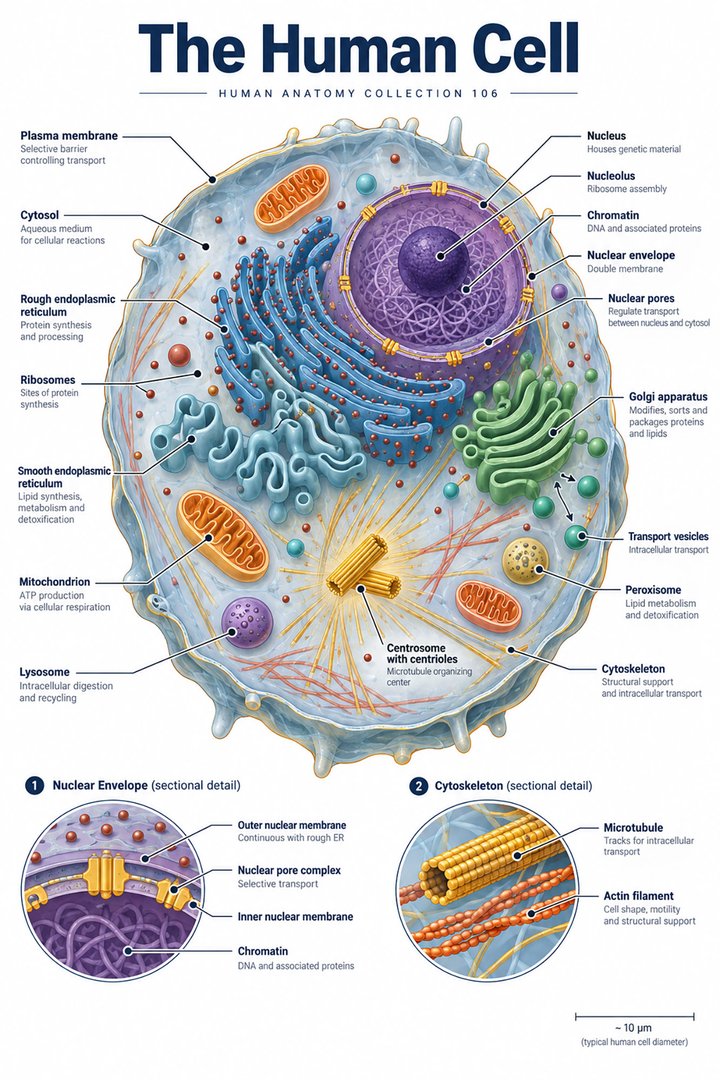 Human Cell Structure ↗
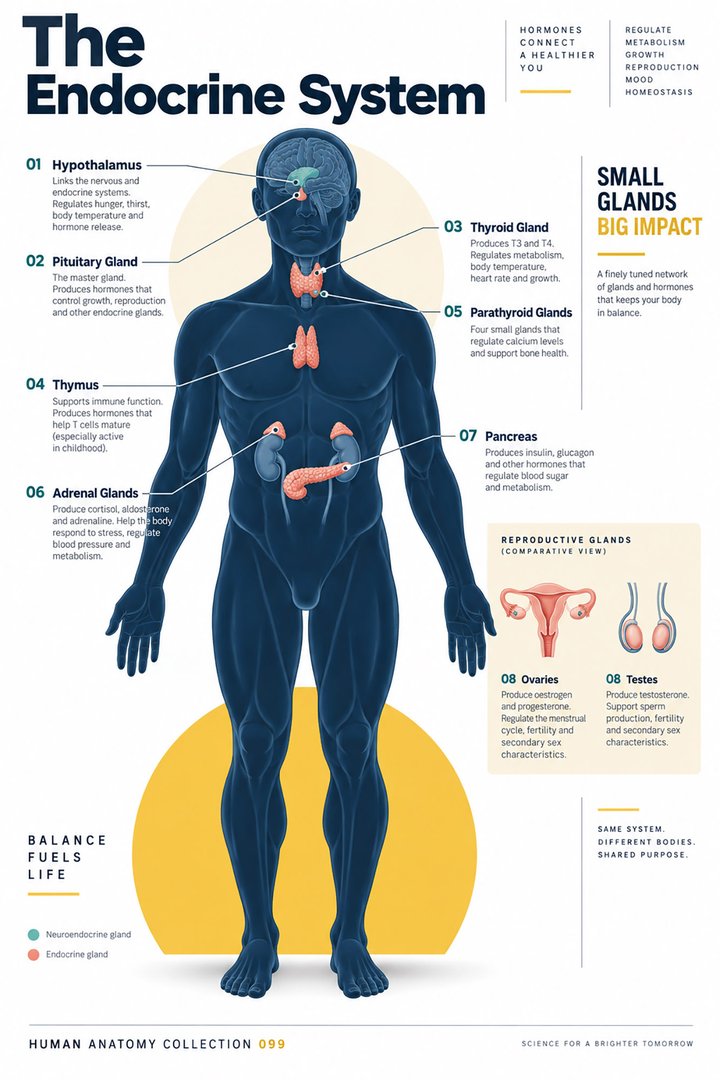 Human Endocrine System ↗
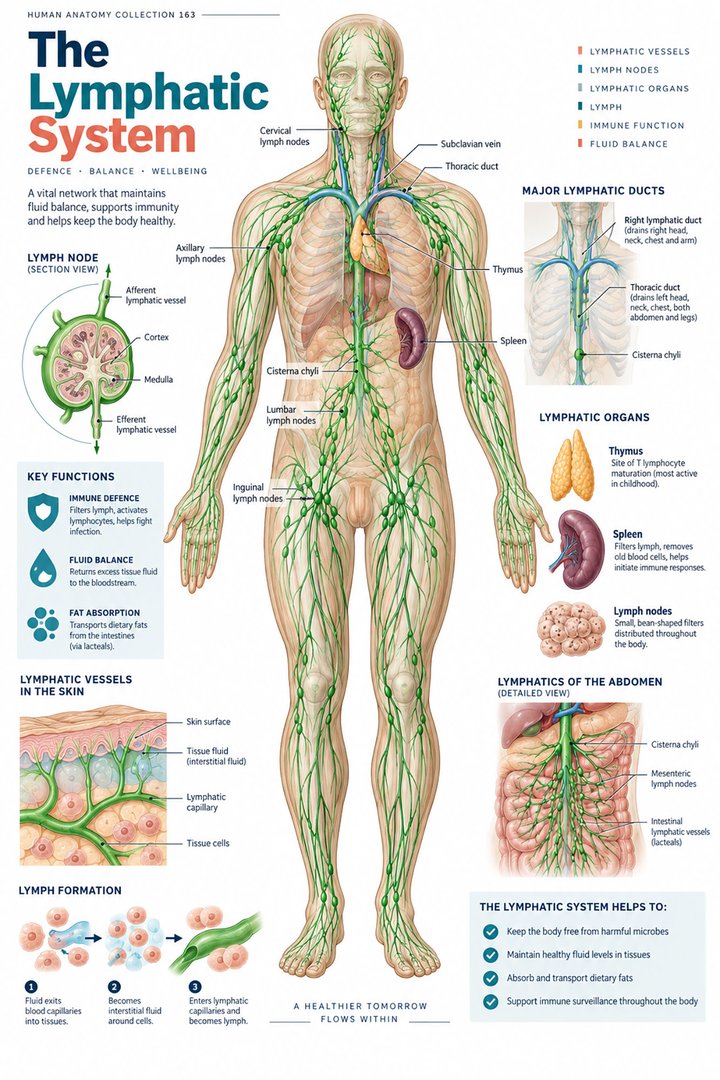 Human Lymphatic System ↗
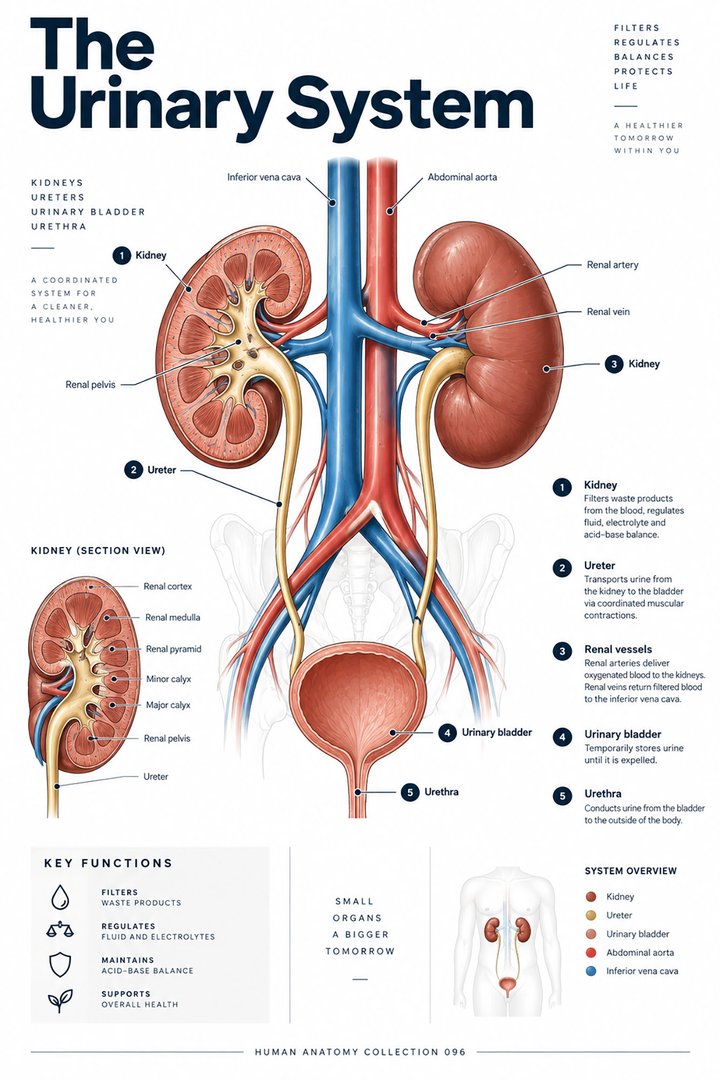 Human Urinary System ↗
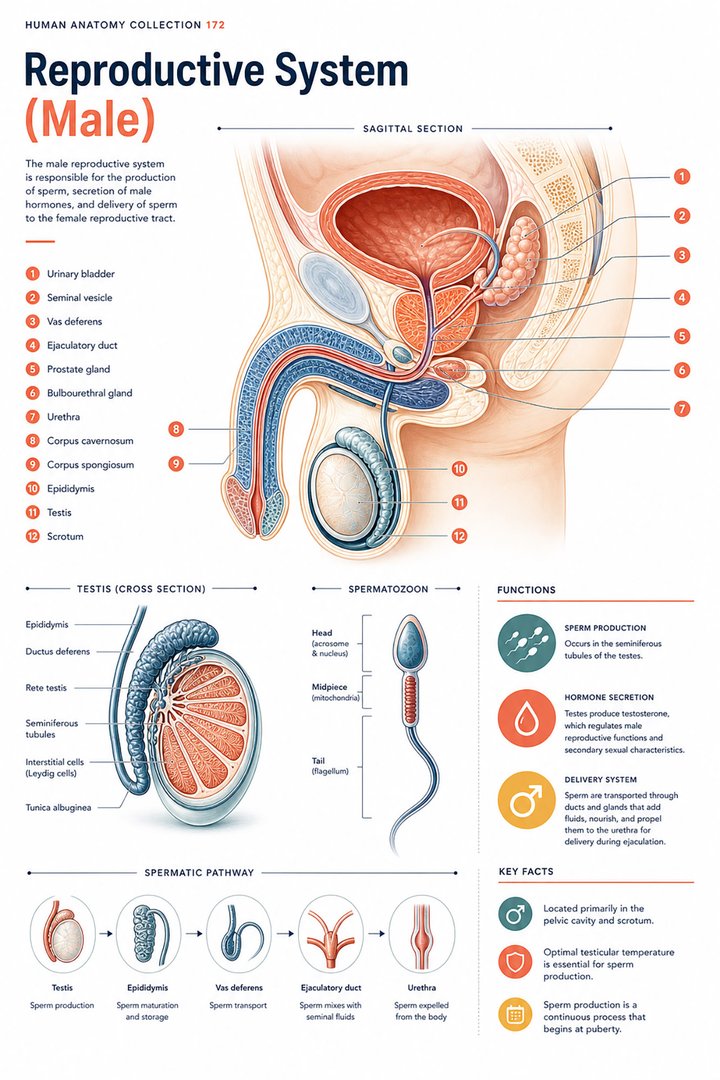 Male Reproductive System ↗
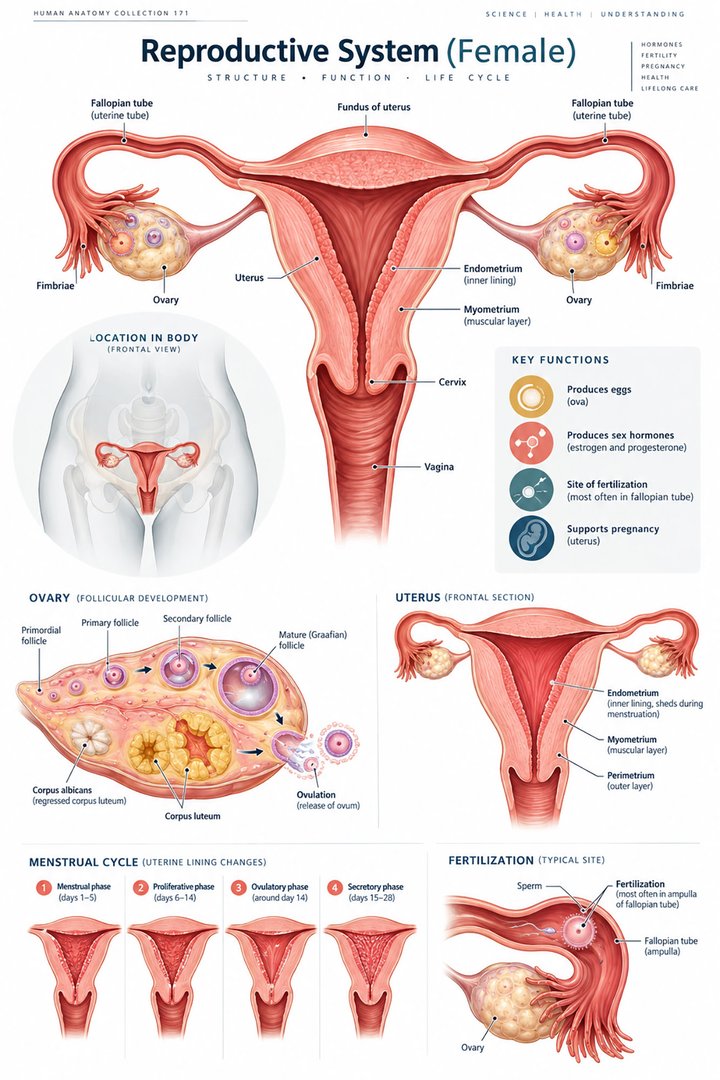 Female Reproductive System ↗
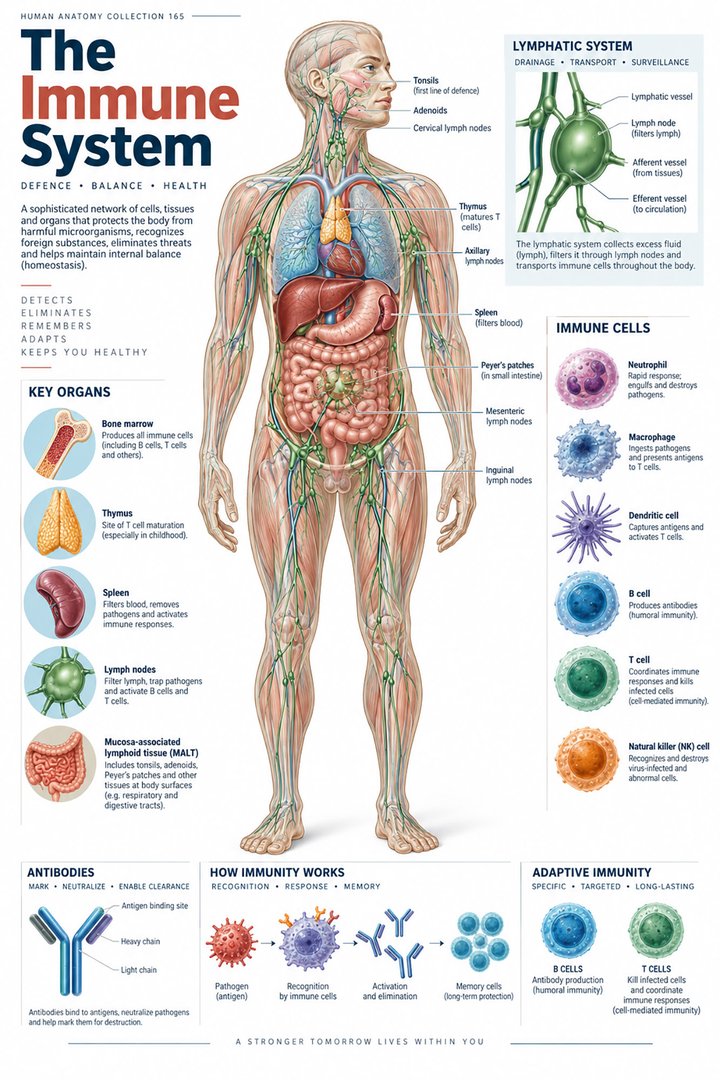 Human Immune System ↗Central Nervous System ↗Human Eye Structure ↗
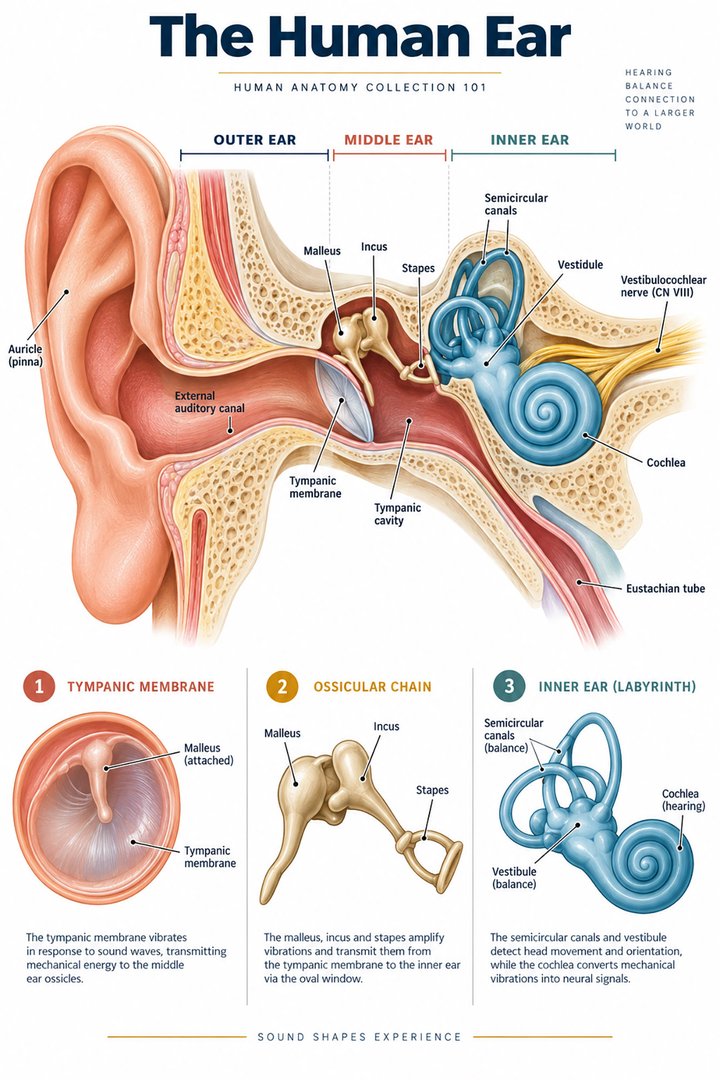 Human Ear Structure ↗
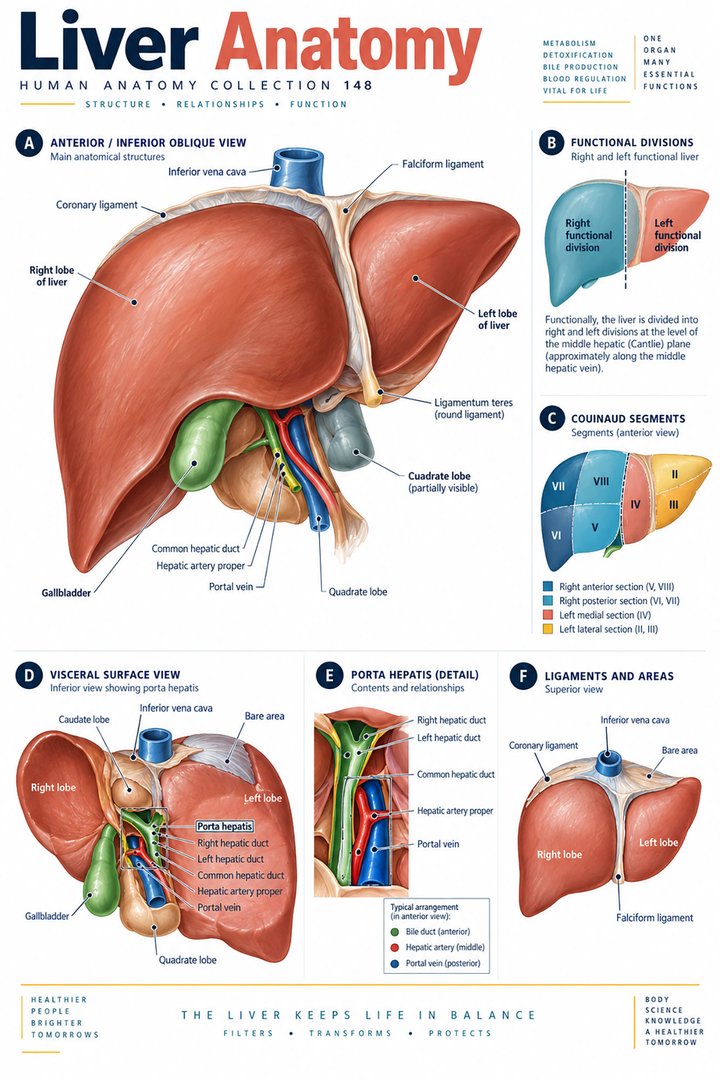 Human Liver Function ↗
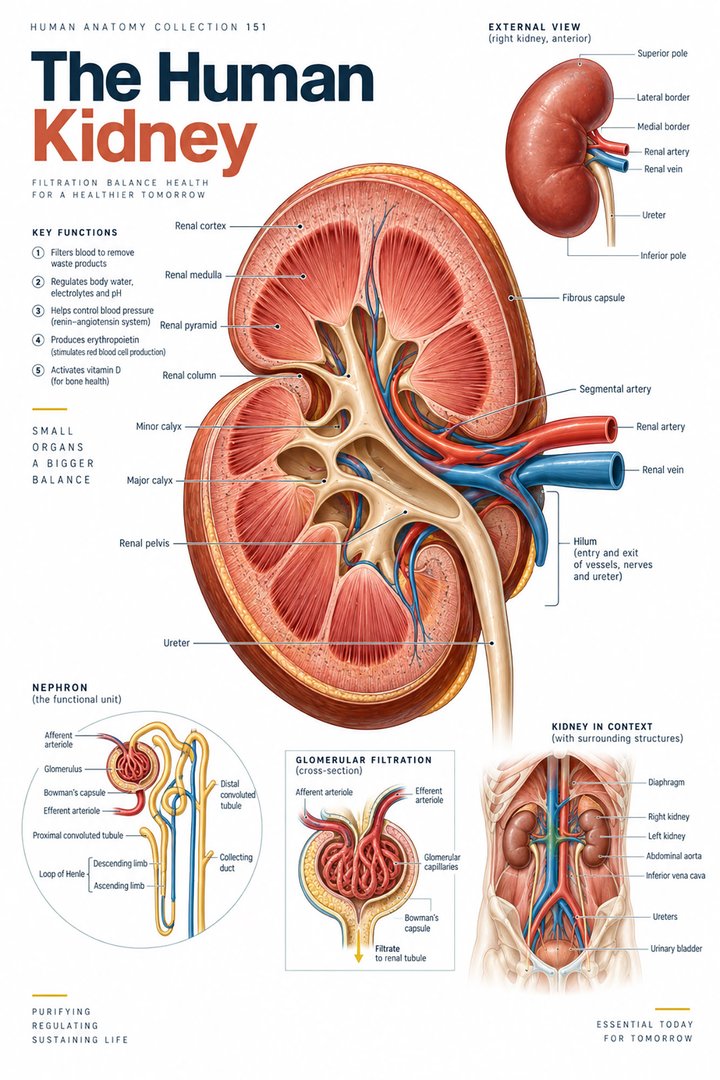 Human Kidney Anatomy ↗
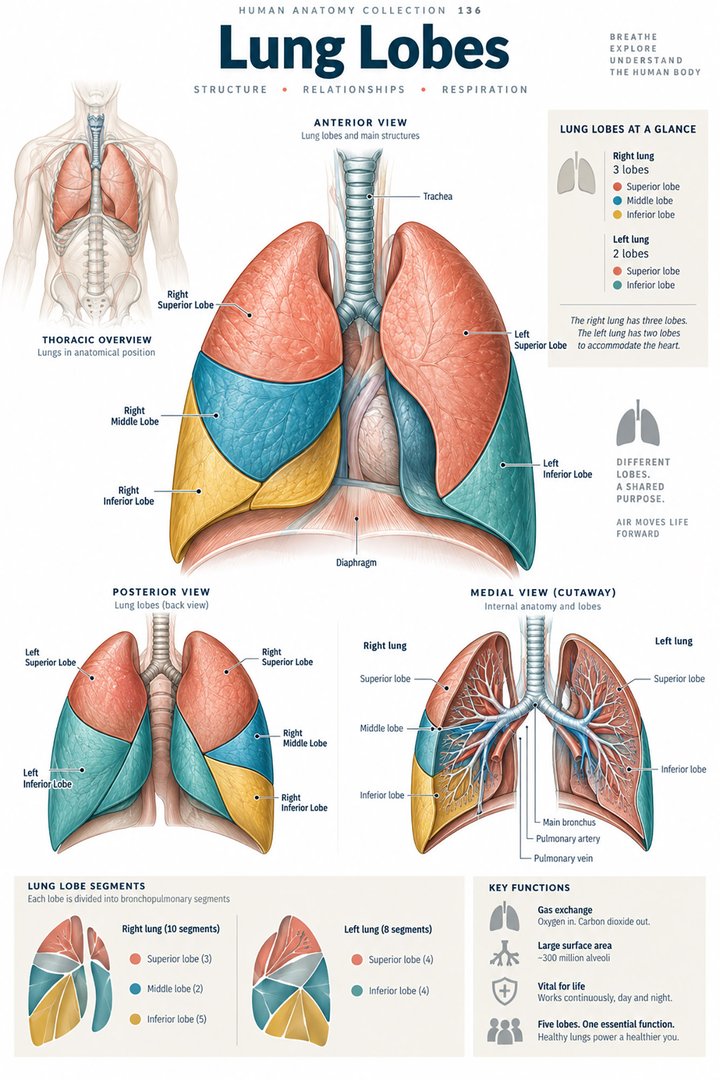 Human Lung Anatomy ↗
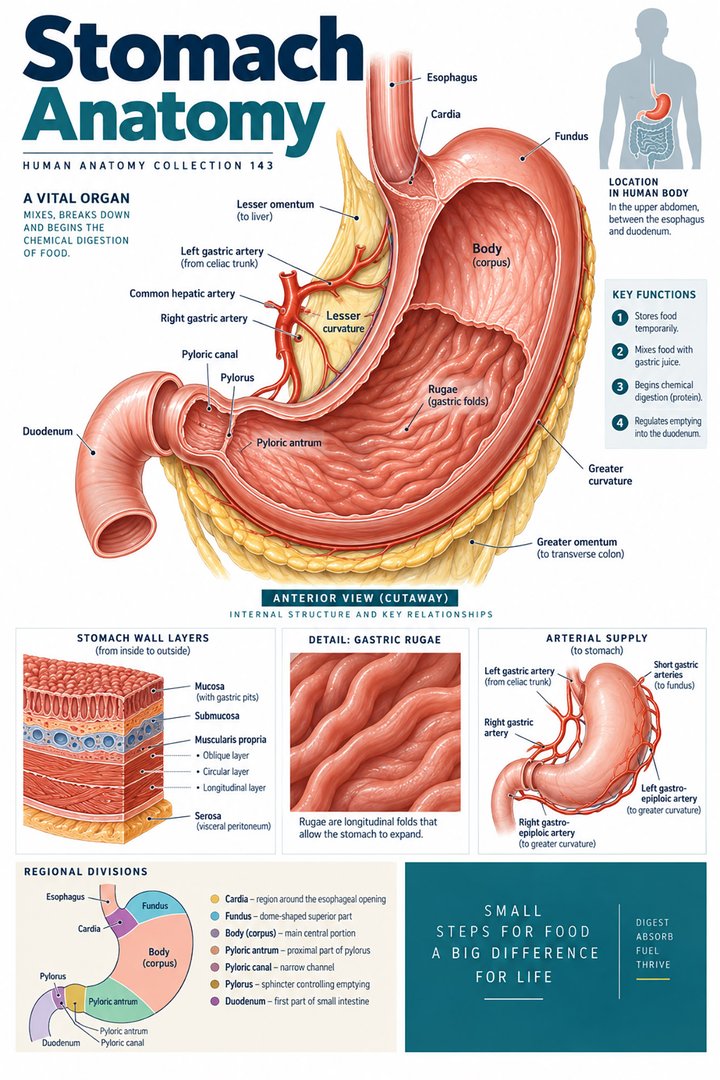 Human Stomach Structure ↗
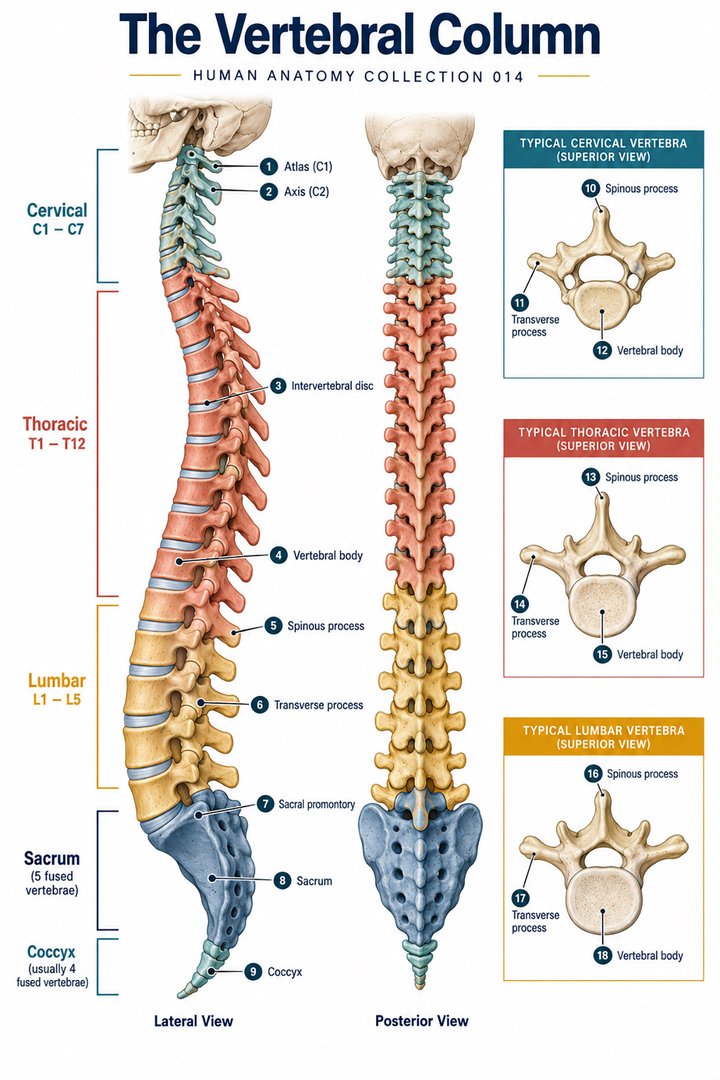 Human Spine Anatomy ↗
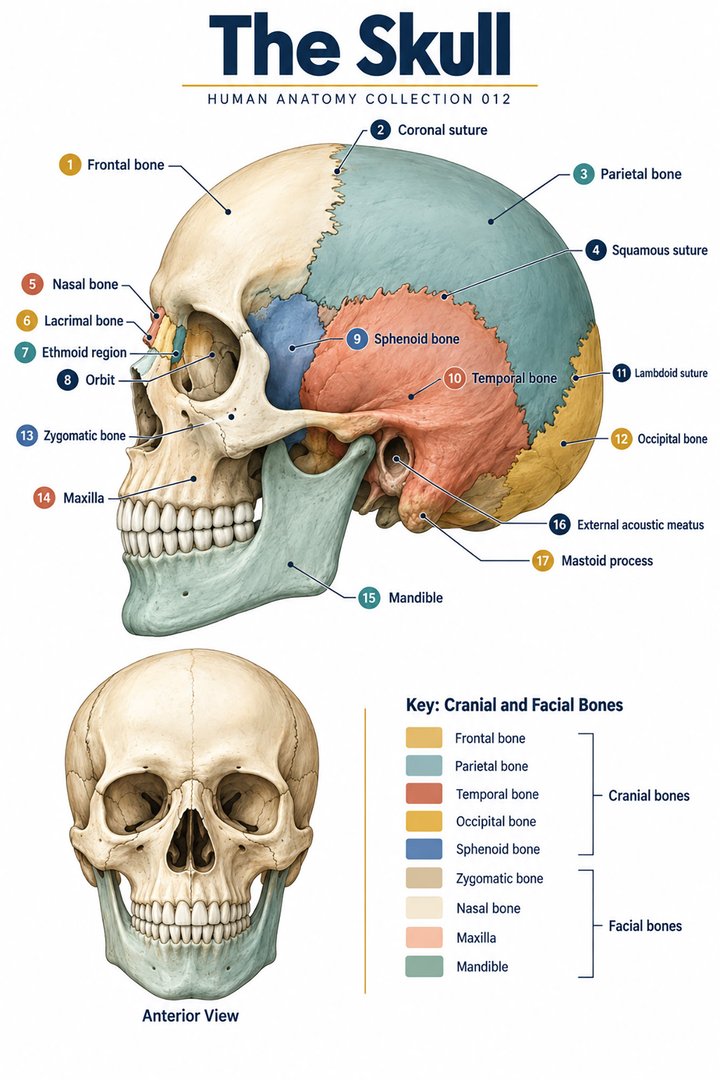 Human Skull Anatomy ↗
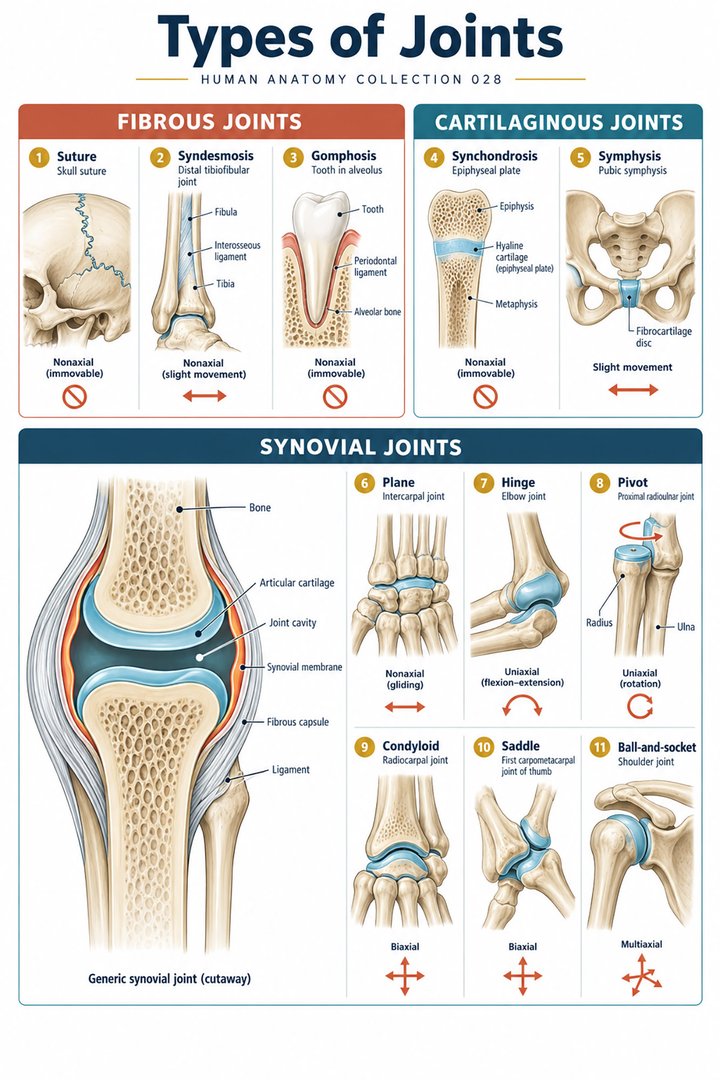 Human Joint Types ↗
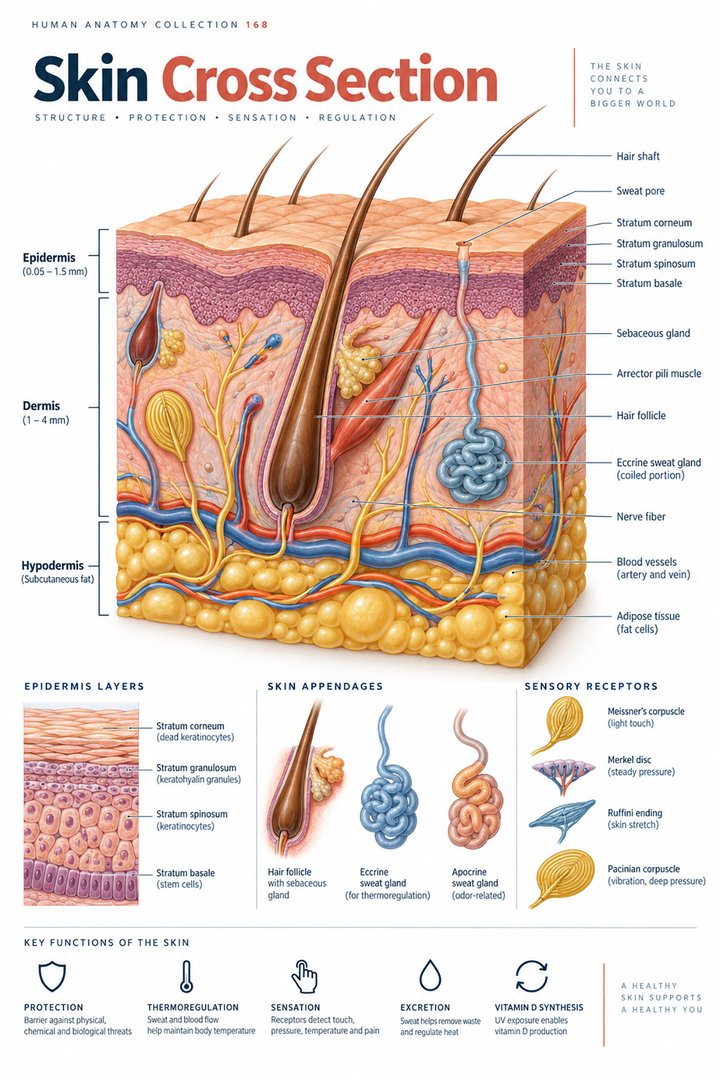 Human Skin Layers ↗
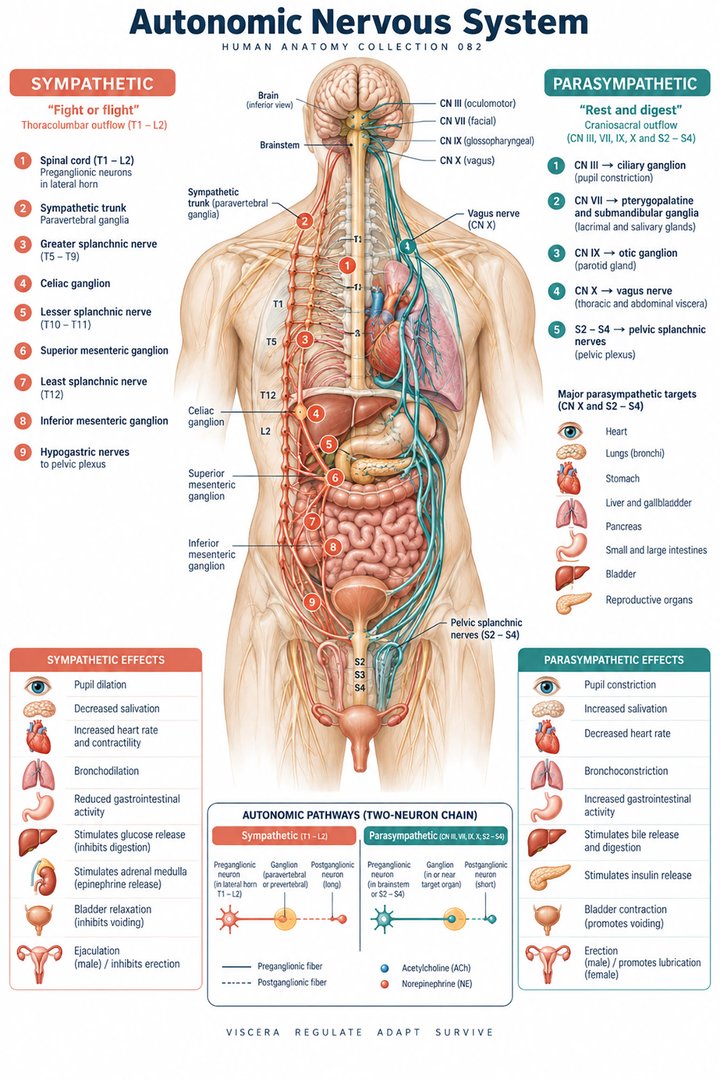 Autonomic Nervous System ↗
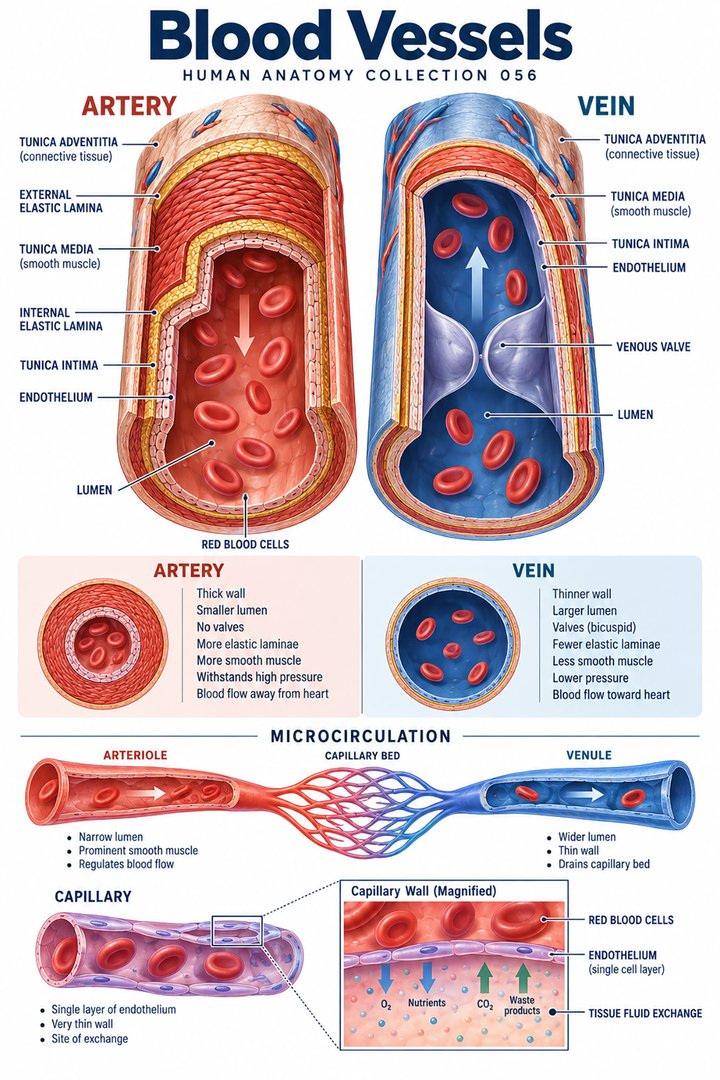 Human Blood Vessels ↗
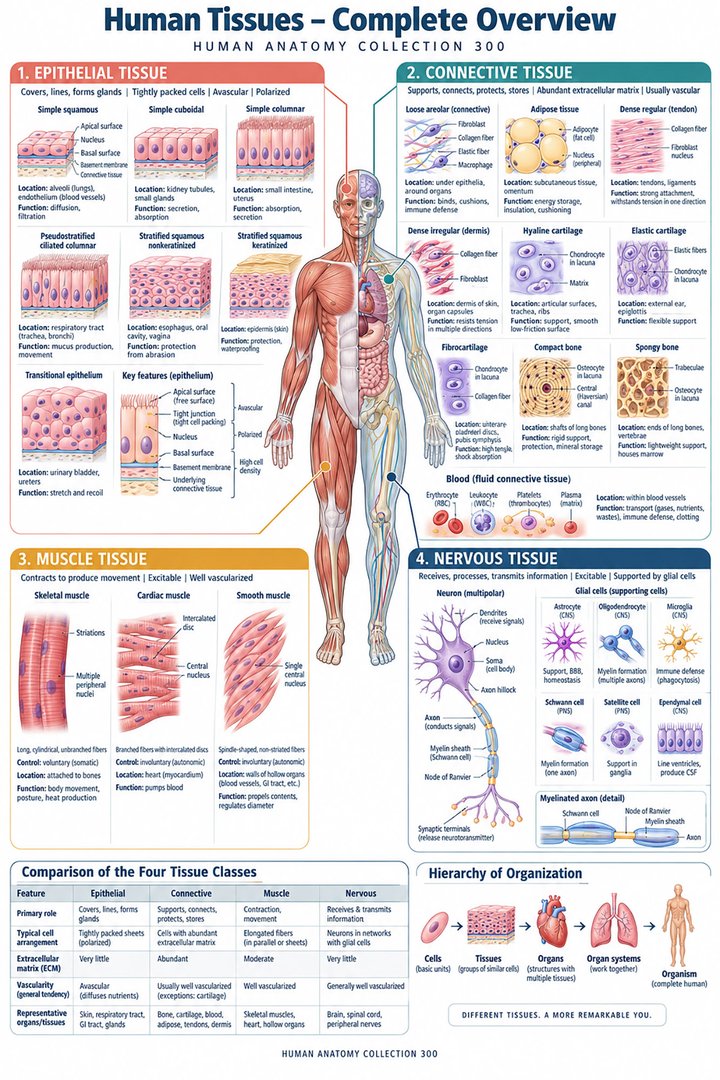 Human Body Tissues ↗
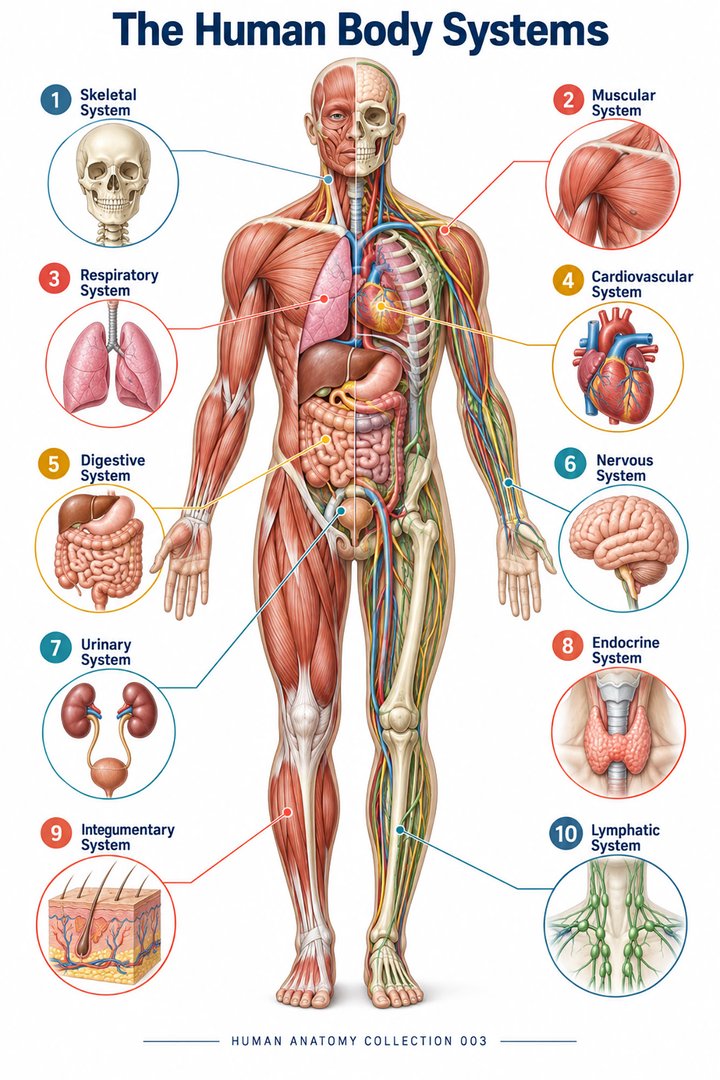 Human Body Systems ↗
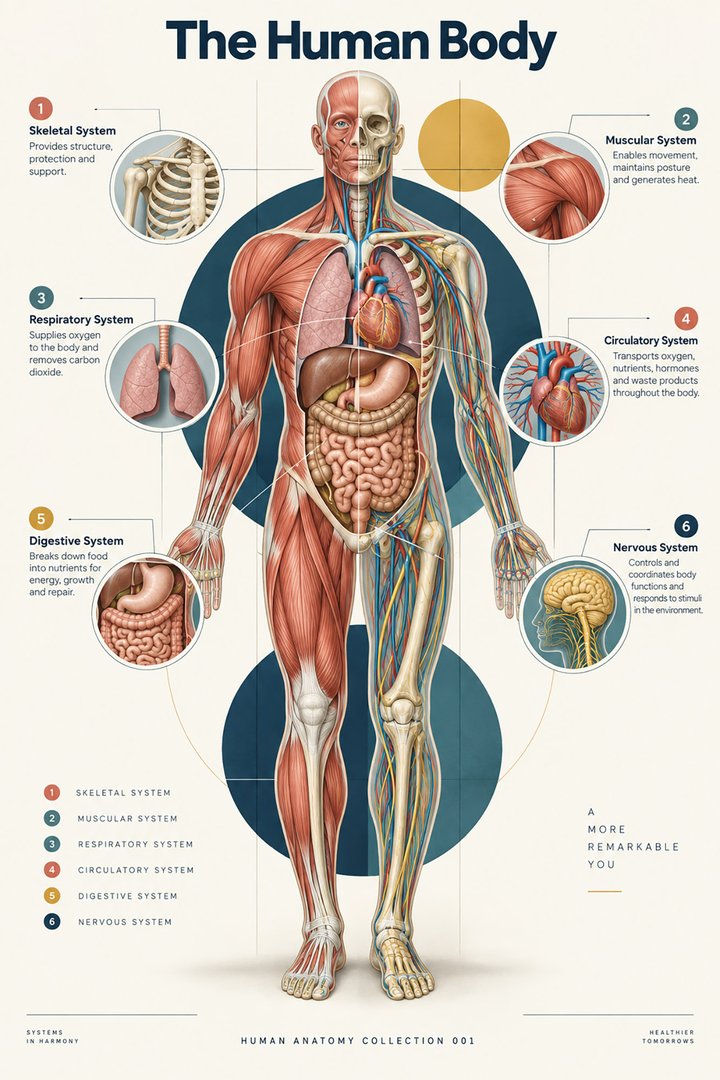 Human Body Facts ↗Human Anatomy and Physiology ↗
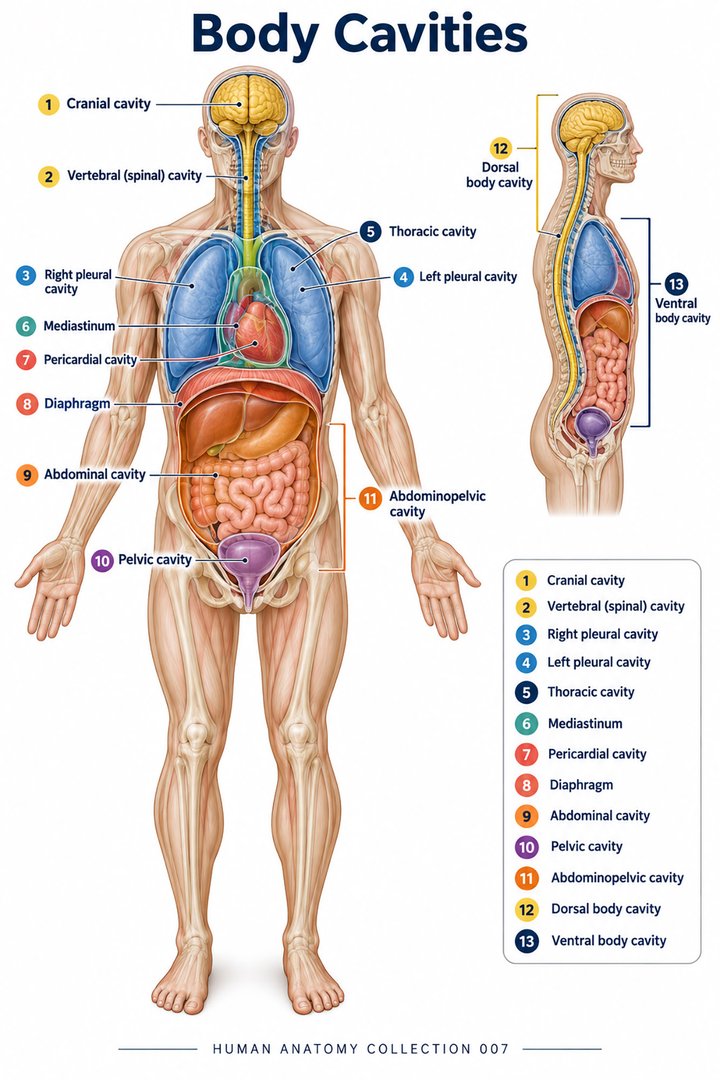 Human Body Cavities ↗Human Torso Anatomy ↗Human Digestive Tract ↗
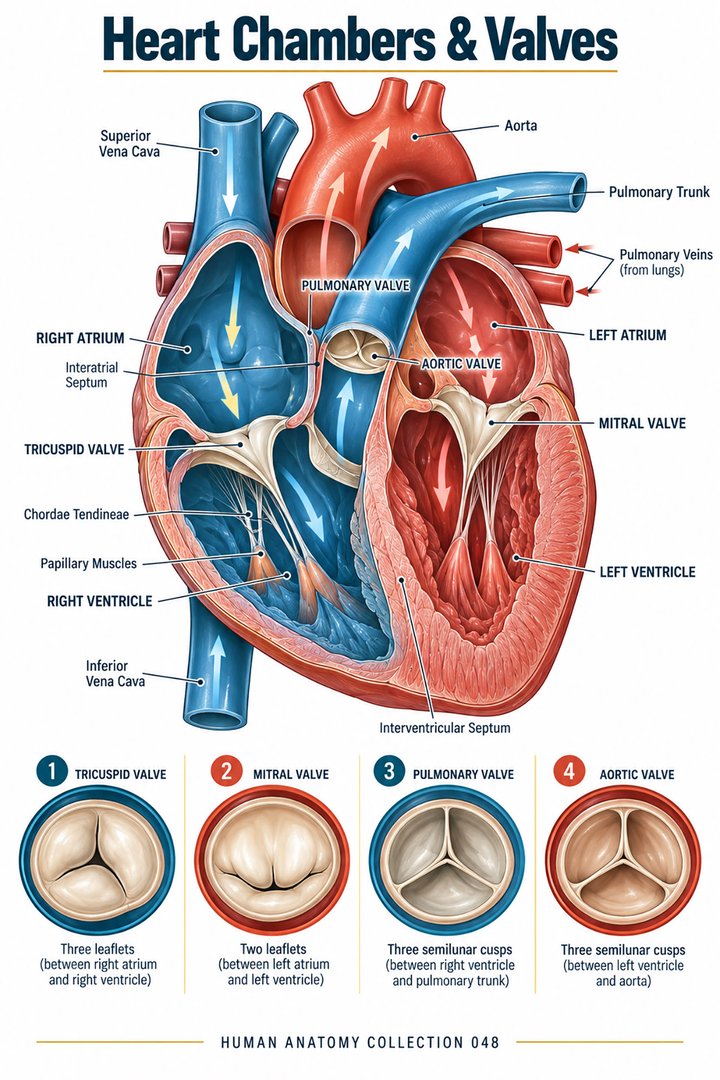 Human Heart Chambers ↗Human Organ Placement ↗
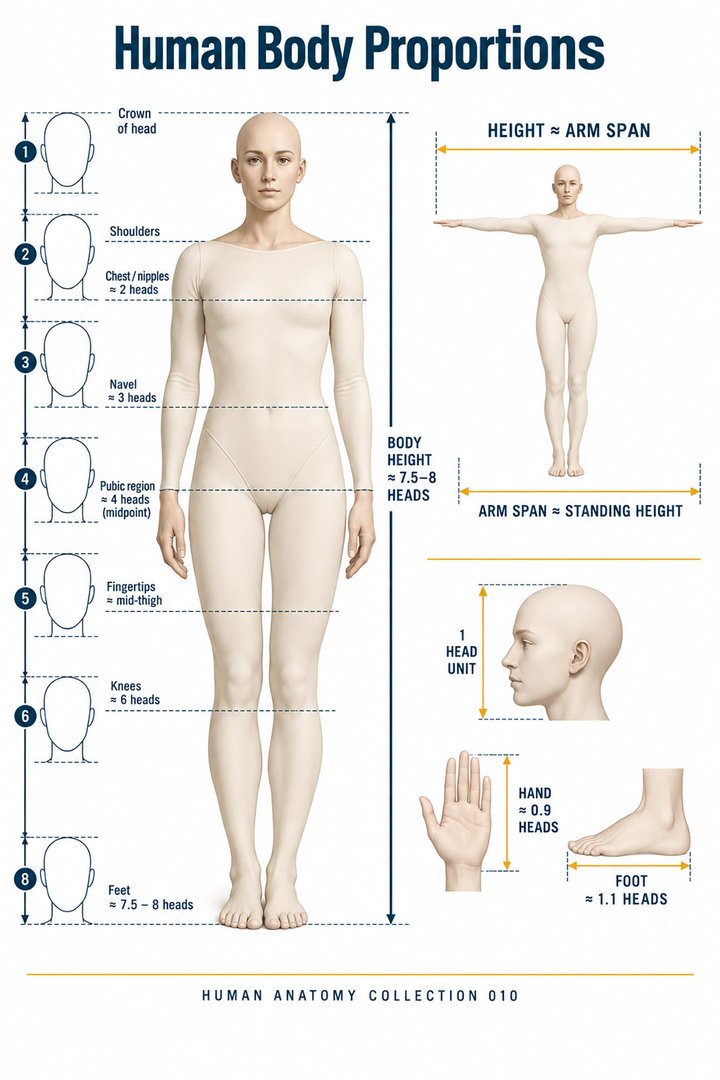 Human Body Proportions ↗
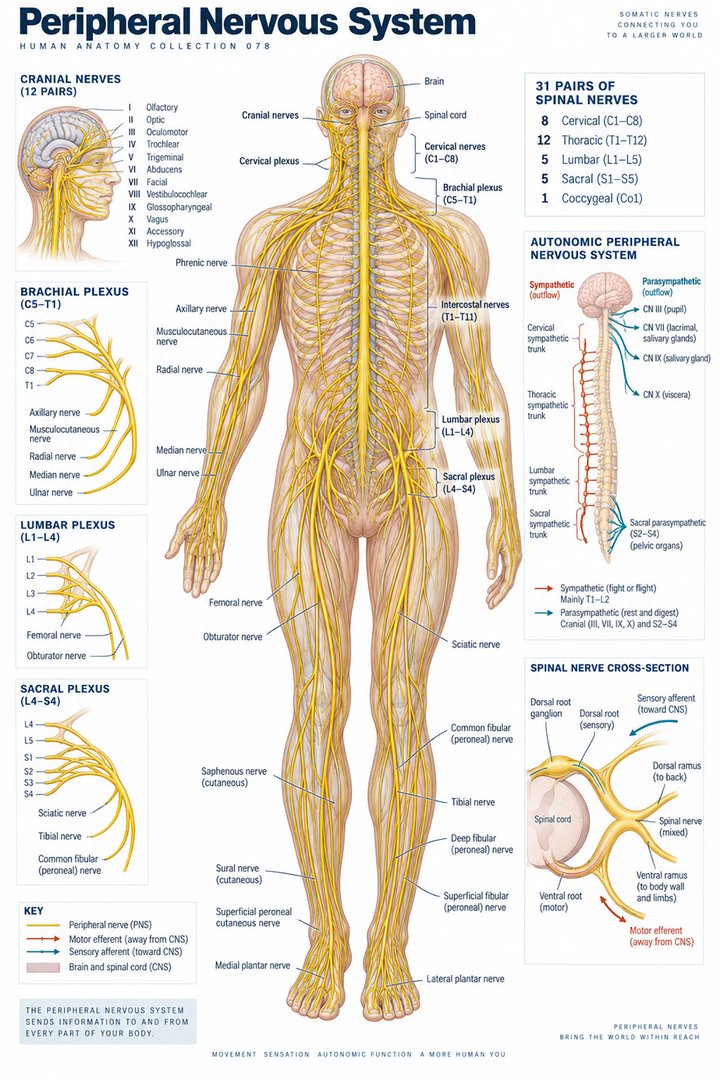 Peripheral Nervous System ↗
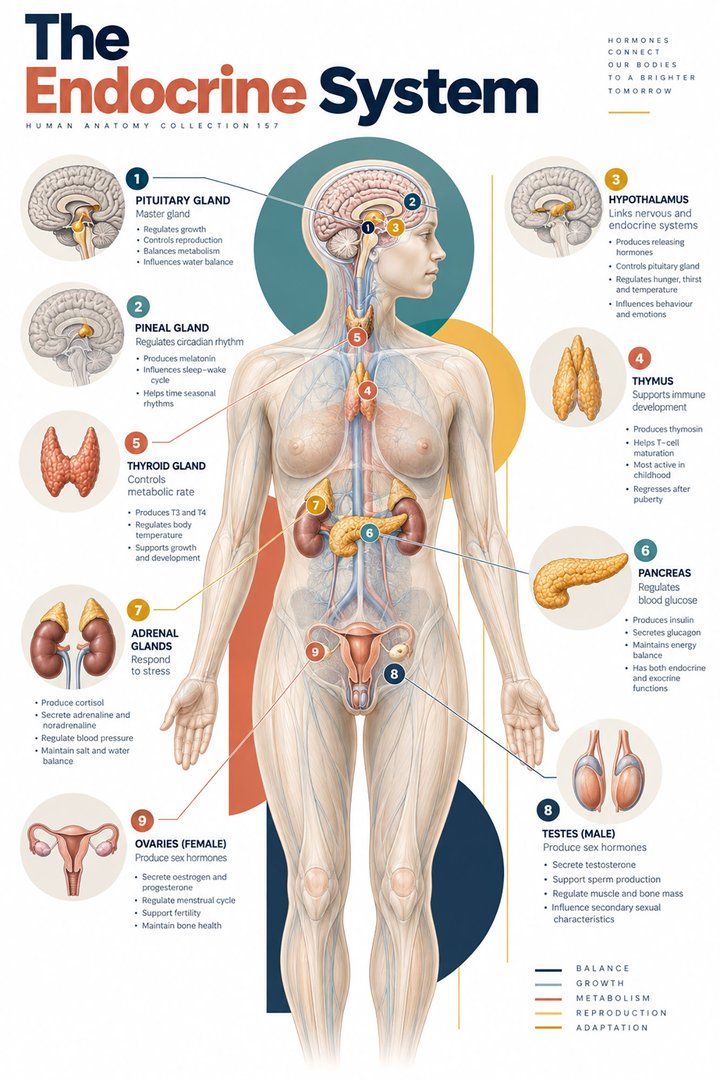 Human Endocrine Glands ↗
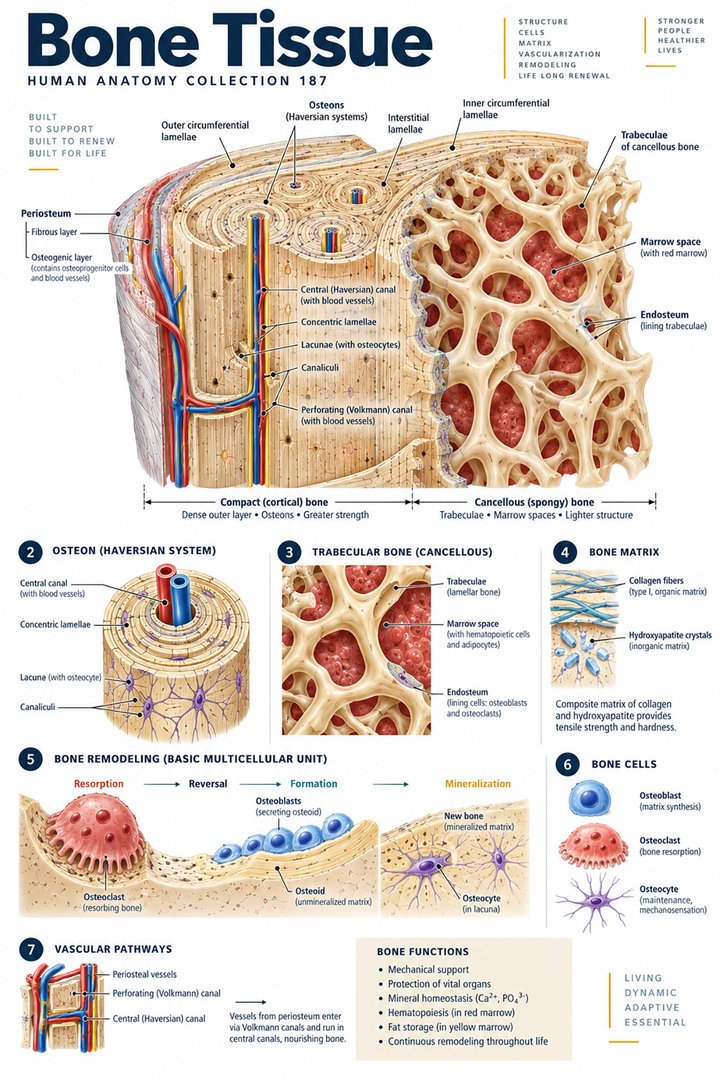 Human Bone Density ↗Human Blood Circulation ↗
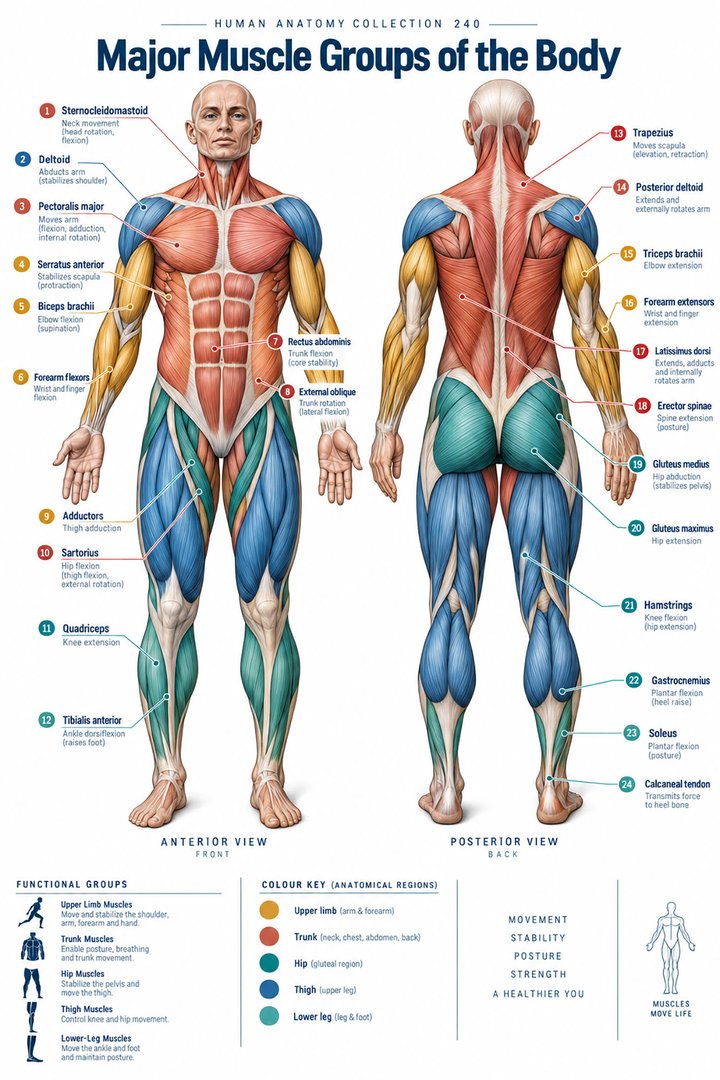 Human Muscle Groups ↗
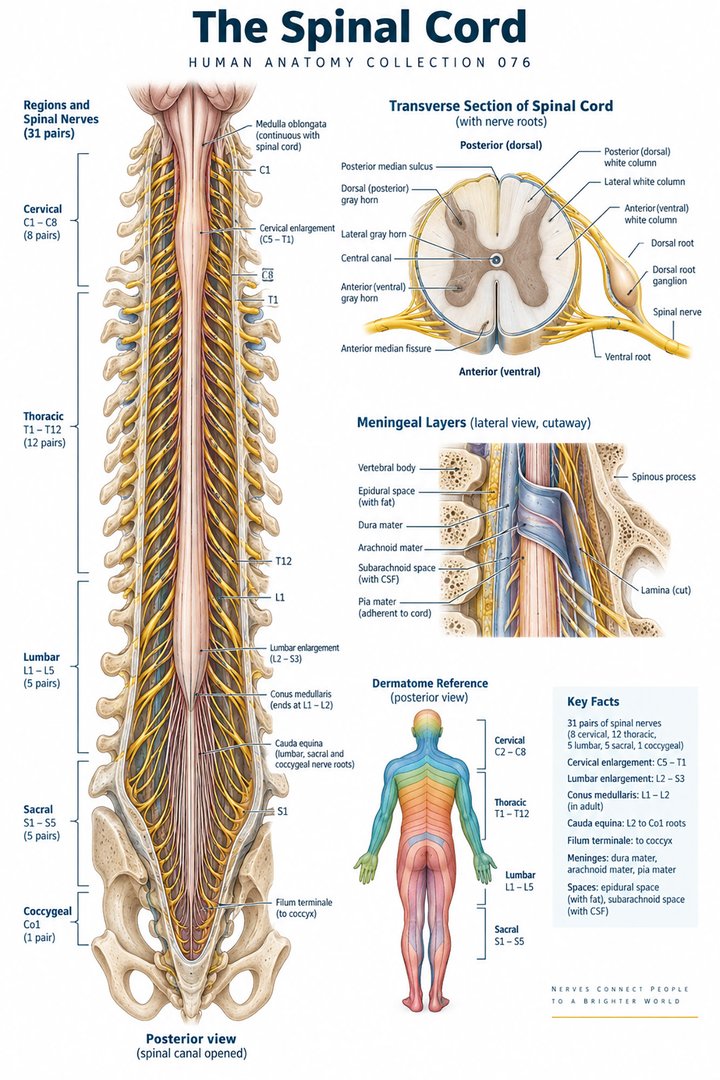 Human Spinal Cord ↗
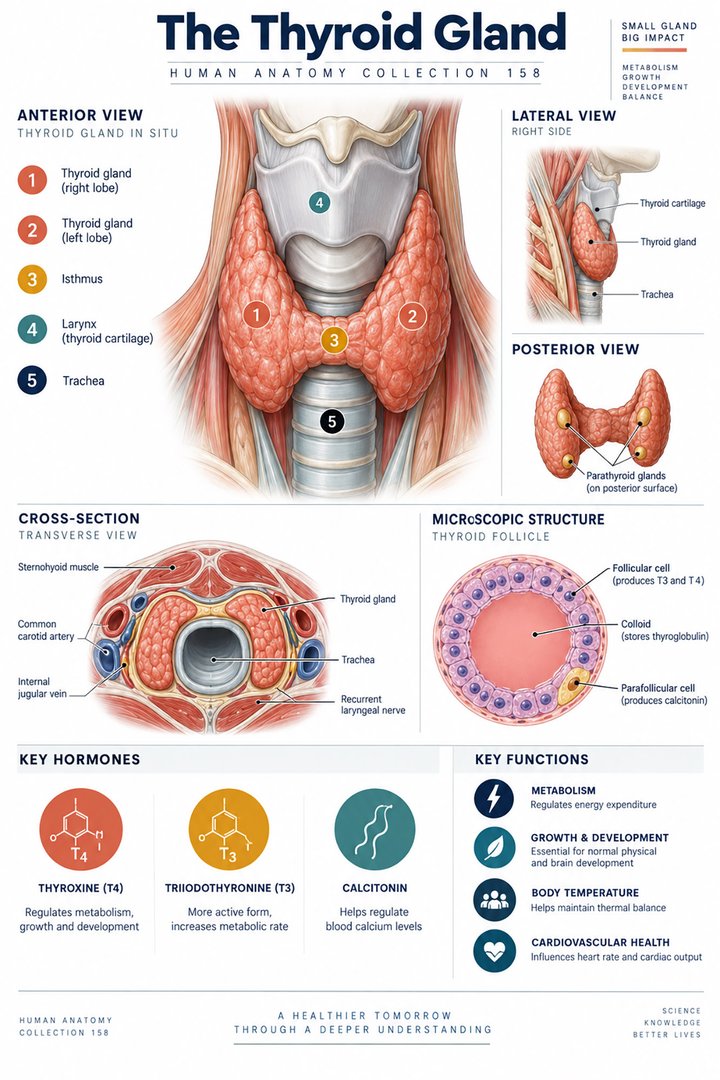 Human Thyroid Gland ↗
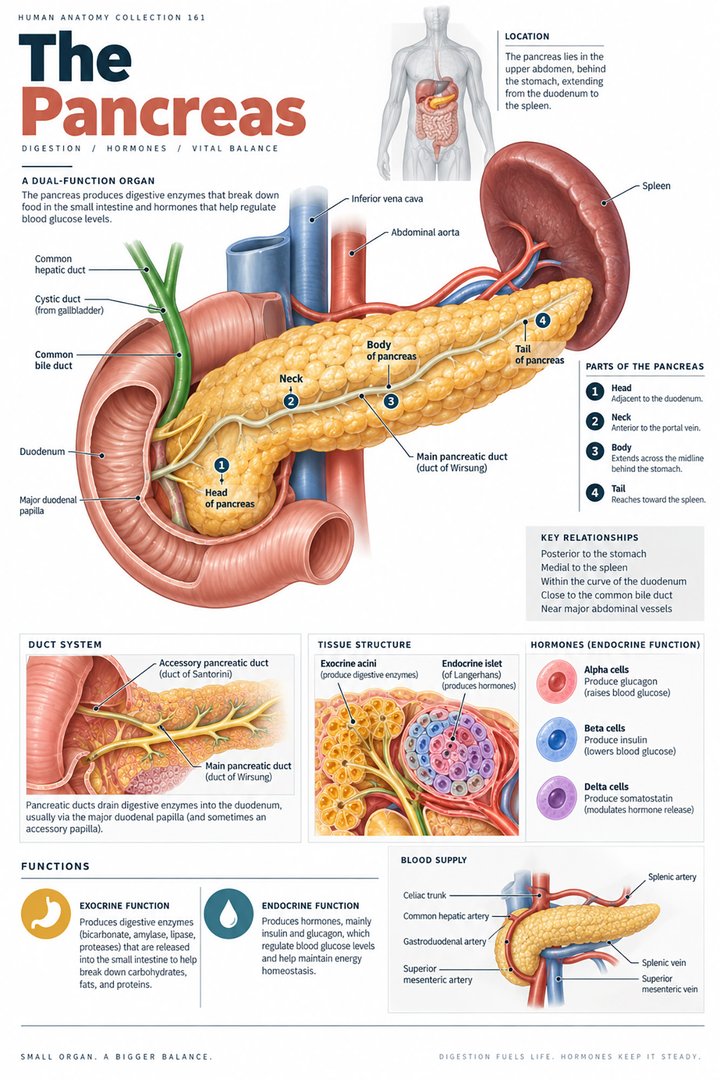 Human Pancreas Function ↗
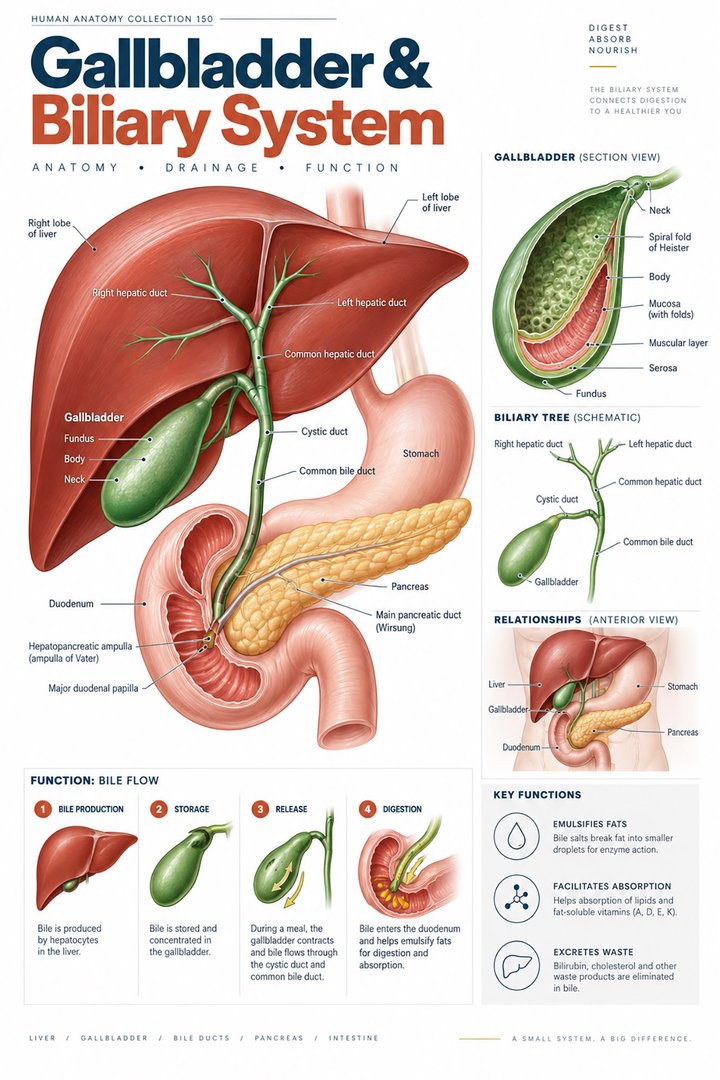 Human Gallbladder Anatomy ↗